Related Experiment Video
Updated: Aug 20, 2025
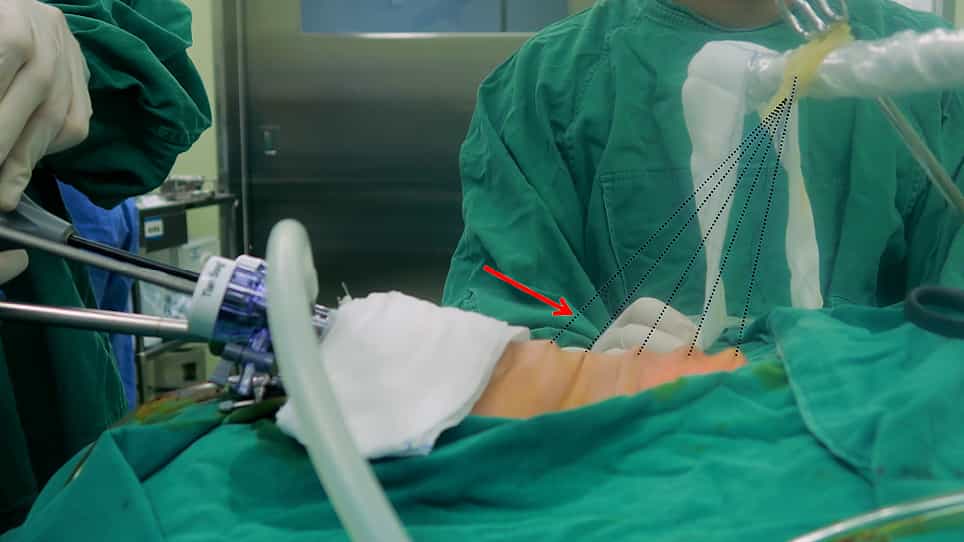

Transoral Endoscopic Thyroidectomy Vestibular Approach for Thyroid Lobectomy
Published on: May 12, 2023
Getting Your Foot in the Door: Access to Surgical Care for Thyroid Disease
Rongzhi Wang1, Adam Bonner2, Nicolas Mayfield2
1Department of Surgery, University of Alabama at Birmingham, Birmingham, Alabama.

Introduction:
Access to specialty care can be challenging for patients, often involving multiple evaluations, laboratory tests, and referrals. To better understand the different pathways to specialty care, we examined the outcomes of patients evaluated for surgical thyroid disease at a single tertiary referral clinic.
Methods:
We reviewed 691 patients seen in the endocrine surgery clinic for thyroid disease (2018-2021). Patient demographics, referral source, referral reason, and reason for not receiving an operation were collected. The number of days from referral to initial clinic visit and from initial clinic visit to an operation were also collected. The Chi-square test, the independent t-test, the Kruskal-Wallis test, the Dunn-Bonferroni post hoc test, and multiple logistic regression tests were performed using SPSS.
Results:
The top reasons for referral were thyroid nodules (54.4%), hyperthyroidism (26.5%), and multinodular goiter (10.3%). Specialty clinic referrals came from endocrinologists (56.0%), self-referrals (15.5%), and primary care physicians (PCP; 14.4%). Self-referred patients had a shorter waiting time for an appointment than those referred by endocrinologists and PCPs. [median (IQR) (days) 12 (6-17) versus 16 (9-24) versus 16 (9-25), P < 0.001]. Overall, 450 (72.7%) patients underwent thyroid surgery. For those who underwent thyroidectomy, self-referred patients had a shorter time between initial clinic visit and the operation compared to those referred by endocrinologists and PCPs [median (IQR) (days) 2 (1-19) versus 19 (8-33) versus 16 (1-48), P < 0.001]. Patients referred for hyperthyroidism (odds ratio [OR] = 2.2, 95% confidence interval [CI] 1.3-10.5, P = 0.012 were more likely to undergo an operation than those referred for other reasons.
Conclusions:
Access to specialty care for thyroid disease is facilitated and optimized when self-referrals are permitted. Reducing or eliminating the requirement for a provider referral may improve patients' access.
Related Concept Videos
 01:23
The Thyroid Gland
The follicles have a central cavity lined by simple cuboidal to squamous epithelial cells called follicular cells. These cells produce the glycoprotein...
 01:20
Synthesis and Regulation of Thyroid Hormones
Upon reaching the thyroid gland, TSH stimulates the follicular cells' active uptake of iodide ions from the blood. The ions diffuse to the apical surface of the cells and are oxidized to iodine. The...
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:18
Functions of Thyroid Hormones
TH is indispensable for the normal development and maturation of the skeletal, muscular, and nervous systems during fetal and childhood growth. It facilitates bone mineral turnover and regulates protein synthesis in developing tissues, contributing significantly to overall growth and...
 01:16
Tracheostomy Care I: Pre-procedural Steps
Required Equipment
The equipment necessary for tracheostomy care includes:
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD: