Related Experiment Video
Updated: Aug 19, 2025
08:03

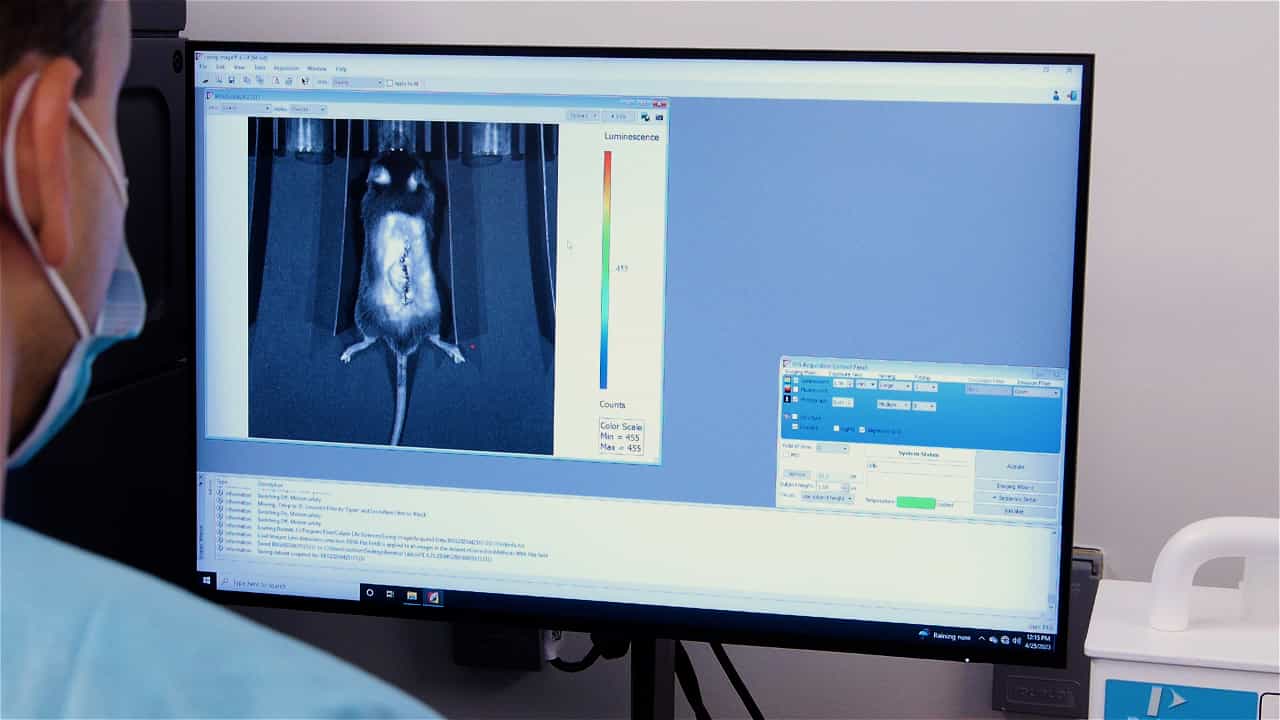
In Vivo Mouse Model of Spinal Implant Infection
Published on: June 23, 2020
2.4K
The Time is Ripe for a Randomized Controlled Trial of Oral Vancomycin in Primary Sclerosing Cholangitis
Jennifer Christine Halma1, Laura Cristoferi2, Marco Carbone2
1Division of Gastroenterology, Hepatology, and Nutrition, Department of Pediatrics, Stanford University School of Medicine, Lucile Packard Children's Hospital, Stanford, California.

Abstract
No abstract available in PubMed .
More Related Videos


Related Concept Videos
 01:16
Treating Helicobacter pylori in Peptic Ulcers: Antimicrobial Therapy
511
Helicobacter pylori, a resilient gram-negative bacterium, can thrive in the stomach's harsh, acidic environment. Infection with H. pylori leads to a cascade of events within the stomach lining. One of the critical disruptions caused by this bacterium is the interference with somatostatin production, a hormone responsible for regulating acid secretion. This interference tips the balance, escalating acid secretion and diminishing bicarbonate levels. This imbalance compromises the defensive...
511
 01:24
Drugs for Peptic Ulcer Disease: Sucralfate as Mucosal Protective Agents
631
In the intricate landscape of the gastric lumen, excessive acid secretion disrupts the natural defense mechanisms, weakening the mucus-bicarbonate barrier. This vulnerability allows pepsin to infiltrate epithelial cells, digesting mucosal proteins and triggering erosion, leading to ulcer formation.
In this scenario, mucosal protective agents like sucralfate play an essential role. Sucralfate, a complex of sulfated sucrose and aluminum hydroxide, demonstrates its usefulness in acidic conditions,...
In this scenario, mucosal protective agents like sucralfate play an essential role. Sucralfate, a complex of sulfated sucrose and aluminum hydroxide, demonstrates its usefulness in acidic conditions,...
631
 01:29
Chronic Pancreatitis II: Collaborative Care
122
The management of chronic pancreatitis is multifaceted, involving a comprehensive approach that includes thorough assessment, diagnostic testing, and a variety of management strategies.
Assessment:
Assessment:
122
 01:28
Esophageal Varices-II: Clinical Features and Management
118
Esophageal varices often manifest as gastrointestinal bleeding episodes, presenting symptoms like hematemesis (vomiting of blood), hematochezia (passing fresh blood via the rectum), and melena (black, tarry stools). Other signs can include weight loss, anorexia, abdominal discomfort, jaundice, pruritus, altered mental status, and muscle cramps.
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...
118
 01:26
Peptic Ulcer Disease IV: Management
127
Medical treatment strategies for peptic ulcers encompass various methods. The primary goal of treatment is to diminish gastric acidity and strengthen mucosal defense mechanisms.
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current...
127
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
177
Peptic ulcer disease (PUD) presents with diverse symptoms depending on the location and severity of the ulcer. Clinical manifestations of peptic ulcer include dull pain and a burning sensation in the mid-epigastric region.
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
177