Related Experiment Video
Updated: Aug 19, 2025
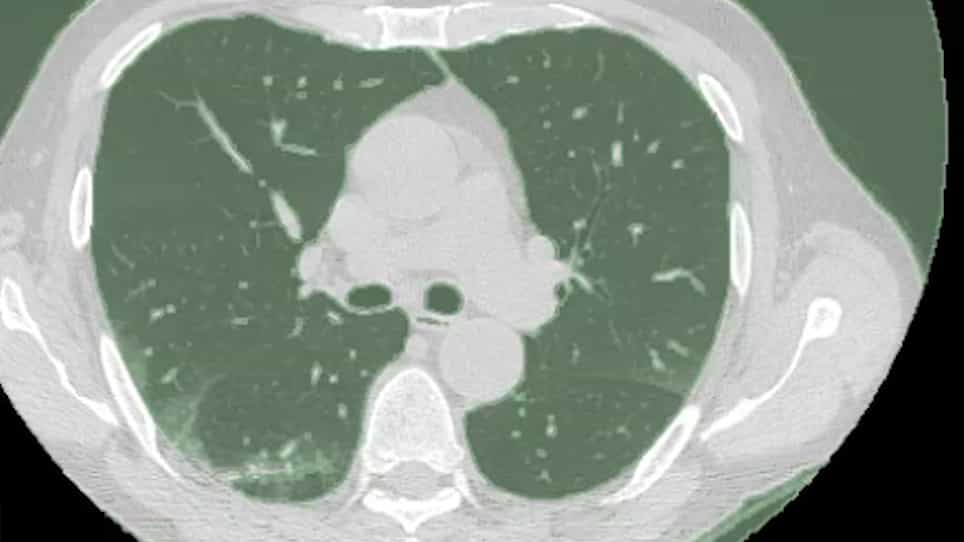

Lung CT Segmentation to Identify Consolidations and Ground Glass Areas for Quantitative Assesment of SARS-CoV Pneumonia
Published on: December 19, 2020
CT-based pathological lung opacities volume as a predictor of critical illness and inflammatory response severity in
Christian Alexander Torres-Ramirez1, David Timaran-Montenegro2, Yohana Sarahi Mateo-Camacho1
1Department of Radiology, Centro Médico Nacional 20 de Noviembre, Universidad Nacional Autonoma de Mexico (UNAM), México.

Objective:
The aim of the study was to assess the impact of CT-based lung pathological opacities volume on critical illness and inflammatory response severity of patients with COVID-19.
Methods:
A retrospective, single center, single arm study was performed over a 30-day period. In total, 138 patients (85.2%) met inclusion criteria. All patients were evaluated with non-contrast enhanced chest CT scan at hospital admission. CT-based lung segmentation was performed to calculate pathological lung opacities volume (LOV). At baseline, complete blood count (CBC) and inflammation response biomarkers were obtained. The primary endpoint of the study was the occurrence of critical illness, as defined as, the need of mechanical ventilation and/or ICU admission. Mann-Whitney U test was performed for univariate analysis. Logistic regression analysis was performed to determine independent predictors of critical illness. Spearman analysis was performed to assess the correlation between inflammatory response biomarkers serum concentrations and LOV.
Results:
Median LOV was 28.64% (interquartile range [IQR], 6.33-47.22%). Correlation analysis demonstrated that LOV was correlated with higher levels of D-dimer (r = 0.51, p < 0.01), procalcitonin (r = 0.47, p < 0.01) and IL6 (r = 0.48, p < 0.01). Critical illness occurred in 51 patients (37%). Univariate analysis demonstrated that inflammatory response biomarkers and LOV were associated with critical illness (p < 0.05). However, multivariate analysis demonstrated that only D-dimer and LOV were independent predictors of critical illness. Furthermore, a ROC analysis demonstrated that a LOV equal or greater than 60% had a sensitivity of 82.1% and specificity of 70.2% to determine critical illness with an odds ratio of 19.4 (95% CI, 4.2-88.9).
Conclusion:
Critical illness may occur in up to 37% of the patients with COVID-19. Among patients with critical illness, higher levels of inflammatory response biomarkers with larger LOVs were observed. Furthermore, multivariate analysis demonstrated that pathological lung opacities volume was an independent predictor of critical illness. In fact, patients with a pathological lung opacities volume equal or greater than 60% had 19.4-fold increased risk of critical illness.
More Related Videos

Related Concept Videos
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:29
Pneumonia II: Pathophysiology
 01:30
Pneumonia III: Complications and Assessment
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:25
Chronic Obstructive Pulmonary Disease-III: Symptoms and Complications.
Symptoms of COPD can be classified as primary or systemic. Primary symptoms relate to reduced airflow, while systemic or extrapulmonary symptoms relate to COPD's broader impact on the body.
Primary Symptoms of COPD: