Related Experiment Video
Updated: Aug 19, 2025

An Ivor Lewis Esophagectomy Designed to Minimize Anastomotic Complications and Optimize Conduit Function
Published on: April 17, 2020
Assessment of pyloric sphincter physiology after Ivor-Lewis esophagectomy using an endoluminal functional lumen
Stefanie Brunner1,2, Florian Lorenz2, Thomas Dratsch3
1Interdisciplinary Endoscopy Unit, Department of General, Visceral, Cancer and Transplantat Surgery, University Hospital of Cologne, Kerpener Street 62, 50937, Cologne, Germany.

Objective Of The Study:
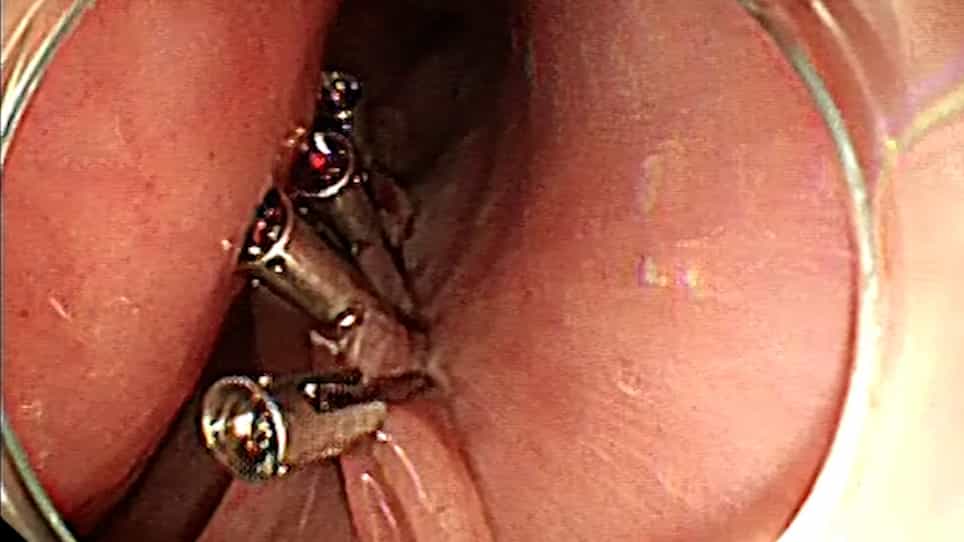
The most common functional complication after Ivor-Lewis esophagectomy is the delayed emptying of the gastric conduit (DGCE) for which several diagnostic tools are available, e.g. chest X-ray, upper esophagogastroduodenoscopy (EGD) and water-soluble contrast radiogram. However, none of these diagnostic tools evaluate the pylorus itself. Our study demonstrates the successful measurement of pyloric distensibility in patients with DGCE after esophagectomy and in those without it.
Methods And Procedures:
Between May 2021 and October 2021, we performed a retrospective single-centre study of all patients who had an oncological Ivor-Lewis esophagectomy and underwent our post-surgery follow-up programme with surveillance endoscopies and computed tomography scans. EndoFlip™ was used to perform measurements of the pylorus under endoscopic control, and distensibility was measured at 40 ml, 45 ml and 50 ml balloon filling.
Results:
We included 70 patients, and EndoFlip™ measurement was feasible in all patients. Successful application of EndoFlip™ was achieved in all interventions (n = 70, 100%). 51 patients showed a normal postoperative course, whereas 19 patients suffered from DGCE. Distensibility proved to be smaller in patients with symptoms of DGCE compared to asymptomatic patients. For 40 ml, 45 ml and 50 ml, the mean distensibility was 6.4 vs 10.1, 5.7 vs 7.9 and 4.5 vs 6.3 mm2/mmHg. The differences were significant for all three balloon fillings. No severe EndoFlip™ treatment-related adverse events occurred.
Conclusion:
Measurement with EndoFlip™ is a safe and technically feasible endoscopic option for measuring the distensibility of the pylorus. Our study shows that the distensibility in asymptomatic patients after esophagectomy is significantly higher than that in patients suffering from DGCE. However, more studies need to be conducted to demonstrate the general use of EndoFlip™ measurement of the pylorus after esophagectomy.

Related Concept Videos
 01:26
Imaging Studies III: Gastrointestinal Motility Studies and Virtual Colonoscopy
Radionuclide Testing
Radionuclide testing is a sophisticated medical technique for assessing gastrointestinal motility. It focuses on gastric emptying and colonic transit time. Radioactive markers track the movement of food through the digestive system, providing insights into gastrointestinal disorders.
In gastric emptying studies, a meal's liquid and...
 01:29
Endoscopic Procedures I: Esophagogastroduodenoscopy
During an EGD, the endoscope can be used to:
 01:28
Endoscopic Procedures III: Video Capsule Endoscopy
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...