Related Experiment Video
Updated: Aug 19, 2025
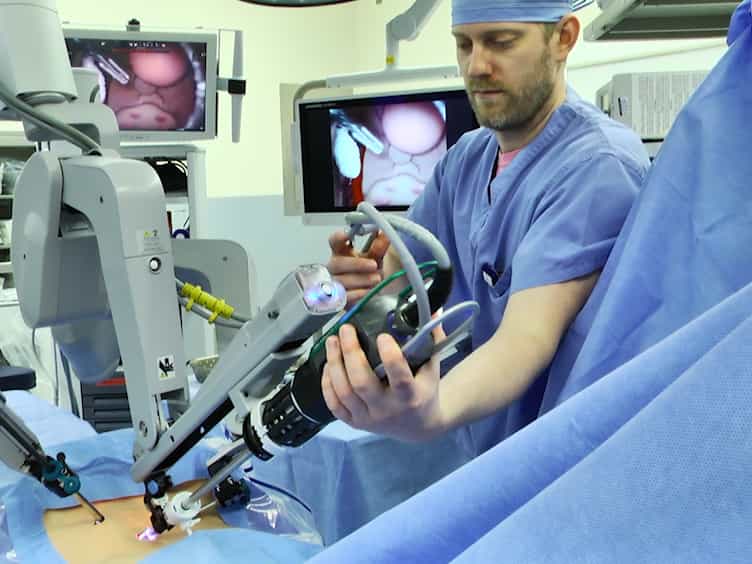

Emergency Undocking in Robotic Surgery: A Simulation Curriculum
Published on: May 20, 2018
Surgical Training for a Disaster: Preparation of Surgical Trainees for Victims of Conflict
Jace J P Franko1, Michael M Vu1, Michael E Parsons1
1Department of Surgery, Madigan Army Medical Center, Joint Base Lewis-McChord, WA 98431, USA.

Introduction:
With increasing global unrest and military physician shortages potentially leading to a surgeon draft, we sought to evaluate the readiness of graduating general surgery residents to care for casualties of war.
Materials And Methods:
We evaluated the National Data Reports of Surgery Case Logs for general surgery residents from 2009 to 2018 to quantify experience with key procedures that provide critical skills required for wartime surgery. Reported cases from the Accreditation Council for Graduate Medical Education for graduating residents from civilian and military residency programs were analyzed for 28 individual procedures determined to be critical for the care of combat casualties. These included central and peripheral vascular procedures, as well as neck, thoracic, abdominal, and peripheral interventions.
Results:
From 2009 to 2018, there has been a significant decrease in wartime-relevant cases by graduating residents. Notably, these include aorto-iliac/femoral bypasses (50% reduction; 7.1%/year; P < .001), femoral-popliteal bypasses (60% reduction; 6.9%/year; P < .001), femoral-femoral bypasses (30% reduction; 2.6%/year; P < .001), upper extremity amputations (50% reduction; 6.4%/year; P = .016), fasciotomies for trauma (50% reduction; 4.5%/year; P = .013), open repair of ruptured infrarenal aorto-iliac aneurysms (70% reduction; 5.8%/year; P < .001), repair of traumatic aorta or vena cava injuries (70% reduction; 7%/year; P = .007), carotid endarterectomies (40% reduction; 4%/year; P < .001), lung resections (40% reduction; 3.7%/year; P = .001), trauma splenectomies/splenorrhaphy (30% reduction; 2.9%/year; P < .001), and repair of traumatic liver lacerations (30% reduction; 2.5%/year; P = .036).
Conclusions:
Graduating general surgery residents has limited exposure to wartime critical skills due to a significant reduction in open vascular, head and neck, thoracic, and operative trauma cases. As the threat of global war persists and new graduates continue to deploy worldwide, residency training must be augmented to ensure adequate preparation in case a surgeon draft is required to fulfill demand for military surgeons.


Related Concept Videos
 01:16
Tracheostomy Care I: Pre-procedural Steps
Required Equipment
The equipment necessary for tracheostomy care includes:
 01:26
Kidney Transplant II: Surgical Procedure
 01:24
Treatment Strategies for Psychological Disorders
Psychological therapies focus on modifying emotions, thoughts, and behaviors through talking, interpreting, listening, rewarding, challenging, and modeling. Clinical psychologists, counselors, and social workers commonly practice psychotherapy. Clinical...
 01:26
Tracheostomy Suctioning I: Pre-Procedural Steps
Equipment Required
First, gather all necessary equipment: a sterile suction catheter, a sterile disposable container, sterile gloves, a towel or...
 01:26
Aneurysm III: Interprofessional Care
 01:27
Post-traumatic Stress Disorder
Symptoms and Behavioral Manifestations
A spectrum of distressing symptoms characterizes PTSD. Recurrent flashbacks, where individuals involuntarily relive traumatic events,...