Related Experiment Video
Updated: Aug 19, 2025
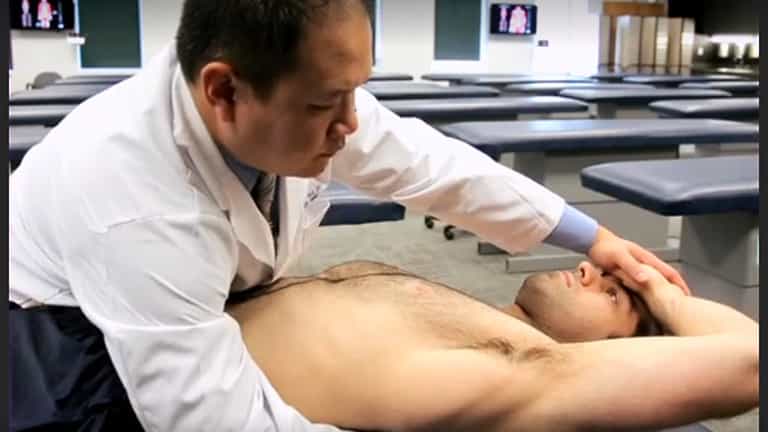

Osteopathic Manipulative Treatment as a Useful Adjunctive Tool for Pneumonia
Published on: May 6, 2014
Pediatric pneumomediastinum: Symptom-based management
Danielle Dougherty1, Kayla M Meyer2, Allison R Thompson3
1University of Michigan, Michigan Medicine, Department of Surgery, Section of Pediatric Surgery, 1540 E. Hospital Dr. Ann Arbor, MI 48109-4211, United States.

Insights
Pediatric spontaneous pneumomediastinum has a benign course. Reducing imaging like chest X-rays (CXRs) and esophagrams can decrease radiation exposure without affecting management.
Area of Science:
- Pediatric Pulmonology
- Pediatric Radiology
Background:
- Spontaneous pneumomediastinum in children typically follows a benign clinical course.
- Current diagnostic workup and management lack standardization, leading to varied imaging practices.
- This variability can result in unnecessary radiation exposure for pediatric patients.
Purpose of the Study:
- To evaluate the presentation, diagnostic workup, and management strategies for pediatric spontaneous pneumomediastinum.
- To identify factors influencing hospital stay duration and admission decisions.
- To assess the utility of common imaging modalities in the management of this condition.
Main Methods:
- Retrospective chart review of pediatric patients diagnosed with spontaneous pneumomediastinum over a 5-year period.
- Analysis of initial imaging studies, including chest X-ray (CXR) and chest computed tomography (CT) scans.
- Review of subsequent imaging, such as esophagrams, and correlation with presenting symptoms and diagnoses.
Main Results:
- Initial imaging varied, with chest X-ray (CXR) alone in 50%, chest CT alone in 18%, and both in 23% of patients.
- Esophagrams were performed in 31% of patients and were consistently negative for esophageal leaks.
- Presenting symptoms like shortness of breath and emesis were associated with longer hospital stays (>24 hours), while pain was associated with shorter stays (<24 hours).
- Respiratory infections and gastrointestinal issues were linked to inpatient admission.
Conclusions:
- Pediatric spontaneous pneumomediastinum management should be guided by presenting symptoms.
- Routine esophagrams are not indicated as they do not alter management and can be avoided.
- Reducing the frequency of chest X-rays (CXRs) can decrease radiation exposure in this pediatric population without compromising care.
Background:
Pediatric spontaneous pneumomediastinum is known to have a benign course. Despite this, there is no consensus or standardization for the workup and management. There are often a variety of imaging studies performed for patients with similar presentations.
Methods:
This is a retrospective chart review evaluating the presentation, workup, and management of all pediatric patients with a primary diagnosis of spontaneous pneumomediastinum over a 5-year period at a children's hospital.
Results:
Of the 62 patients, the initial workup consisted of either a chest x-ray (CXR) only (n = 31, 50%), a chest computed tomography scan only (n = 11, 18%) or both (n = 14, 23%); additionally, some patients came with 'other' imaging only (n = 3, 5%) or no imaging (n = 3, 5%). Twenty-seven patients (44%) underwent an additional CXR and 19 (31%) underwent an esophagram. All esophagrams were negative for an esophageal leak. A presenting symptom of pain was associated with a hospital stay of less than 24 h (p = 0.008) while shortness of breath (p = 0.0005) and emesis (p = 0.0006) were associated with a hospital stay of greater than 24 h. Associated diagnoses of respiratory infections (p = 0.02) and gastrointestinal issues (p = 0.006), such as hyperemesis, were associated with inpatient admission.
Conclusion:
Pediatric patients with spontaneous pneumomediastinum benefit from evaluation, management, and treatment based on their presenting symptoms. There is an opportunity to decrease unnecessary radiation exposure in this patient population with fewer CXRs and avoidance of esophagrams, neither of which alter management.
Level Of Evidence:
Level III.
More Related Videos
 05:50
International Expert Consensus and Recommendations for Neonatal Pneumothorax Ultrasound Diagnosis and Ultrasound-guided Thoracentesis Procedure
Published on: March 12, 2020
 06:15
Protocol and Guidelines for Point-of-Care Lung Ultrasound in Diagnosing Neonatal Pulmonary Diseases Based on International Expert Consensus
Published on: March 6, 2019
Related Concept Videos
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:30
Pneumonia V: Nursing management and Prevention
The nurse must practice strict medical asepsis and adhere to infection control guidelines to minimize healthcare-associated infections.
Enhance airway patency
Position the patient correctly to facilitate drainage of the affected lung segments. Manual or mechanical percussion and vibration can also be employed....
 01:28
Pleural Effusion II: Symptoms and Management
A pleural effusion is the abnormal collection of fluid between the parietal and visceral pleura layers of tissue that form the lining of the lungs and chest cavity. It can occur independently or due to surrounding parenchymal diseases, such as infection, malignancy, or inflammatory conditions.
Clinical Manifestations:
 01:28
Pneumonia IV: Management
Bacterial Pneumonia Treatment
For bacterial pneumonia, antibiotics serve as the cornerstone of therapy. Initial treatment often begins with empirical antibiotics, tailored to the anticipated causative organism and adjusted based on culture results. Key antibiotic choices include:
 01:30
Pneumonia III: Complications and Assessment
 01:17
Pulmonary Cycle: Exhalation