Related Experiment Video
Updated: Aug 19, 2025

Optimizing Isolation and Purification of Murine Glomerular Mesangial Cells
Published on: March 7, 2025
Gut-kidney axis in IgA nephropathy: Role on mesangial cell metabolism and inflammation
Mateus Justi Luvizotto1, Luísa Menezes-Silva2, Viktoria Woronik1
1Department of Nephrology, Faculty of Medicine, University of Sao Paulo, São Paulo, Brazil.

Abstract:
IgA Nephropathy (IgAN) is the commonest primary glomerular disease around the world and represents a significant cause of end-stage renal disease. IgAN is characterized by mesangial deposition of IgA-immune complexes and mesangial expansion. The pathophysiological process includes an abnormally glycosylated IgA1, which is an antigenic target. Autoantibodies specifically recognize galactose-deficient IgA1 forming immune complexes that are amplified in size by the soluble IgA Fc receptor CD89 leading to deposition in the mesangium through interaction with non-classical IgA receptors. The local production of cytokines promotes local inflammation and complement system activation, besides the stimulation of mesangial proliferation. The spectrum of clinical manifestations is quite variable from asymptomatic microscopic hematuria to rapidly progressive glomerulonephritis. Despite all the advances, the pathophysiology of the disease is still not fully elucidated. The mucosal immune system is quoted to be a factor in triggering IgAN and a "gut-kidney axis" is proposed in its development. Furthermore, many recent studies have demonstrated that food intake interferes directly with disease prognosis. In this review, we will discuss how mucosal immunity, microbiota, and nutritional status could be interfering directly with the activation of intrinsic pathways of the mesangial cells, directly resulting in changes in their function, inflammation and development of IgAN.
More Related Videos


Related Concept Videos
 01:28
Chronic Kidney Disease III: Interprofessional Care
 01:29
Acute Kidney Injury II: Pathophysiology
 01:29
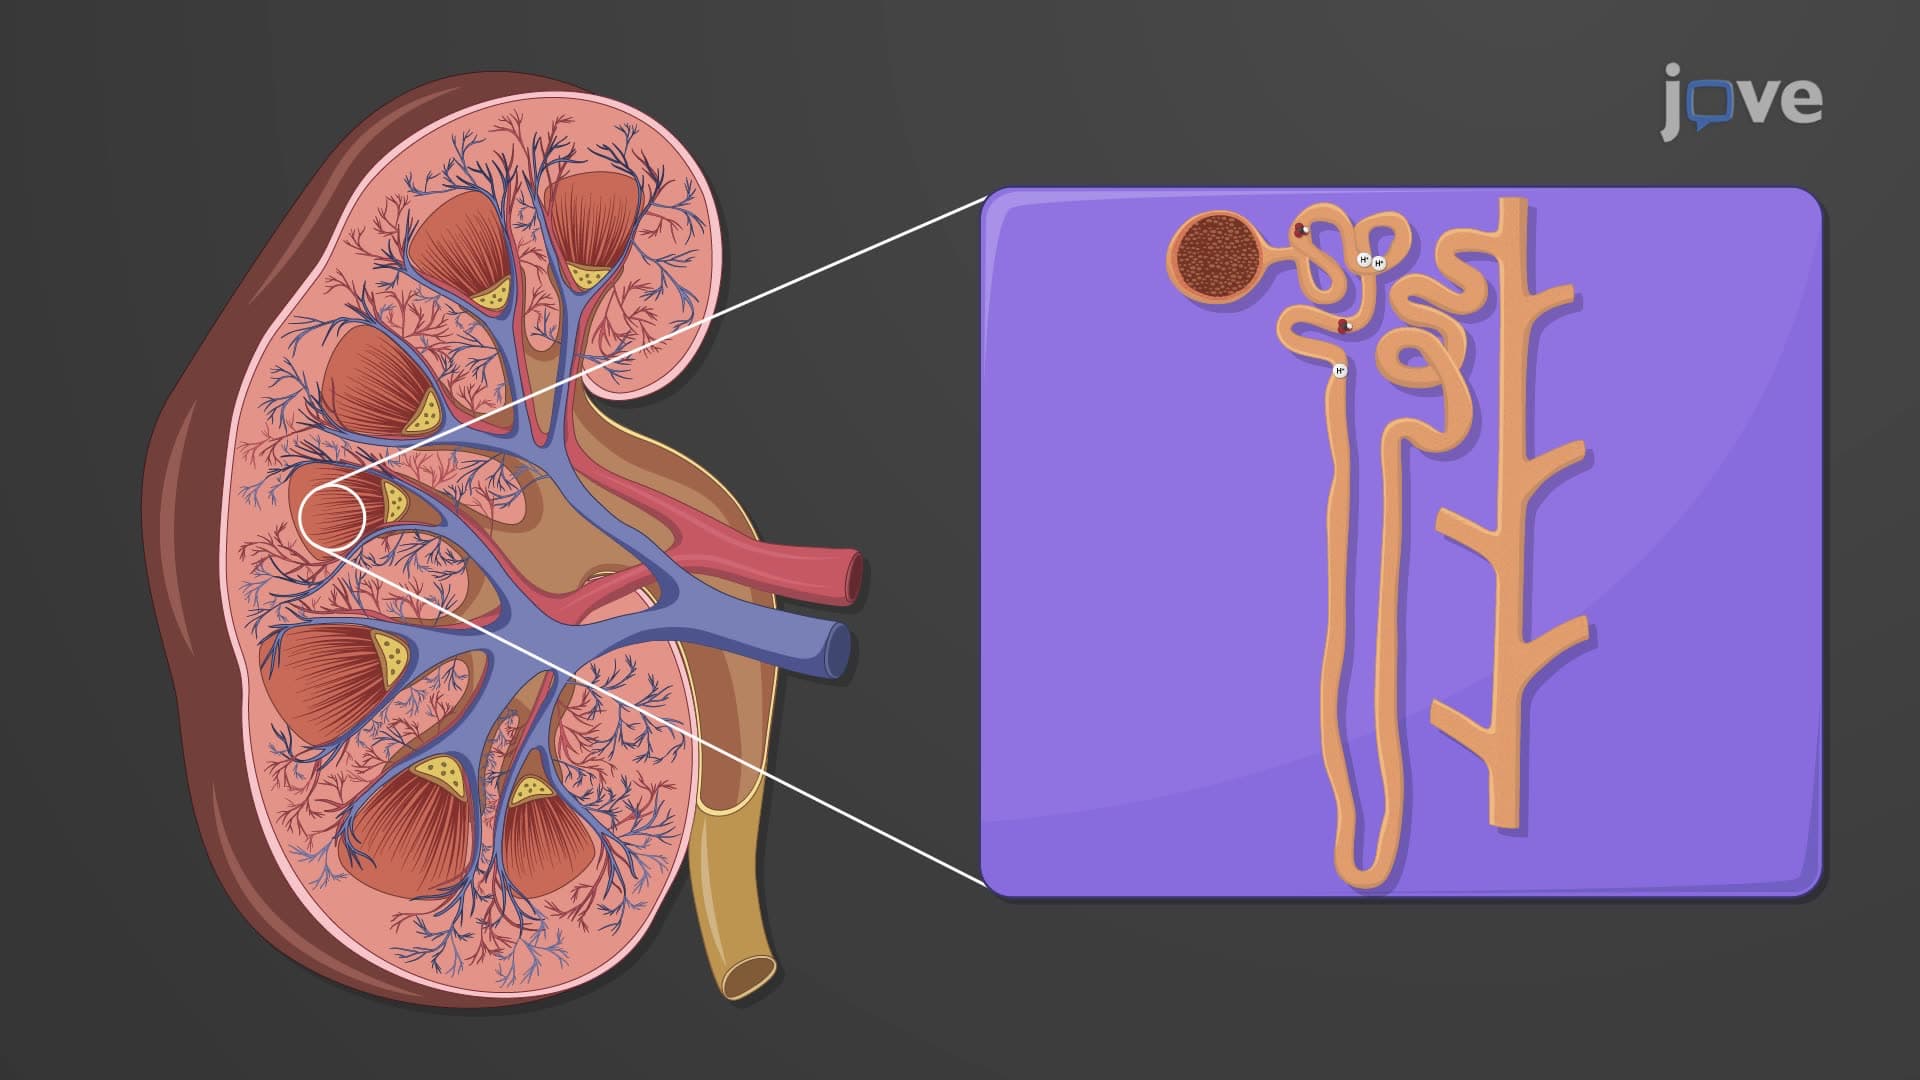
Renal Regulation of Acid-Base Balance
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...
 01:24
Chronic Kidney Disease II: Clinical Manifestations
 01:29
Acute Kidney Injury III: Clinical Manifestations
 01:20
Acute Kidney Injury V: Interprofessional Care