Related Experiment Video
Updated: Aug 18, 2025
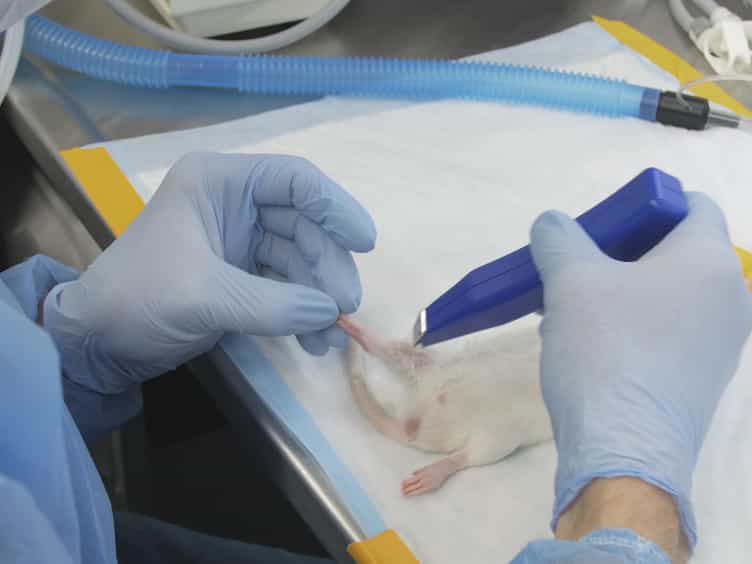
A Rat Tibial Growth Plate Injury Model to Characterize Repair Mechanisms and Evaluate Growth Plate Regeneration Strategies
Published on: July 4, 2017
Incidence of growth disturbance after distal tibia physeal fracture in children
Hui Chen1,2,3, Zhao Chen4,5, Peisheng Chen6
1Department of Pediatric Orthopedics, Fujian Maternity and Child Health Hospital College of Clinical Medicine for Obstetrics & Gynecology and Pediatrics, Fujian Medical University, Fuzhou, 350001, China. fzch0321@163.com.

Background:
To analyze the growth disturbance after distal tibia physeal fracture in children.
Methods:
Data about children with distal tibia physeal fractures between September 2015 to September 2018 were collected, including age, gender, affected side, Salter-Harris classification, initial maximal displacement, with or without fibula fracture, open or closed reduction, the method of fixation, time to surgery, blood loss, duration of operation, and complications. Patients were placed in the growth disturbance group when leg length discrepancy was equal to or greater than 1.5 cm, or when they had more than 5 degrees of varus or valgus deformity. Others were placed in the no-growth disturbance group.
Results:
A total of 143 patients (96 boys and 47 girls) were enrolled in this study. The length of the follow-up periods averaged 29.34 ± 7.46 months (26 to 61 months). Among the total of 143 patients, the incidence of growth disturbance was 15.39% (22/143). The no-growth disturbance group consisted of 121 patients (84 boys and 37 girls), with a mean age of 11.50 ± 3.20 years, and there were 68, 52, and 1 injuries to the left, right, and bilateral sides, respectively. The average maximal displacement was 5.51 ± 3.18 mm, and 27.27% (33/121) of patients also had a fibula fracture. The growth disturbance group contained 22 patients (12 boys and 10 girls) with a mean age of 9.32 ± 3.56 years, and there were 12, 10, and 0 injuries on the left, right, and bilateral sides, respectively. The average maximal displacement was 5.77 ± 4.89 mm, and 45.45% (10/22) of patients also had a fibula fracture. There was a significant difference in age (p = 0.004) and fibula fracture (p = 0.011) between the two groups. More patients had Salter-Harris types III and IV fractures in the growth disturbance group than in the no-growth disturbance group (p = 0.043).
Conclusions:
Children with Salter-Harris types III and IV fractures, younger children, and children with fibula fractures all have a higher incidence of growth disturbance after distal tibia physeal fractures.
Level Of Evidence:
Level III-Prognostic study.
More Related Videos


Related Concept Videos
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:27
Growth of Cartilage and Bone Tissue