Related Experiment Video
Updated: Aug 17, 2025
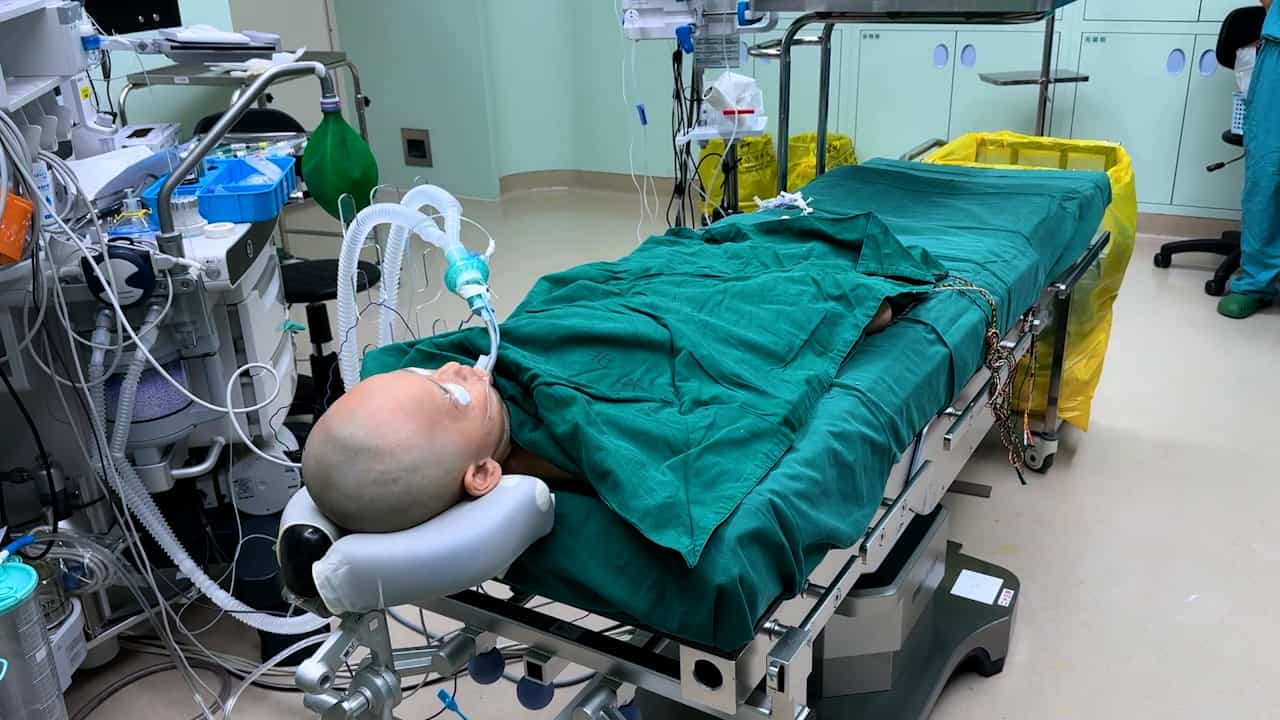

Author Spotlight: Studying Clinical Characters and Epilepsy Outcomes After Frontal Disconnection in Patients with MOGHE
Published on: August 16, 2024
Which centers should be authorized to treat craniosynostosis? A plea for quality and not for quantity
A Lassausaie1, F Abed Rabbo2, I Barthélémy1
1Service de Chirurgie Maxillofaciale, CHU Clermont-Ferrand, Clermont-Ferrand, F-63000, France.

Background:
In centers for craniosynostosis surgery, the volume of activity does not necessarily reflect the quality of the treatment.
Objective:
Our aim was to analyze a retrospective series of patients over a period of 6 years in a low-volume craniosynostosis surgery center, and to study indicators that reflect the quality of treatment.
Patients And Methods:
The analysis included all patients who underwent a craniofacial surgery for all forms of craniosynostosis during the period 2012-2017 (annual follow-up for 4 years). Data on the type of synostosis, sex, age, weight, type of surgery, duration of surgery, blood transfusion, postinterventional care, and total length of hospital stay were collected. Medical and surgical complications were recorded using the Leeds classification.
Results:
Overall, 42 patients (33 male; 23 cases of scaphocephaly, 13 cases of trigonocephaly, 4 cases of coronal plagiocephaly, 1 case of lambdoid plagiocephaly, and 1 case of brachycephaly) underwent craniofacial surgery with a median age of 7.4 months [4.8; 10.4] and a mean weight of 8.40 ± 1.92 kg at surgery. The median hospital stay was 7 days [6;7] with 1 day in the postinterventional care unit for 83% of patients. The global complication rate was 12% (95% CI: 4%-26%) with three minor cutaneous and two major (cardiovascular and septic) complications.
Conclusion:
Complication rates reflect the quality of care in a center that treats craniosynostosis much more than do the number of procedures, mean hospital stay, and blood transfusion rates. It is essential to define new indicators capable of measuring the quality of life linked to surgical procedures and of using them to assess the competence of a center.


Related Concept Videos
 01:22
Sutures of the Skull
Sutures are immobile joints between adjacent bones of the skull. The narrow gap between the bones is filled with dense, fibrous connective tissue that unites the bones. The long sutures located between the skull bones are not straight but instead follow irregular, tightly twisting paths. These twisting lines tightly...
 01:30
Specialized Care Centers and Settings-I
Daycare centers
They provide several functions. Some facilities care for healthy newborns and children whose parents work, while others are medically focused and care for...
 01:19
Cranial and Spinal Meninges
Cranial Meninges
These meningeal layers cover the cranium. The dura mater is the outermost layer of cranial meninges. It is a thick and durable membrane of dense...
 01:26
Aneurysm III: Interprofessional Care
 01:30
Specialized Care Centers and Settings-II
Rural health centers are specialized care facilities in remote locations with very few medical personnel. The primary care providers who run the centers are mostly Registered Nurse Practitioners. Here, emergency treatment is provided to critically ill or injured patients before they are transferred to the closest hospital. Fortunately, due to advancement in technology, many rural healthcare facilities and professionals have easy access to diagnostic and treatment...
 01:14
Cranial Bones: Superior and Posterior View
The frontal bone is the single bone that forms the forehead. At its anterior midline, between the eyebrows, there is a slight depression called the glabella. The frontal bone also forms the supraorbital margin of the orbit. Near the middle of this margin is the supraorbital foramen, the opening that provides passage for a sensory nerve to the forehead. The frontal bone is thickened just above each supraorbital margin,...