Related Experiment Video For Cytology
Updated: Aug 17, 2025
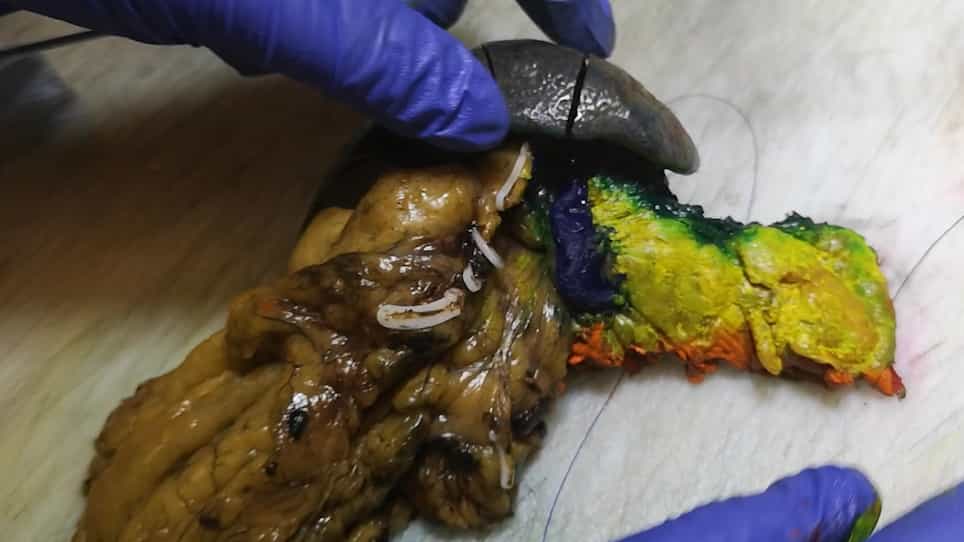

DIPLOMA Approach for Standardized Pathology Assessment of Distal Pancreatectomy Specimens
Published on: February 1, 2020
The World Health Organization Reporting System for Pancreaticobiliary Cytopathology
Martha B Pitman1, Barbara A Centeno2, Michelle D Reid3
1Department of Pathology, Massachusetts General Hospital, Harvard Medical School, Boston, Massachusetts, USA.

Abstract:
The World Health Organization (WHO), the International Academy of Cytology, and the International Agency for Research on Cancer, with expert contributors from around the world, present an international approach to standardized reporting of pancreaticobiliary cytopathology. This reporting system is one of the first in a series from various body sites that mirror the WHO Classification of Tumours series and provides an evidence-based terminology system with associated risk of malignancy and diagnostic management recommendation per diagnostic category. The WHO Reporting System for Pancreaticobiliary Cytopathology (WHO system) revises the Papanicolaou Society of Cytopathology (PSC) system for Reporting Pancreaticobiliary Cytology published in 2015 and replaces the six-tiered system with a seven-tiered system: "insufficient/inadequate/nondiagnostic"; "benign (negative for malignancy)," "atypical," "pancreaticobiliary neoplasm of low risk/low grade," "pancreatic neoplasm of high risk/high grade," "suspicious for malignancy," and "malignant." The principal differences between the WHO and the PSC systems revolve around the classification of neoplasia. In the PSC system, there was a single category for "neoplastic" lesions that includes two groups, one for "benign neoplasms" [primarily serous cystadenoma] and one named "other," dominated by premalignant intraductal neoplasms (primarily intraductal papillary mucinous neoplasms) and low-grade malignant neoplasms [pancreatic neuroendocrine tumors (PanNETs) and solid pseudopapillary neoplasms (SPNs)]. In the WHO system, benign neoplasms with virtually no risk of malignancy are included in the "benign" category and low-grade malignancies (PanNET and SPN) are included in the "malignant" category, as per the WHO Classification of Digestive System Tumours, thus leaving in the "neoplasm" category primarily those noninvasive premalignant lesions of the ductal system. These neoplasms are divided by the cytomorphological grade of the epithelium into low risk/low-grade and high risk/high-grade, with distinctly different risks of malignancy. As with the PSC system, the WHO system advocates close correlation with imaging and encourages incorporation of ancillary testing into the final diagnosis, such as biochemical (CEA and amylase) and molecular testing of cyst fluid and bile duct brushings. Key diagnostic cytopathological features of specific lesions or neoplasms, ancillary studies for diagnostic and prognostic evaluation, and implications of diagnosis for patient care and management are discussed. In addition, the WHO system includes reporting and diagnostic management options that recognize the variations in the availability of diagnostic and prognostic ancillary testing modalities in low- and middle-income countries, where cytopathology is particularly useful and is increasingly available in the absence of histopathological services.

Related Concept Videos
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:26
Diseases of the Liver and Gallbladder
Cirrhosis is characterized by the scarring of hepatic lobules in the liver, which are replaced by fibrous tissue, affecting the liver's normal functioning. NAFLD, on the other hand, is caused by an excessive build-up of fat in the liver, not...
 01:26
Endoscopic Procedures V: ERCP
Patient...