Related Experiment Video
Updated: Aug 17, 2025


Non-fluoroscopic Catheter Tracking for Fluoroscopy Reduction in Interventional Electrophysiology
Published on: May 26, 2015
Mechanisms of persistent atrial fibrillation and recurrences within 12 months post-ablation: Non-invasive mapping
Ramya Vijayakumar1,2, Mitchell N Faddis2,3, Phillip S Cuculich2,3
1Department of Surgery, Washington University School of Medicine, St. Louis, MO, United States.

Introduction:
Catheter ablation of persistent AF has not been consistently successful in terminating AF or preventing arrhythmia recurrences. Non-invasive Electrocardiographic Imaging (ECGI) can help to understand recurrences by mapping the mechanisms of pre-ablation AF and comparing them with the patterns of recurrent arrhythmias in the same patient.
Methods:
Seventeen persistent AF patients underwent ECGI before their first catheter ablation. Time-domain activation maps and phase progression maps were obtained on the bi-atrial epicardium. Location of arrhythmogenic drivers were annotated on the bi-atrial anatomy. Activation and phase movies were examined to understand the wavefront dynamics during AF. Eight patients recurred within 12 months of ablation and underwent a follow-up ECGI. Driver locations and movies were compared for pre- and post-ablation AF.
Results:
A total of 243 focal drivers were mapped during pre-ablation AF. 62% of the drivers were mapped in the left atrium (LA). The pulmonary vein region harbored most of the drivers (43%). 35% of the drivers were mapped in the right atrium (RA). 59% (10/17) and 53% (9/17) of patients had repetitive sources in the left pulmonary veins (LPV) and left atrial appendage (LAA), and the lower half of RA, respectively. All patients had focal drivers. 29% (5/17) of patients had macro-reentry waves. 24% (4/17) of patients had rotors. Activation patterns during persistent AF varied from single macro-reentry to complex activity with multiple simultaneous wavefronts in both atria, resulting in frequent wave collisions. A total of 76 focal driver activities were mapped in 7/8 patients during recurrence. 59% of the post-ablation AF drivers were mapped in the LA. The pulmonary vein region harbored 50% of total drivers. 39% of sources were mapped in the RA. AF complexity remained similar post-ablation. 58% (44/76) of pre-ablation sources persisted during recurrence. 38% (3/8) of patients had macro-reentry and one patient had rotors.
Conclusion:
ECGI provides patient-specific information on mechanisms of persistent AF and recurrent arrhythmia. More than half pre-ablation sources repeated during post-ablation recurrence. This study provides direct evidence for drivers that persist days and months after the ablation procedure. Patient-tailored bi-atrial ablation is needed to successfully target persistent AF and prevent recurrence. ECGI can potentially predict recurrence and assist in choice of therapy.


Related Concept Videos
 01:25
ECG Interpretation of Arrhythmias II: Atrial, Junctional and Ventricular Arrhythmias
 01:28
Mechanism of Cardiac Arrhythmias
 01:30
Dysrhythmias V: Evaluating Dysrhythmias
 01:25
Correlation between ECG and Cardiac Cycle
A cardiac action potential originates in the SA node and spreads throughout the atria and the AV node in approximately 0.03 seconds. This results in the P wave in an ECG and triggers atrial contraction. The action potential is then briefly slowed at the AV node, allowing the atria to contract and fill the ventricles with blood before...
 01:19
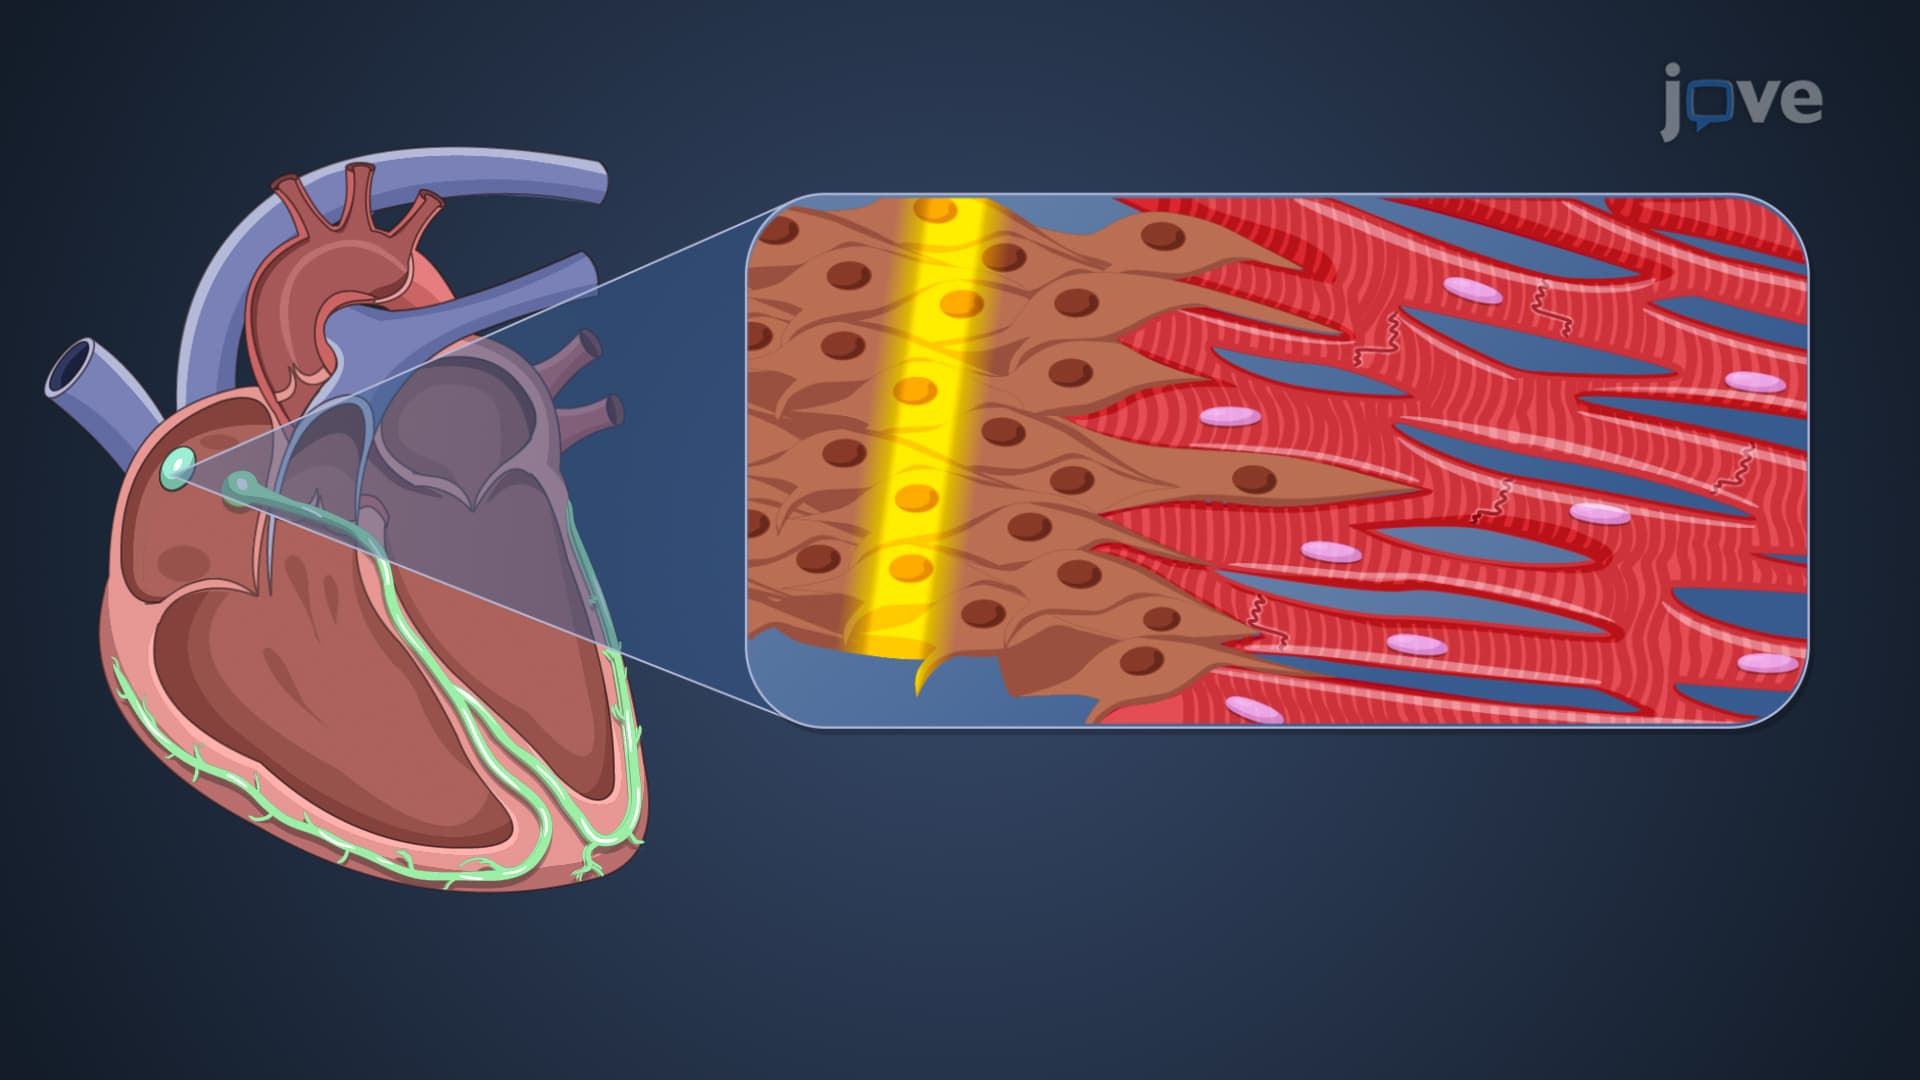
Electrophysiology of Normal Cardiac Rhythm
 01:30
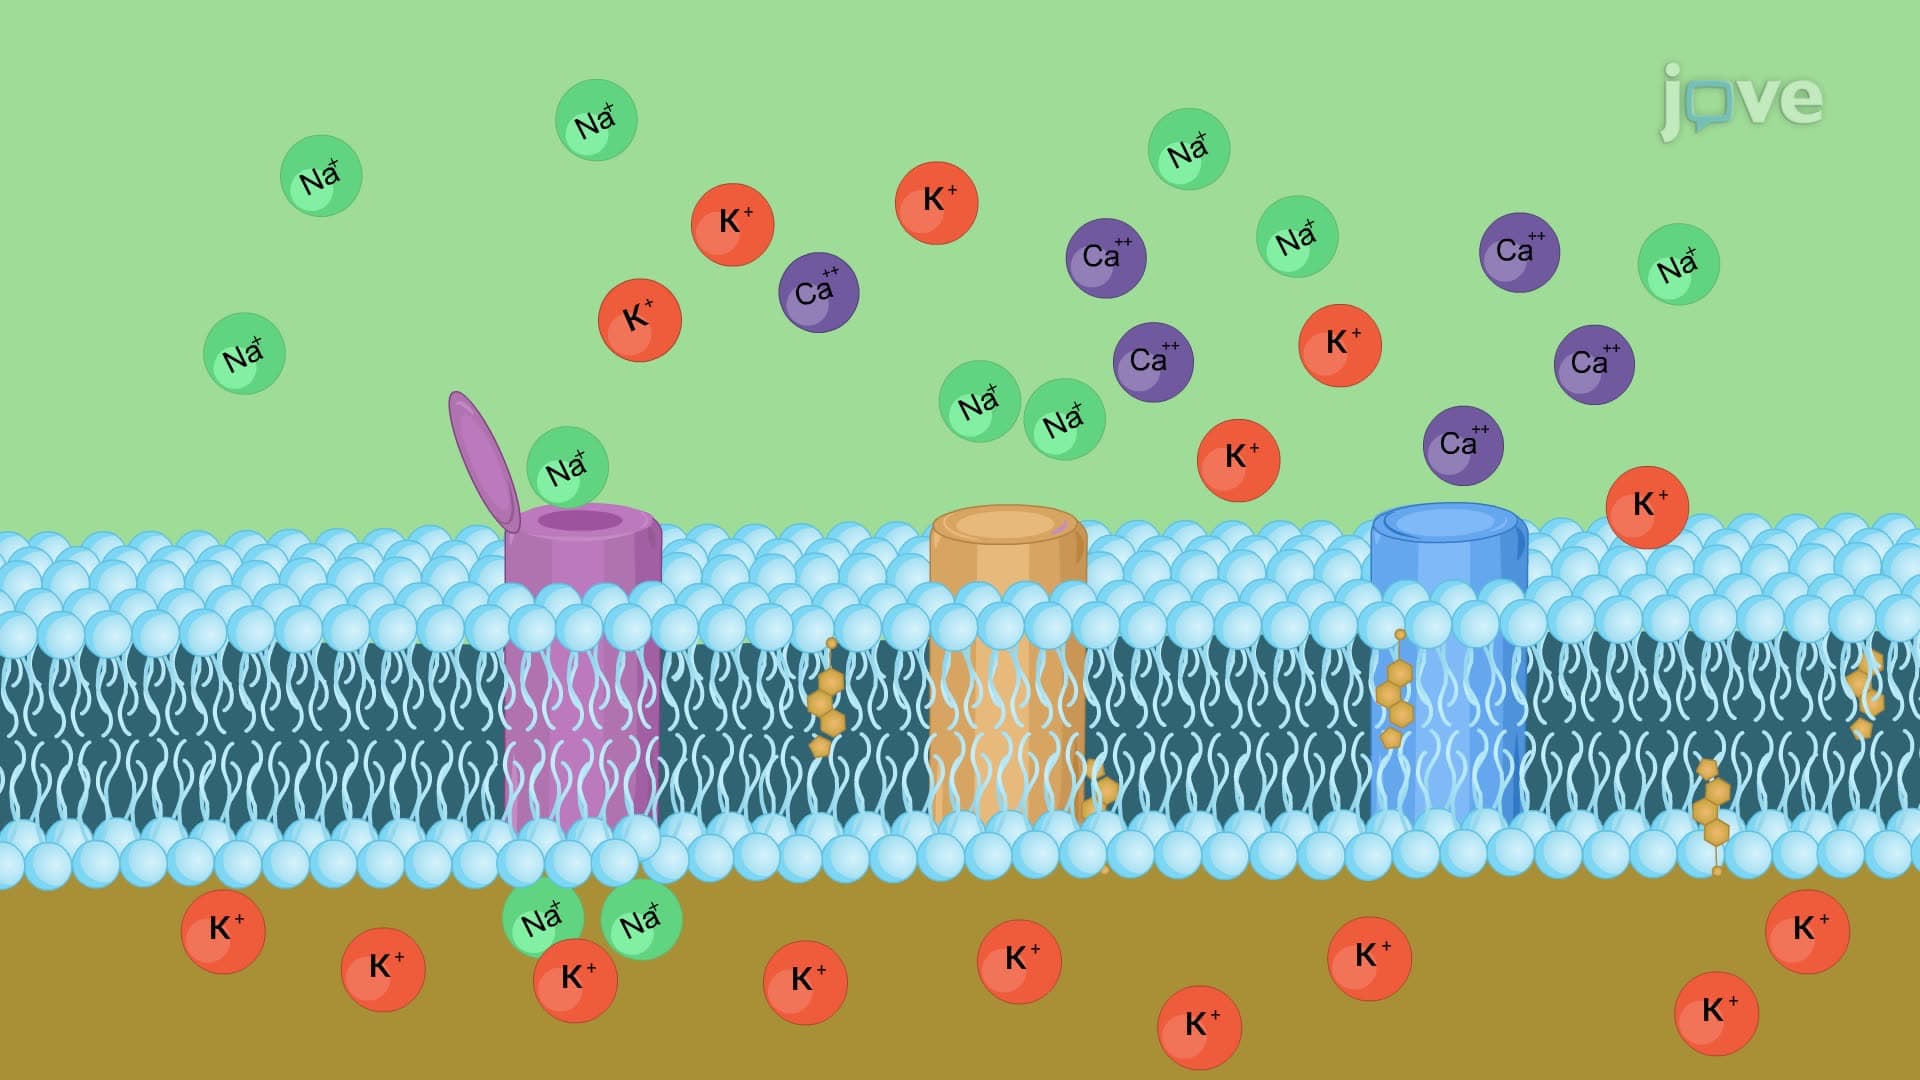
Cardiac Action Potential
The cardiac action potential process involves a series of phases characterized by the movement of ions across the cardiac cell membranes, leading to the depolarization and repolarization of the cardiac myocytes.
Ionic Basis of Cardiac Action Potentials