Related Experiment Video
Updated: Aug 16, 2025
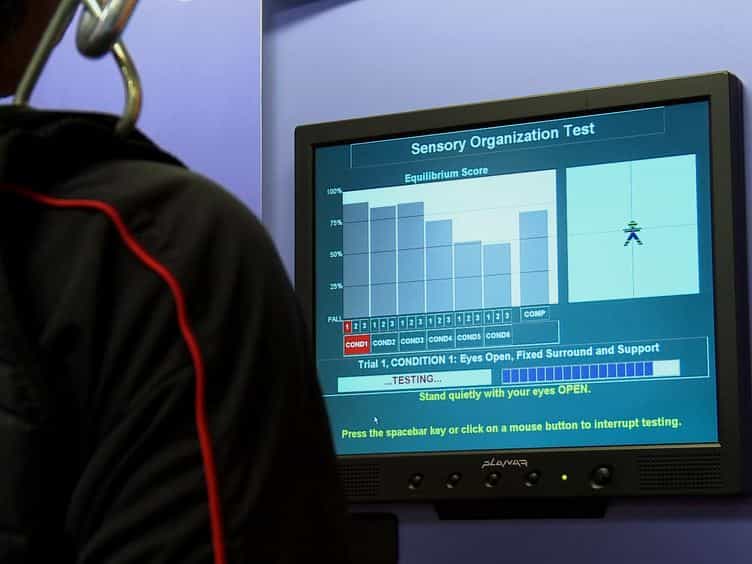

Computerized Dynamic Posturography for Postural Control Assessment in Patients with Intermittent Claudication
Published on: December 11, 2013
Provider ankle brachial index and wound classification teaching as part of a comprehensive limb preservation outreach
Kathryn DiLosa1, Christina Brown1, Ganesh Rajasekar1
1Department of Surgery, University of California, Davis Health, Sacramento, CA.

Objective:
Utilization of evidence-based specialty guidelines is low in primary care settings. Early use of ankle-brachial index (ABI) testing and a validated wound classification system allows prompt referral of patients for specialty care. We implemented a program to teach providers ABI testing and the use of the Wound, Ischemia, and foot Infection (WIfI) classification tool. Here, we report program outcomes and provider perceptions.
Methods:
Physicians and non-physicians from wound care centers, nursing and physician education programs, primary care offices, and federally qualified health centers were invited to participate in the educational program teaching ABI testing and the use of the WIfI tool. Pretest and posttest responses and intention to use content in the future were assessed with descriptive statistics.
Results:
A total of 101 subjects completed the ABI module, and 84 indicated their occupation (59 physicians, 25 non-physicians). Seventy-nine subjects completed the WIfI module, and 89% indicated their occupation (50 physicians, 20 non-physicians). Physicians had lower pre-test knowledge scores for the ABI module than non-physicians (mean scores of 7.9 and 8.2, respectively). Both groups had improved knowledge scores on the post-test (physicians, 13.4; non-physicians, 13.8; P < .001). Non-physicians in practice longer than 10 years at wound care centers had the lowest baseline knowledge scores, whereas physicians in practice for over 10 years had the highest. In the ABI module, the largest knowledge gap included accurately calculating the ABI, followed by the correct use of the Doppler, and management of incompressible vessels. For the WIfI module, providers struggled to accurately score patients based on wound classification. The greatest barriers to the implementation of ABI testing were the availability of trained personnel, followed by limited time for testing. Barriers to the use of the WIfI tool for physicians included lack of time and national guideline support. For non-physicians, the most notable barrier was a lack of training.
Conclusions:
Provider understanding of ABI and WIfI tools are limited in wound care centers, primary care offices, and federally qualified health centers. Further barriers include a lack of training in the use of tools, limited potential for point-of-care testing reimbursement, and insufficient dissemination of WIfI guidelines. Such barriers discourage widespread adoption and result in delayed diagnosis of arterial insufficiency.
More Related Videos
 07:25
Predicting Amputation using Local Circulating Mononuclear Progenitor Cells in Angioplasty-treated Patients with Critical Limb Ischemia
Published on: September 22, 2020
 08:16
High-Resolution Three-Dimensional Imaging of the Footpad Vasculature in a Murine Hindlimb Gangrene Model
Published on: March 16, 2022
Related Concept Videos
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management
 01:26
Peripheral Artery Disease IV: Nursing Management
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:27
Peripheral Artery Disease III: Interprofessional Care
 01:11
Assessing Blood pressure in the Leg
Preparation:
 01:27
Assessment of the Cardiovascular System III: Palpation
Jugular Venous Pressure (JVP) Measurement
Position the patient at a thirty- to forty-five-degree angle or in a semi-fowler's position. Look for the highest point of pulsation in the internal jugular vein and measure the vertical distance to the angle of Loius or sternal angle. A normal JVP is 3-4 cm above...