COVID-19 Lessons Learned: Response to the Anticipated Ventilator Shortage
Related Experiment Video
Updated: Aug 16, 2025
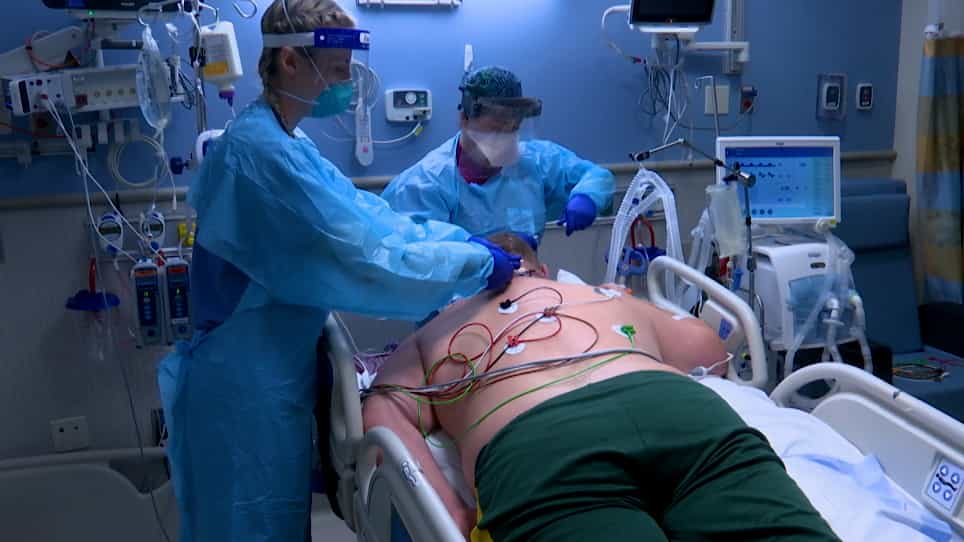
An Educational Video Demonstration of How to Prone a Critically Ill Intubated Patient
Published on: November 30, 2022
Richard D Branson1, Dario Rodriquez2
1Division of Trauma/Critical Care, Department of Surgery, University of Cincinnati, Cincinnati, Ohio. richard.branson@uc.edu.

Abstract:
Early in the COVID-19 pandemic predictions of a worldwide ventilator shortage prompted a worldwide search for solutions. The impetus for the scramble for ventilators was spurred on by inaccurate and often unrealistic predictions of ventilator requirements. Initial efforts looked simply at acquiring as many ventilators as possible from national and international sources. Ventilators from the Strategic National Stockpile were distributed to early hotspots in the Northeast and Northwest United States. In a triumph of emotion over logic, well-intended experts from other industries turned their time, talent, and treasure toward making a ventilator for the first time. Interest in shared ventilation (more than one patient per ventilator) was ignited by an ill-advised video on social media that ignored the principles of gas delivery in deference to social media notoriety. With shared ventilation, a number of groups mistook a physiologic problem for a plumbing problem. The United States government invoked the Defense Production Act to push automotive manufacturers to partner with existing ventilator manufacturers to speed production. The FDA granted emergency use authorization for "splitters" to allow shared ventilation as well as for ventilators and ancillary equipment. Rationing of ventilators was discussed in the lay press and medical literature but was never necessary in the US. Finally, planners realized that staff with expertise in providing mechanical ventilation were the most important shortage. Over 200,000 ventilators were purchased by the United States government, states, cities, health systems, and individuals. Most had little value in caring for patients with COVID-19 ARDS. This paper attempts to look at where miscalculations were made, with an eye toward what we can do better in the future.

Related Concept Videos
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:29
Mechanical Ventilation I: Indication and Settings
 01:14
Ventilatory Modes
There are three ventilatory modes: full support, partial support, and spontaneous. These are described below.
Full Support Modes
Full support modes include controlled mechanical ventilation, continuous mandatory...
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation...
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include: