Related Experiment Video
Updated: Aug 15, 2025

Studying Cavitation Enhanced Therapy
Published on: April 9, 2021
Regularity and mechanism of fake crackle noise in an electronic stethoscope
Peitao Ye1, Qiasheng Li1, Wenhua Jian1
1National Center for Respiratory Medicine, State Key Laboratory of Respiratory Disease, National Clinical Research Center for Respiratory Disease, Guangzhou Institute of Respiratory Health, First Affiliated Hospital of Guangzhou Medical University, Guangzhou, China.

Abstract:
Background: Electronic stethoscopes are widely used for cardiopulmonary auscultation; their audio recordings are used for the intelligent recognition of cardiopulmonary sounds. However, they generate noise similar to a crackle during use, significantly interfering with clinical diagnosis. This paper will discuss the causes, characteristics, and occurrence rules of the fake crackle and establish a reference for improving the reliability of the electronic stethoscope in lung auscultation. Methods: A total of 56 participants with healthy lungs (no underlying pulmonary disease, no recent respiratory symptoms, and no adventitious lung sound, as confirmed by an acoustic stethoscope) were enrolled in this study. A 30-s audio recording was recorded from each of the nine locations of the larynx and lungs of each participant with a 3M Littmann 3200 electronic stethoscope, and the audio was output in diaphragm mode and auscultated by the clinician. The doctor identified the fake crackles and analyzed their frequency spectrum. High-pass and low-pass filters were used to detect the frequency distribution of the fake crackles. Finally, the fake crackle was artificially regenerated to explore its causes. Results: A total of 500 audio recordings were included in the study, with 61 fake crackle audio recordings. Fake crackles were found predominantly in the lower lung. There were significant differences between lower lung and larynx (p < 0.001), lower lung and upper lung (p = 0.005), lower lung and middle lung (p = 0.005), and lower lung and infrascapular region (p = 0.027). Furthermore, more than 90% of fake crackles appeared in the inspiratory phase, similar to fine crackles, significantly interfering with clinical diagnosis. The spectral analysis revealed that the frequency range of fake crackles was approximately 250-1950 Hz. The fake crackle was generated when the diaphragm of the electronic stethoscope left the skin slightly but not completely. Conclusion: Fake crackles are most likely to be heard when using an electronic stethoscope to auscultate bilateral lower lungs, and the frequency of a fake crackle is close to that of a crackle, likely affecting the clinician's diagnosis.
More Related Videos
 10:50
Behavioral Determination of Stimulus Pair Discrimination of Auditory Acoustic and Electrical Stimuli Using a Classical Conditioning and Heart-rate Approach
Published on: June 6, 2012
 05:30
Crack Monitoring in Resonance Fatigue Testing of Welded Specimens Using Digital Image Correlation
Published on: September 29, 2019
Related Concept Videos
 01:15
Heart Sounds
Auscultation is the process of listening to these internal body sounds using a stethoscope. The heart produces four types of sounds, but only two—S1 and S2—can usually be heard with a stethoscope.
S1, also known as the "lub" sound, is caused by the closure of atrioventricular (A-V)...
 01:25
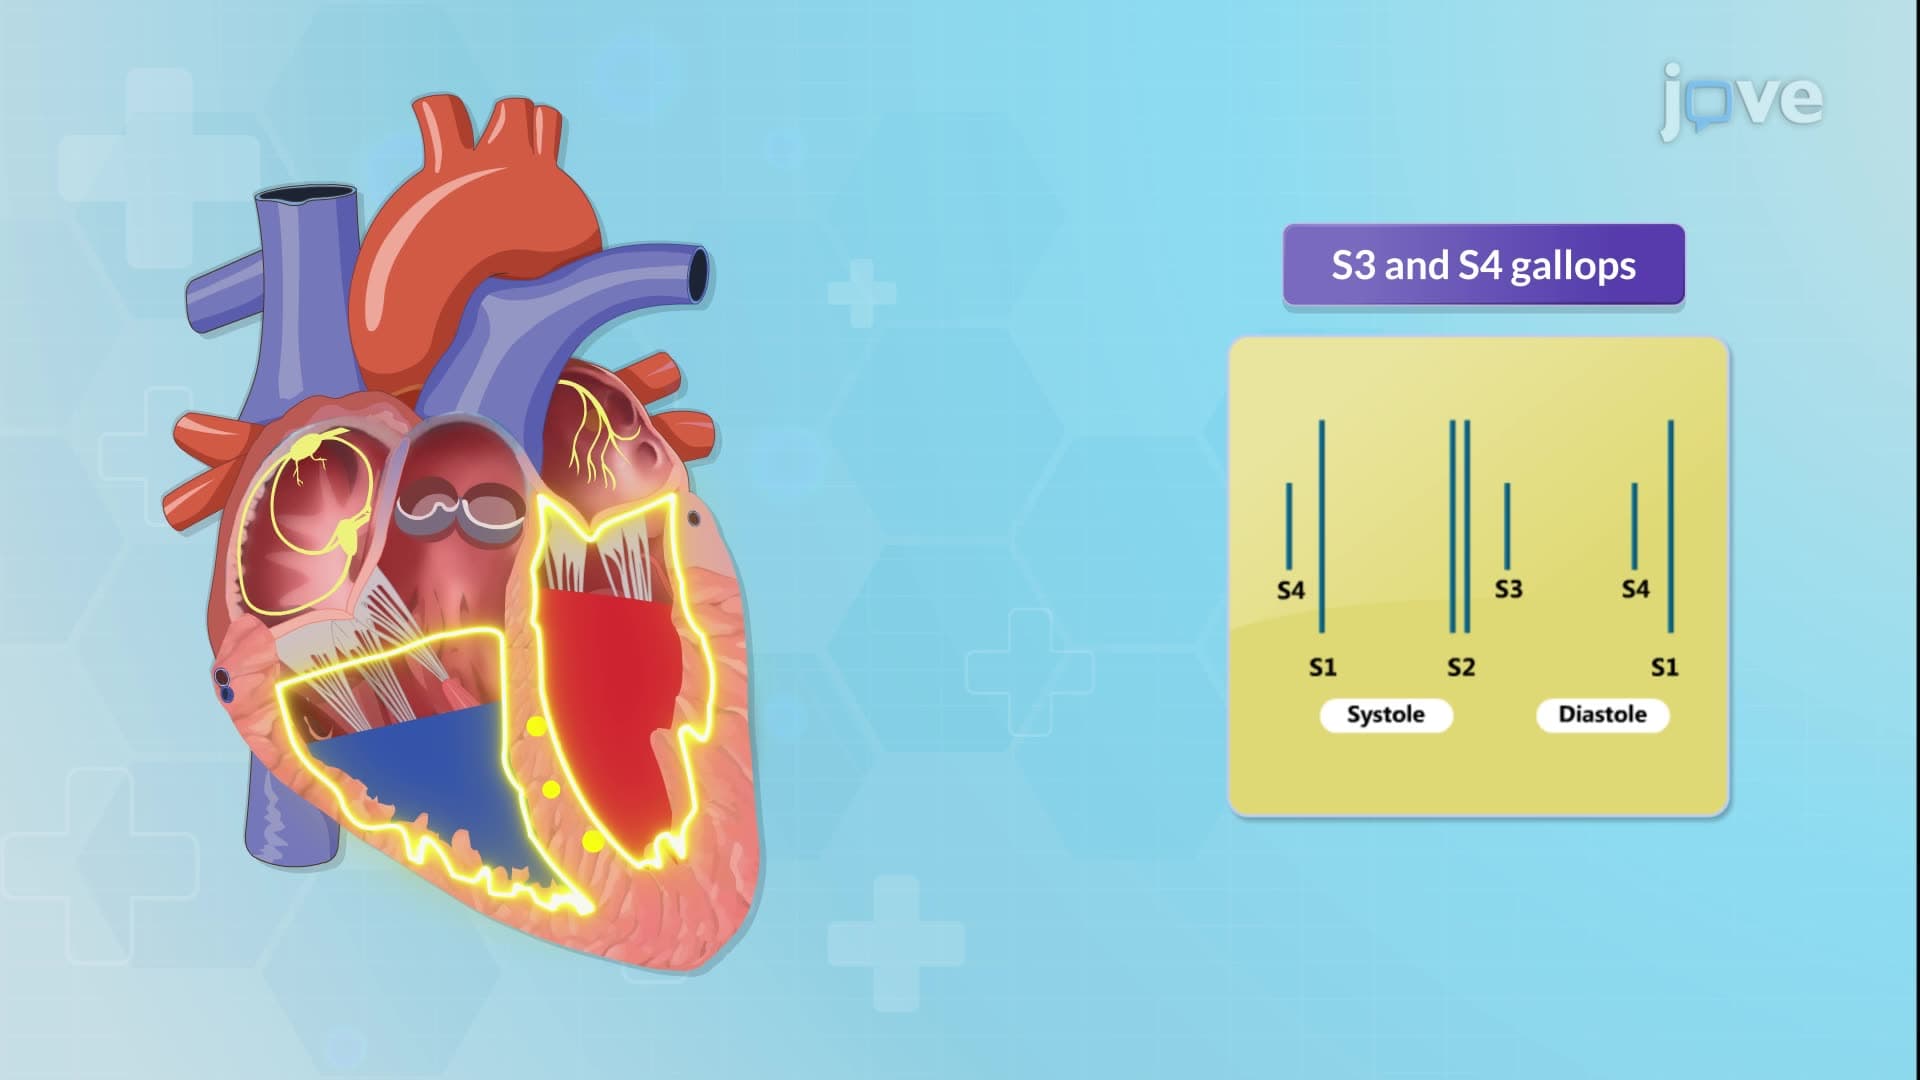
Cardiovascular System Abnormal Findings II: Auscultation
Abnormal Heart Sounds
Gallops:
 01:12
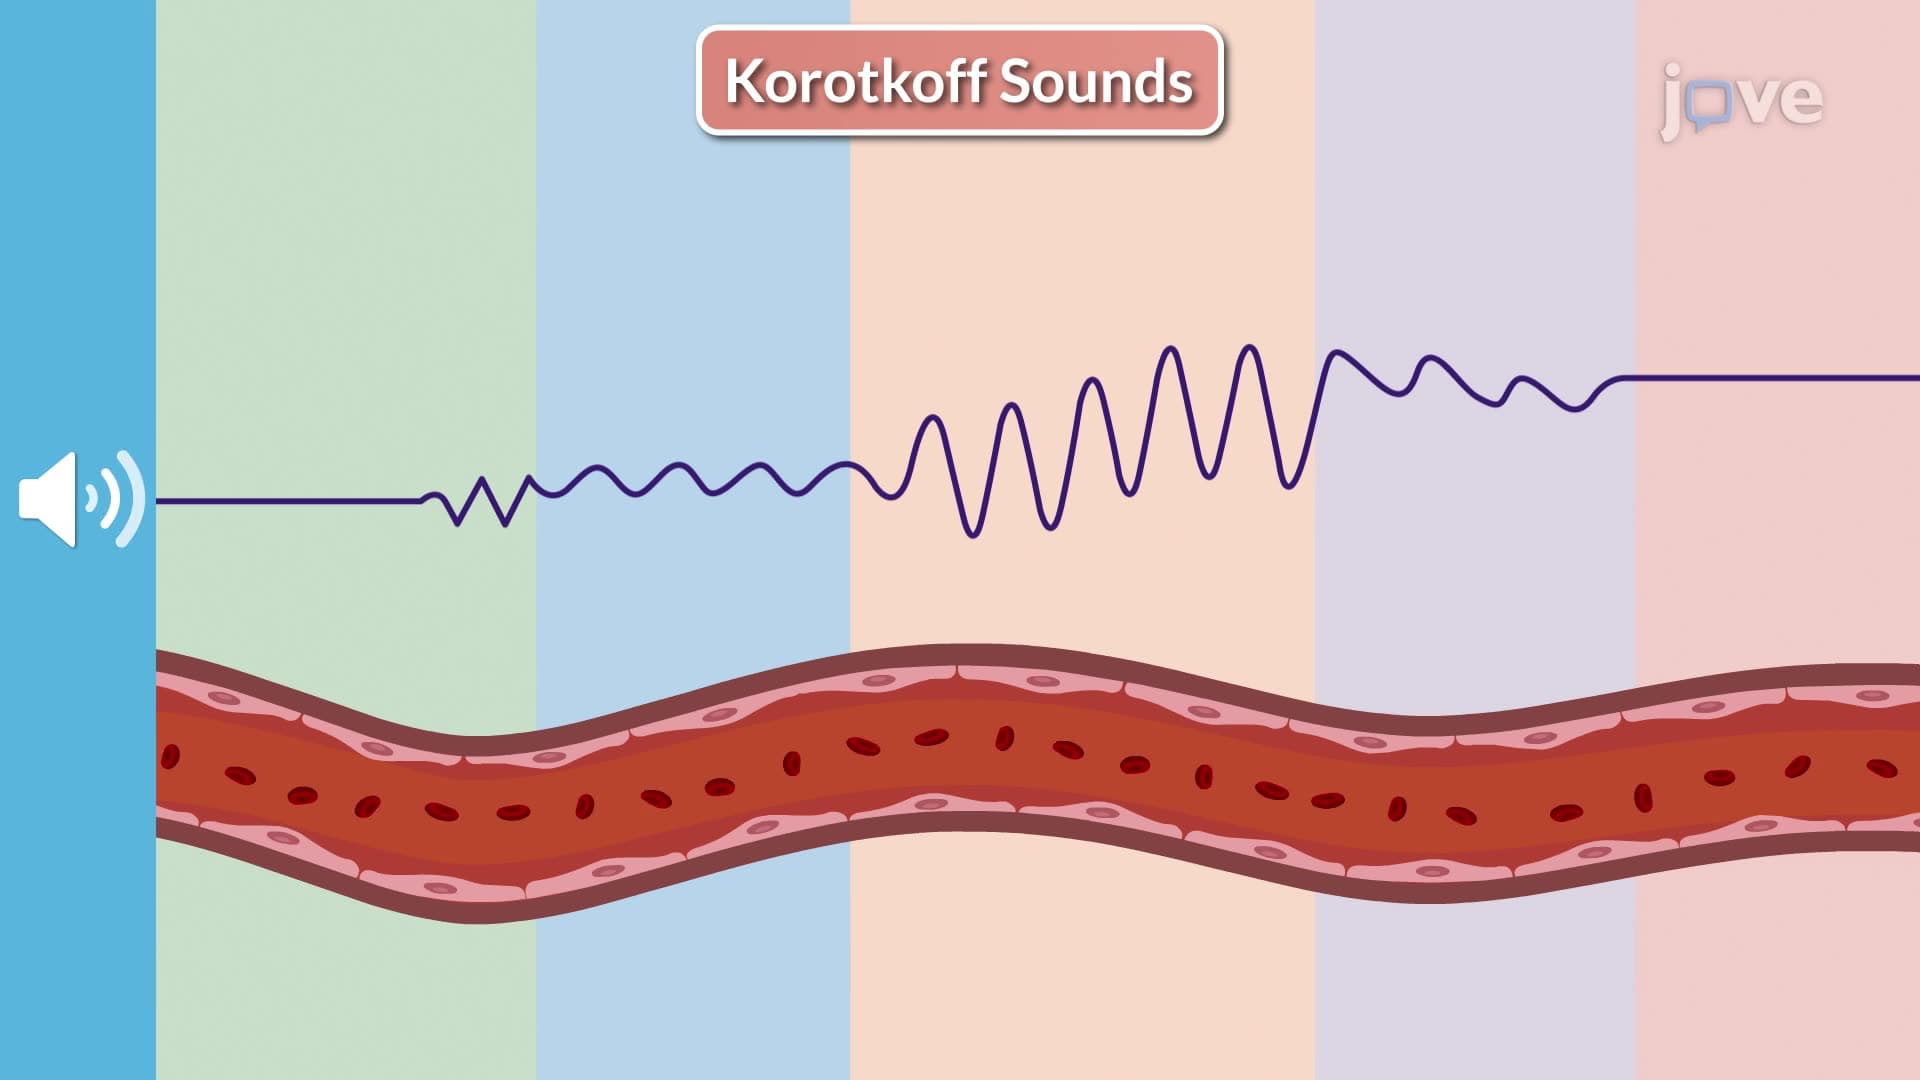
Korotkoff Sounds
During blood pressure assessment, inflating the cuff 30 millimeters of mercury above the patient's systolic blood pressure...
 01:31
Respiratory System Abnormal Finding II: Palpation and Auscultation
Palpation Findings
During a respiratory assessment, palpation can reveal several vital abnormalities:
 01:28
Physical Assessment of the Respiratory Tract IV: Auscultation
Breath Sounds
Breath sounds are categorized into vesicular, bronchovesicular, and bronchial.
 01:09
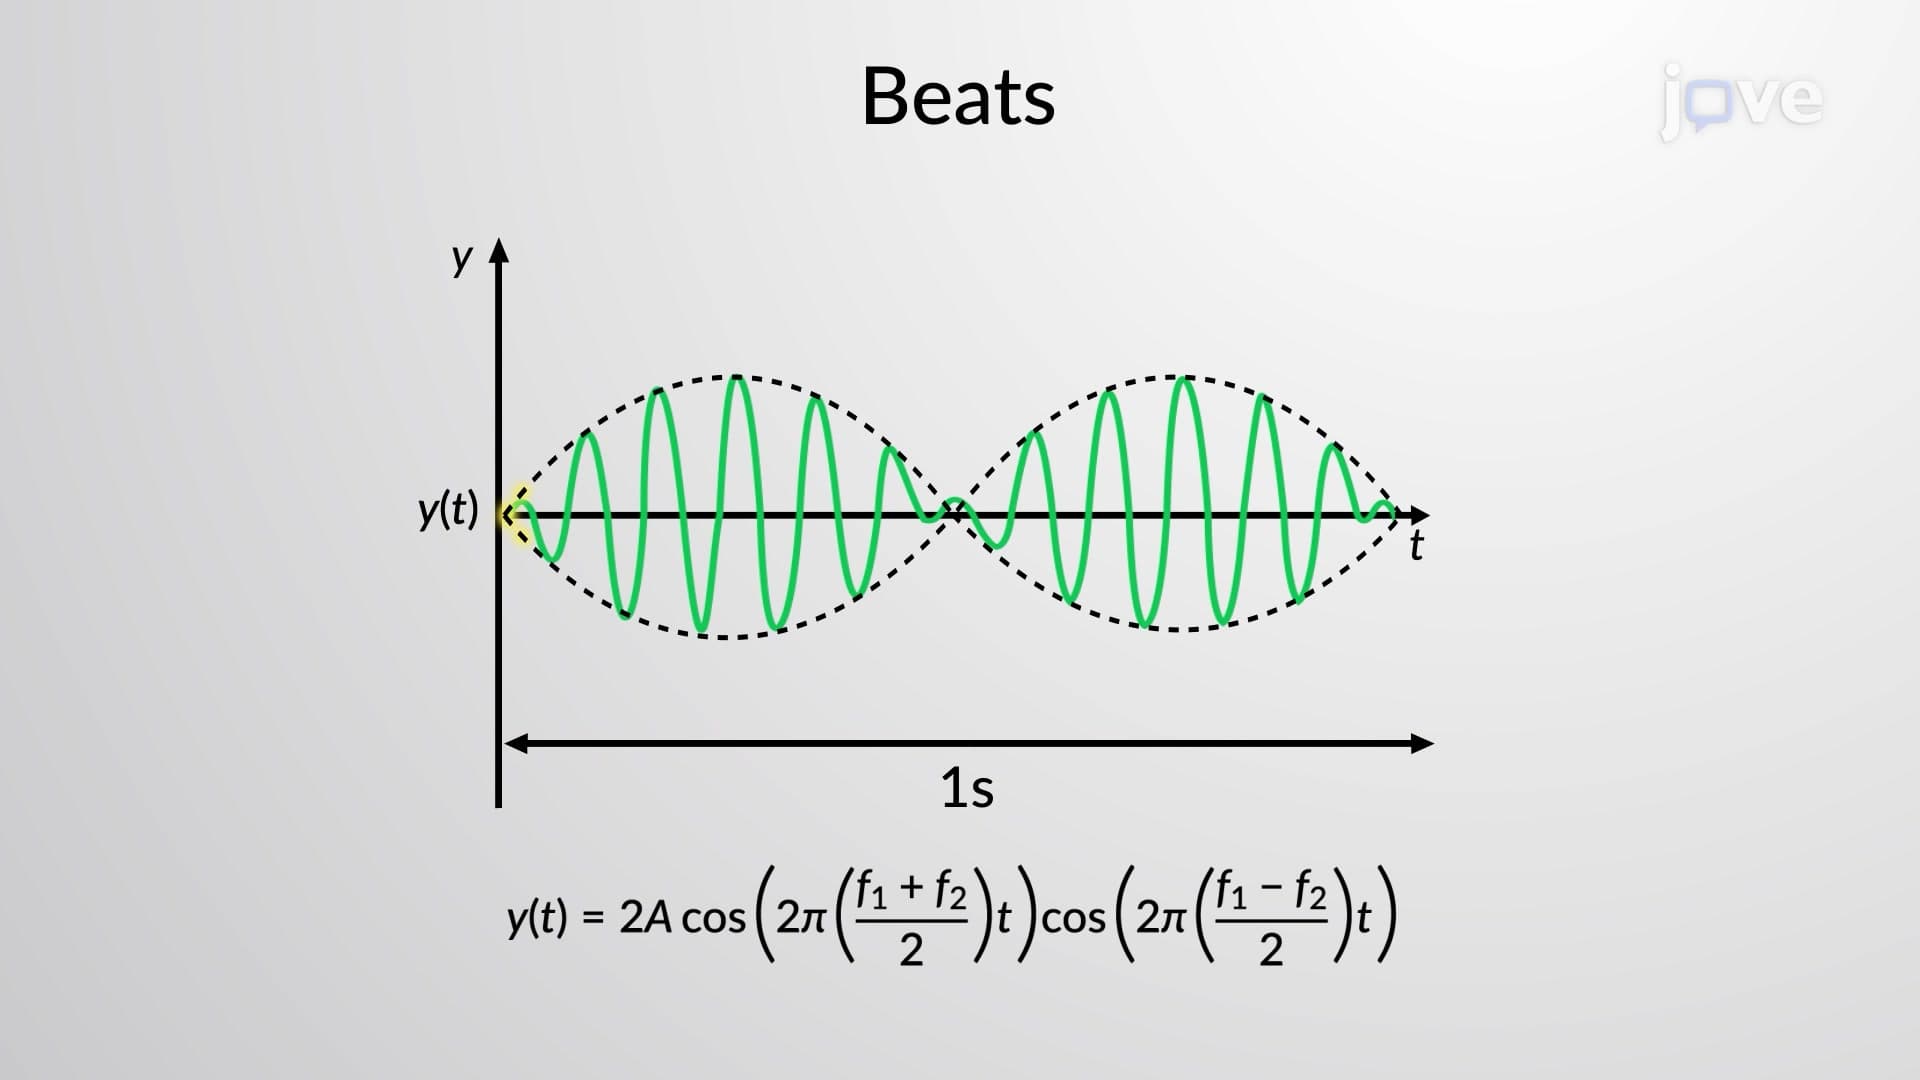
Beats