Related Experiment Video
Updated: Aug 15, 2025
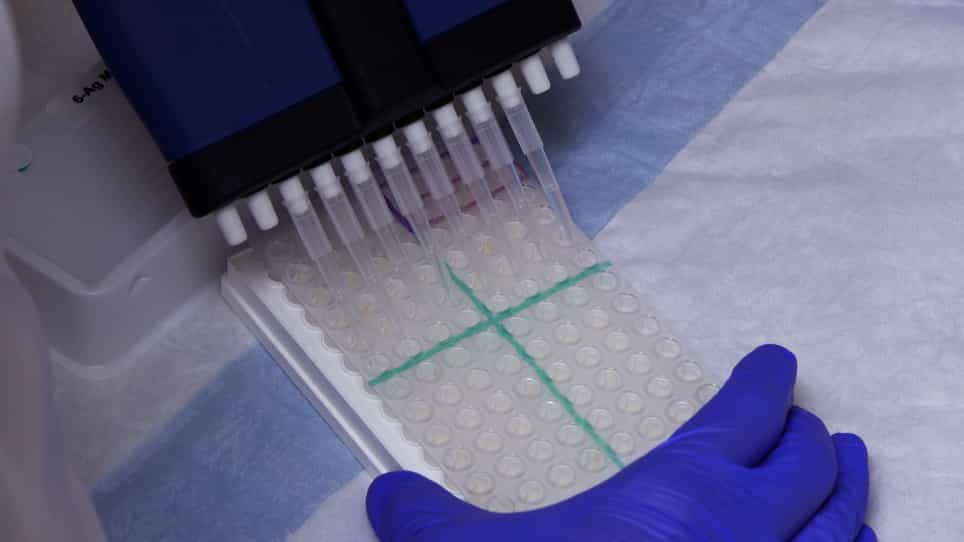

A High-Throughput Multiplexed Screening for Type 1 Diabetes, Celiac Diseases, and COVID-19
Published on: July 5, 2022
Gender gaps in type 1 diabetes care
Jessica C G Bak1,2, Erik H Serné1, Harold W de Valk3
1Department of Vascular Medicine, Amsterdam University Medical Centers, Location AMC, Meibergdreef 9, 1105 AZ, Amsterdam, The Netherlands.

Aims:
Diabetes mellitus is one of the largest global health concerns of recent times. Women with diabetes mellitus have a higher excess risk of all-cause mortality and more vascular events than men. Focusing on type 1 diabetes, this could be caused by gender inequalities in delivered diabetes care. This study aims to assess gender differences in type 1 diabetes outpatient care, particularly diagnostics and outcomes.
Methods:
This cross-sectional cohort study included all adult type 1 diabetes patients in the Dutch Pediatric and Adult Registry of Diabetes (DPARD) visiting diabetes outpatient clinics between 2016-2021. The frequency of process measurements, including physical examination and laboratory testing, was assessed among both sexes after adjustment for age and body mass index. Gender differences in eGFR ≥ 60, BMI-, and control in blood pressure and LDL-cholesterol were evaluated. Hospital variation in achieving HbA1c targets of 53 mmol/mol and median HbA1c were assessed. Cardiovascular risk scores were calculated in men and women using the Systematic Coronary Risk Evaluation (SCORE) European low-risk chart.
Results:
Our study showed a 17% higher odds of reaching weight control and a 23% lower odds of achieving blood pressure targets in men than women. Gender-skewed cardiovascular mortality risk scores were found. Gender disparities in outcomes appear not to be caused by gender-biased attitudes in healthcare professionals since no gender differences were found in the performance of process measurements in type 1 diabetes care. In addition, hospitals appear to vary by extent of gender differences in achieving a target HbA1c of 53 mmol/mol.
Conclusion:
Gender equality exists in the diagnostic process of diabetes care. However, differences in weight control, blood pressure control, and cardiovascular mortality risk scores remain between both sexes, most likely due to multifactorial causes. Indications for interhospital variation in gender disparities in HbA1c control exist. Further focus on performance of process measurements between hospitals may identify areas for improvement of gender-skewed outcomes to further enhance Dutch diabetes care for both sexes.

Related Concept Videos
 01:22
Diabetes Mellitus: Overview and Type I Subtype
Type 1 diabetes is an autoimmune disease in which the immune system mistakenly attacks and destroys the insulin-producing beta cells in the pancreas. As a result, the body is unable to produce sufficient insulin, and individuals with...
 01:22
Diabetes Mellitus: Type 2 and Gestational
 01:15
Diabetes: Management and Pharmacotherapy
Insulin remains the cornerstone of treatment for most patients with type 1 and many...
 01:20
Pathophysiology of Diabetes
Type 1 diabetes is characterized by autoimmune-mediated destruction of pancreatic β cells, with environmental factors potentially triggering this process in genetically susceptible individuals. Despite many not having a family history, certain genes increase susceptibility,...
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
 01:36
Carbohydrate Metabolism
Starch accounts for approximately 60% of the carbohydrates consumed by humans. Since amylase enzymes cannot function in the stomach's acidic environment, starch can only be digested in the mouth and small intestine. Simple sugars are found naturally in milk and fruits in...