Volume-guarantee vs. pressure-limited ventilation in evolving bronchopulmonary dysplasia
Related Experiment Video
Updated: Aug 14, 2025

Combining Volumetric Capnography And Barometric Plethysmography To Measure The Lung Structure-function Relationship
Published on: January 8, 2019
Milenka Cuevas Guaman1, Joseph Hagan1, Dajana Sabic1
1Department of Pediatrics, Division of Neonatology, Texas Children's Hospital, Baylor College of Medicine, Houston, TX, United States.

Insights
Volume-guarantee ventilation (VGV) use in extremely premature infants with evolving bronchopulmonary dysplasia (BPD) was associated with a decreased risk of BPD compared to pressure-limited ventilation (PLV). Further trials are needed to confirm these findings.
Area of Science:
- Neonatology
- Pediatric Pulmonology
- Critical Care Medicine
Background:
- Extremely premature infants (<28 weeks) face high risks of bronchopulmonary dysplasia (BPD).
- Ventilator support is often necessary, with evolving BPD requiring specific management strategies.
- Current practices include pressure-limited ventilation (PLV) and volume-guarantee ventilation (VGV), a form of volume-targeted ventilation (VTV).
Purpose of the Study:
- To test the hypothesis that VGV use in evolving BPD is associated with improved clinical and pulmonary outcomes compared to PLV.
- To evaluate the impact of different ventilation strategies on BPD development and associated outcomes in extremely premature infants.
Main Methods:
- Retrospective cohort review of 471 extremely premature infants (<28 weeks) from January 2015 to December 2020.
- Analysis of ventilator data (PLV vs. VGV) at Day of Life (DOL) 14, 21, and 28.
- Assessment of ventilator 'dose' and its association with BPD, death, and length of stay (LOS).
Main Results:
- PLV at DOL 21 and 28 was linked to a significantly higher risk of BPD and the composite outcome of BPD or death before 36 weeks compared to VGV.
- Increasing doses of both VGV and PLV were associated with higher odds of BPD and the composite outcome.
- Each additional time point of VGV or PLV exposure increased predicted LOS by 15.3 and 28.8 days, respectively (p<0.001).
Conclusions:
- VGV use at DOL 21 and 28 is associated with a decreased risk of BPD compared to PLV in extremely premature infants.
- Both ventilation modalities, when used for longer durations, are associated with increased length of stay.
- Prospective trials are warranted to confirm the optimal ventilatory strategy for infants with evolving BPD.
Introduction:
Extremely premature infants are at high risk for developing bronchopulmonary dysplasia (BPD). While noninvasive support is preferred, they may require ventilator support. Although volume-targeted ventilation (VTV) has been shown to be beneficial in preventing BPD, no data exists to guide ventilator management of infants with evolving BPD. Thus, clinicians employ a host of ventilator strategies, traditionally time-cycled pressure-limited ventilation (PLV) and more recently volume-guarantee ventilation (VGV) (a form of VTV). In this study, we sought to test the hypothesis that use of VGV in evolving BPD is associated with improved clinical and pulmonary outcomes when compared with PLV.
Design:
Single-center, retrospective cohort review of premature infants born less than 28 weeks inborn to a Level 4 NICU from January 2015 to December 2020. Data abstracted included demographics, maternal and birth data, and ventilator data until death or discharge. Exposure to either VGV or PLV was also examined, including ventilator "dose" (number of time points from DOL 14, 21 and 28 the patient was on that particular ventilator) during the period of evolving BPD.
Results:
Of a total of 471 patients with ventilation data available on DOL 14, 268 were not ventilated and 203 were ventilated. PLV at DOL 21 and 28 was associated with significantly higher risk of BPD and the composite outcome of BPD or death before 36 weeks compared to VGV. Both increasing VGV and PLV doses were significantly associated with higher odds of BPD and the composite outcome. For each additional time point of VGV and PLV exposure, the predicted length of stay (LOS) increased by 15.3 days (p < 0.001) and 28.8 days (p < 0.001), respectively.
Discussion:
Our study demonstrates the association of use of VGV at DOL 21 and 28 with decreased risk of BPD compared to use of PLV. Prospective trials are needed to further delineate the most effective ventilatory modality for this population with "evolving" BPD.

Related Concept Videos
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation...
 01:14
Ventilatory Modes
There are three ventilatory modes: full support, partial support, and spontaneous. These are described below.
Full Support Modes
Full support modes include controlled mechanical ventilation, continuous mandatory...
 01:29
Mechanical Ventilation I: Indication and Settings
 01:15
Respiratory Volumes
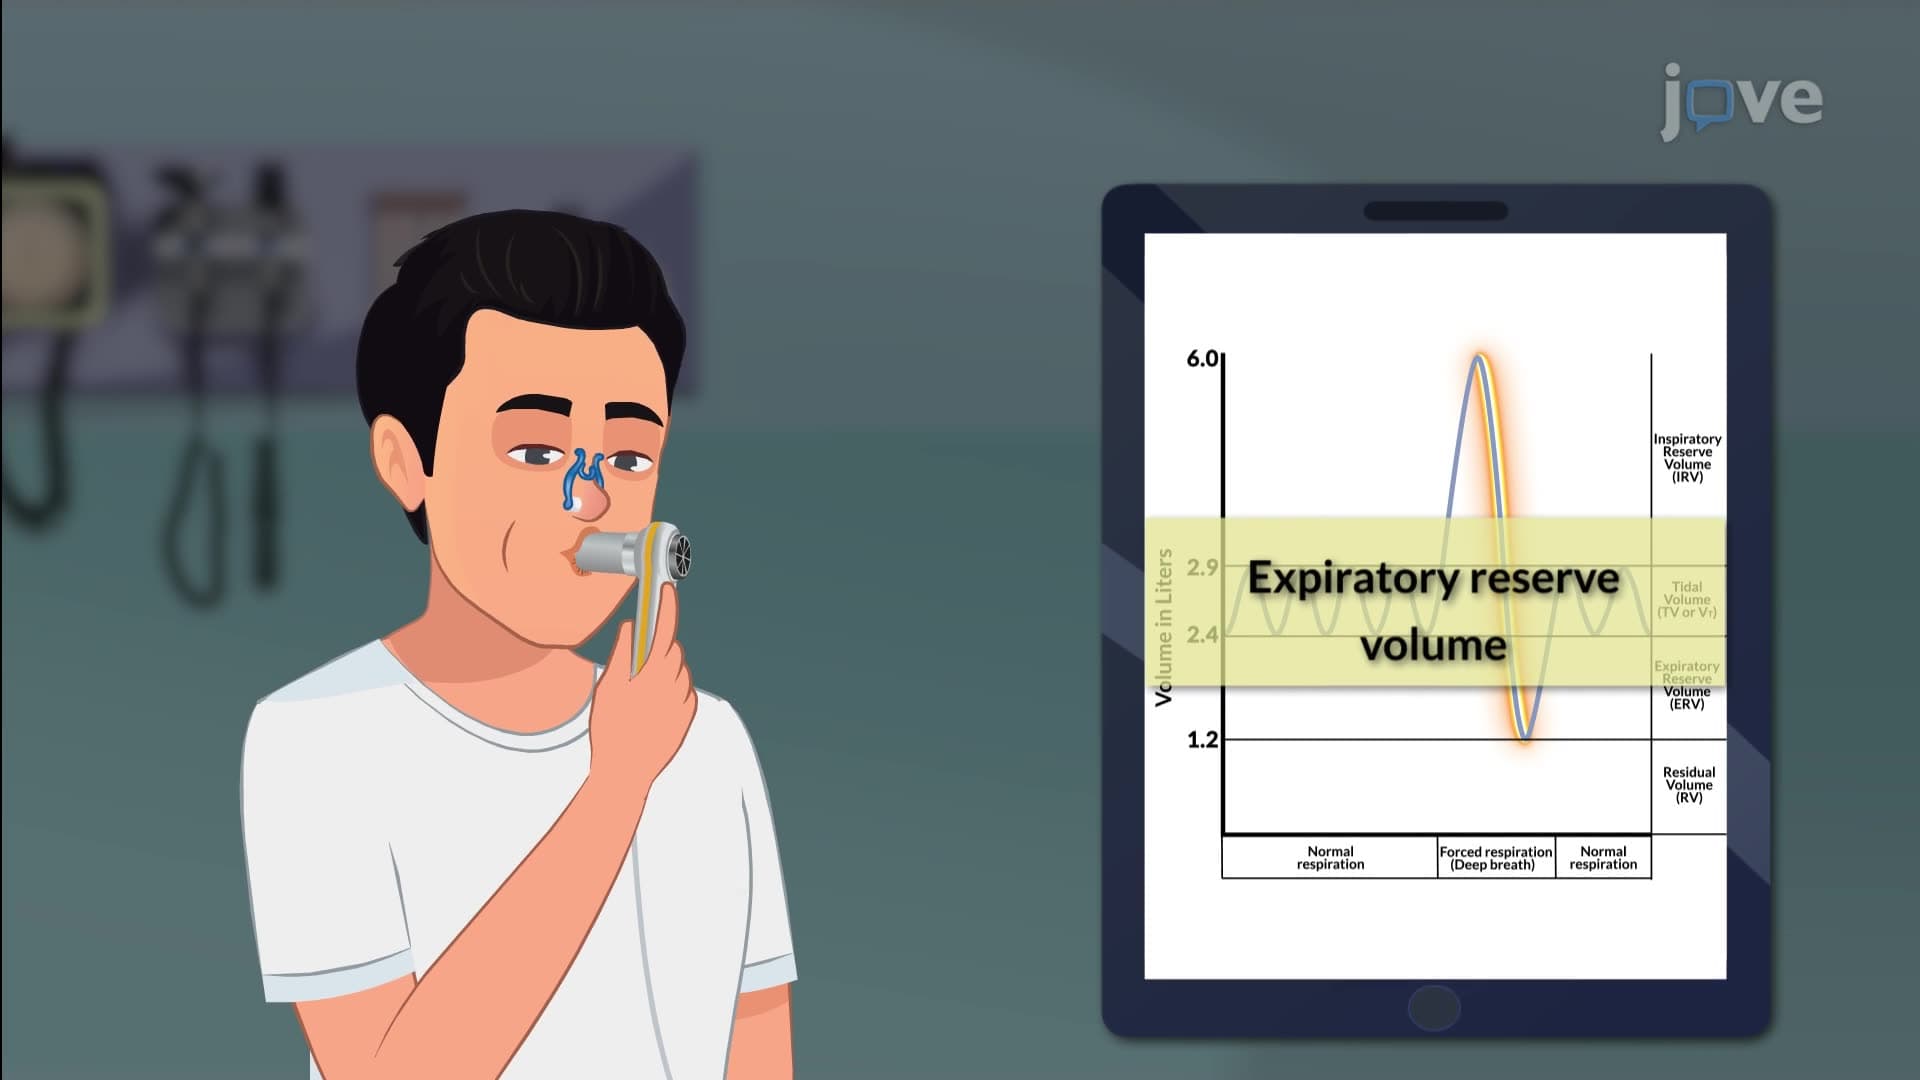
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:24
Pulmonary Ventilation: Inhalation
Boyle's law becomes particularly pertinent when examining respiratory...