Related Experiment Video
Updated: Aug 14, 2025
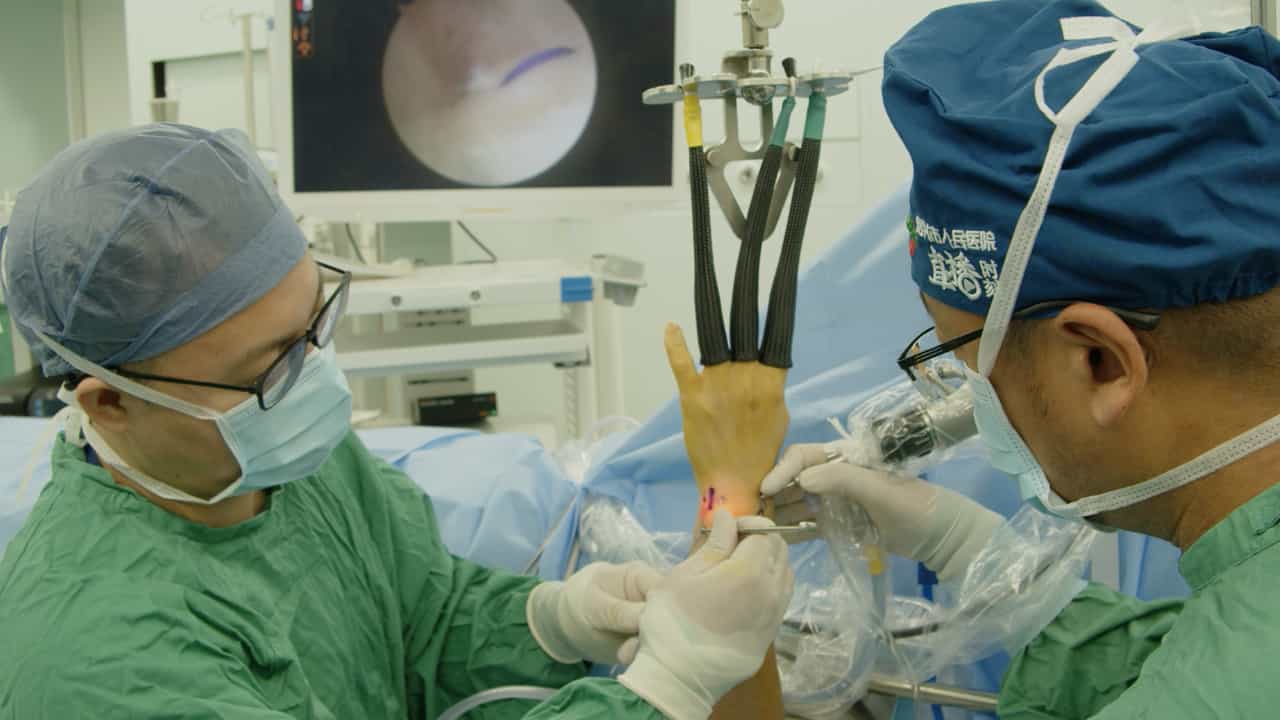

Novel Triple-Loop Technique for Suturing TFCC Injuries without Transosseous Tunnel
Published on: May 23, 2025
Surgical Treatment of Adams Type IV Anterolateral Fracture of the Ulna Coronoid Process
Bo Zhang1, Lintao Liu1, Junyang Liu1
1Department of No. 2 Upper Extremity Traumatology, Tianjin Hospital, Tianjin, China.

Objective:
Anterolateral coronal fractures are so rare that the mechanism of injury, the type of combined fracture and ligament injury, and the optimal treatment are unknown. To study the outcome of surgical treatments for anterolateral (AL) fracture of the ulna coronoid process (Adams Type IV) and summarize the characteristics of this type of fracture and to guide clinical applications.
Methods:
From February 2015 to April 2021, 32 patients were included in the study. All patients had standard radiography with anteroposterior and lateral views, computed tomography, and intraoperative fluoroscopy. All patients were treated surgically. Surgery-related information, including surgical approach, operation duration, blood loss, and repairing the lateral collateral ligament and the medial collateral ligament integrity, were recorded. The patient's clinical details, such as the final range of motion (ROM), the Broberg-Morrey scores and the visual analogue scale (VAS) at the last follow-up, were described. The chi-square test or Fisher's exact test was used for statistical analysis.
Results:
We divided patients into two groups according to the anterolateral coronoid fracture morphology. In the intact group, 20 patients with an intact anterolateral coronoid fracture fragment. In the comminuted group, 12 patients with comminuted anterolateral coronoid fracture fragments extended the less sigmoid notch of the ulna. There was no difference in age, sex, total incision length, follow-up duration, and recovery with rehabilitation among the two groups (all Ps >0.05). The other follow-up outcomes, such as elbow ROM (Flexion, Extension, Posterior rotation, Anterior rotation), VAS score, or Broberg-Morrey scores, were not different between the two groups (all Ps >0.05). Both groups achieved relatively satisfactory clinical outcomes, and the Broberg-Morrey score and index excellence rate reached 84.38%. There is a statistical difference in the history of elbow dislocation (P = 0.017), radial head fracture type (P = 0.041), operation duration (P = 0.014) and blood loss at operation (P = 0.029) between the two groups. Cannulated screws, anchors, and sutures were used as point fixation in the coronoid process of the ulna. There was a statistical difference between the two groups in the choice of internal fixation (P = 0.020).
Conclusions:
For anterolateral ulnar coronoid fractures with different degrees of comminution, effective and reliable surgical treatment can achieve better results and fewer complications.
More Related Videos
 04:41
Treatment with Locking Intramedullary Nailing for Intertrochanteric Fracture of the Femur Utilizing a New Awl with a Distal Positioner
Published on: June 6, 2025
 05:18
Author Spotlight: Ultrasound-Guided Needle Release Combined with Corticosteroid Injection for the Treatment of Supinator Syndrome
Published on: May 26, 2023
Related Concept Videos
 01:15
Bones of the Upper Limb: Ulna
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...