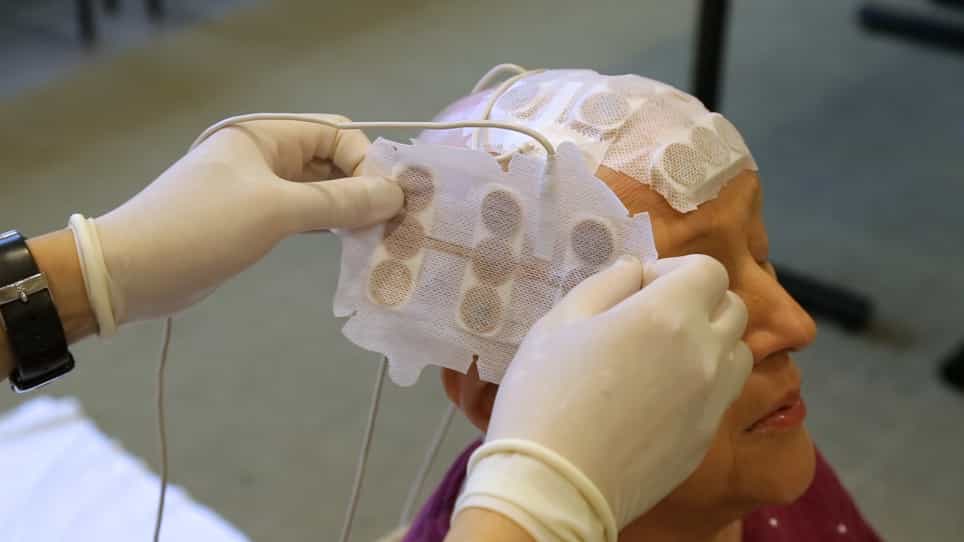
Related Experiment Video
Updated: Aug 14, 2025

Tumor Treating Field Therapy in Combination with Bevacizumab for the Treatment of Recurrent Glioblastoma
Published on: October 27, 2014
Targeted therapies in patients with newly diagnosed glioblastoma-A systematic meta-analysis of randomized clinical
Angelika Scherm1, Franziska Maria Ippen2, Peter Hau1
1Wilhelm Sander-NeuroOncology Unit and Department of Neurology, Regensburg University Hospital, Regensburg, Germany.

Abstract:
Glioblastoma (GB) is the most common malignant primary brain tumor in adults. The standard of care for newly diagnosed GB involves surgical resection followed by radiochemotherapy with temozolomide, with or without tumor-treating fields. In recent years, various efforts have been made to identify suitable molecularly targeted treatment options for malignant brain tumors. This meta-analysis provides an overview of recently published randomized controlled trials (RCTs) with and without molecular stratification, analyzing targeted agents in patients with newly diagnosed GB. The Cochrane Library, MEDLINE (Ovid), ClinicalTrials.gov, WHO's International Clinical Trials Registry Platform, and Google Scholar were searched for RCTs on targeted therapies in patients with newly diagnosed glioblastoma. Hazard ratios (HRs) for overall survival (OS) and progression-free survival (PFS) were extracted and pooled in a random-effects meta-analysis. Twelve RCTs (n = 3941 patients) involving protein kinase inhibitors, proteasome and histone deacetylase inhibitors, anti-angiogenic approaches and poly (ADP-ribose) polymerase (PARP) inhibitors were included in the meta-analysis. None of the targeted agents achieved a significant benefit with regard to OS (HR = 0.98 [95% confidence interval (CI) 0.86-1.11, P = .7731]). By comparison, targeted therapy showed a benefit for PFS (HR = 0.83 [95% CI 0.74-0.94, P = .0037]), especially for patients with an unmethylated O6-methylguanine-DNA-methyltransferase (MGMT) promoter (0.75 [95% CI 0.56-0.99, P = .0440]). Prolongation of PFS was largely driven by VEGF inhibition with bevacizumab (HR = 0.70 [95% CI 0.61-0.80, P = .0000]). VEGF inhibition with bevacizumab prolonged PFS in patients with newly diagnosed glioblastoma compared to standard care. However, no improvement in OS was observed with any of the targeted agents.
Insights
Targeted therapies improved progression-free survival (PFS) in glioblastoma patients, particularly those with unmethylated MGMT promoters, but did not significantly extend overall survival (OS). Bevacizumab showed notable PFS benefits.
Area of Science:
- Neuro-oncology
- Clinical Trials Research
- Molecular Targeted Therapy
Background:
- Glioblastoma (GB) is the most aggressive primary brain tumor in adults.
- Standard treatment involves surgery, radiotherapy, and temozolomide chemotherapy.
- Identifying effective molecularly targeted treatments remains a critical research area.
Approach:
- A meta-analysis of 12 randomized controlled trials (RCTs) involving 3941 patients with newly diagnosed glioblastoma.
- Searched multiple databases including Cochrane Library, MEDLINE, ClinicalTrials.gov, and Google Scholar for relevant RCTs.
- Extracted and pooled hazard ratios (HRs) for overall survival (OS) and progression-free survival (PFS) using a random-effects model.
Key Points:
- No targeted agents demonstrated a significant improvement in overall survival (OS) (HR = 0.98).
- Targeted therapies showed a significant benefit for progression-free survival (PFS) (HR = 0.83).
- Patients with an unmethylated O6-methylguanine-DNA-methyltransferase (MGMT) promoter particularly benefited in PFS (HR = 0.75).
- VEGF inhibition with bevacizumab was the primary driver of PFS prolongation (HR = 0.70).
Conclusions:
- While targeted therapies, especially VEGF inhibition with bevacizumab, can prolong PFS in newly diagnosed glioblastoma, they do not improve OS.
- Further research is needed to identify targeted agents that can enhance overall survival in glioblastoma patients.