Related Experiment Video
Updated: Aug 13, 2025
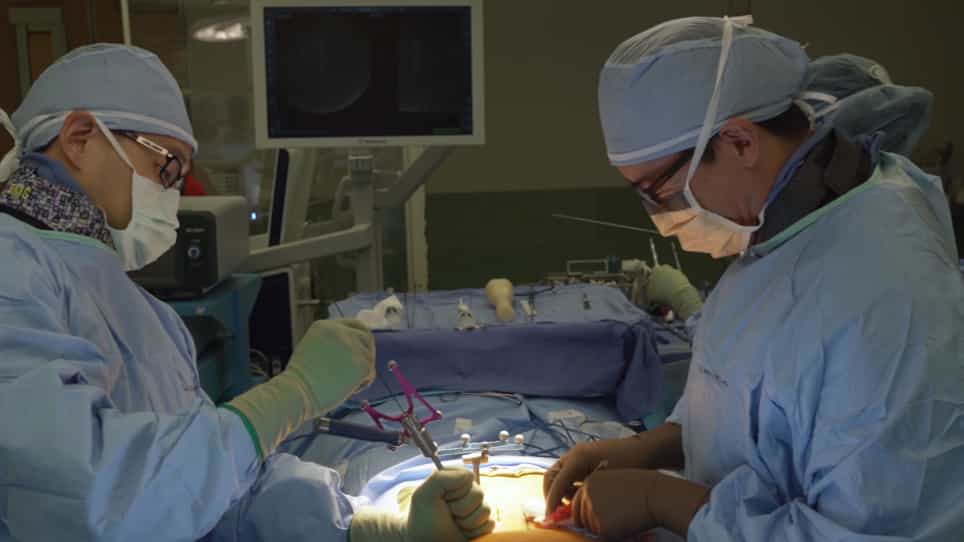

Cone Beam Intraoperative Computed Tomography-based Image Guidance for Minimally Invasive Transforaminal Interbody Fusion
Published on: August 6, 2019
Safety of blind versus guided feeding tube placement: Misplacement and pneumothorax risk
Stephen J Taylor1, Terpsi Karpasiti2, Danielle Milne1
1Department of Nutrition & Dietetics, Southmead Hospital, North Bristol NHS Trust, BS10 5NB, United Kingdom.

Abstract:
Most intensive care unit patients require a feeding tube, but misplacement risk is high due to the presence of artificial airways and because unconsciousness reduces clinical warnings. Predominantly, tubes are placed 'blindly', where position is not known throughout placement. The result is that 1.6% enter the lung, 0.5% cause pneumothorax and potentially 5% are left in the oesophagus. Guided placement, by identifying tube position in real time, may prevent these problems, but undetected misplacements still occur. We review the safety of guided methods of confirming tube position, including rates of pneumothorax, in the context of current unguided methods. During blind tube placement, tube position can only be tracked intermittently. Excepting X-ray and ultra-sound, most methods of checking position are simple. Conversely, guided tube placement can track tube position from the nose to small intestine (IRIS®), or oesophagus to jejunum (Cortrak™, ENvue®). However, this requires expertise. Overall, guided placement is associated with lower rates of pneumothorax. Unfortunately, for Cortrak, low-use centres have higher rates of undetected misplacement compared with blind placement whereas Cortrak use in high-use centres had lower risk compared with blind placement and low use centres. Because guided placement requires high-level expertise manufacturer training packages have been developed but currently appear insufficient. Specifically, Cortrak's package is less accurate in determining tube position compared to the 'gastrointestinal flexure' system. Validation of an evidence-based guide for IRIS placement is underway. Recommendations are made regarding the training of new operators, including minimum numbers of placements required to achieve expertise.
More Related Videos


Related Concept Videos
 01:26
Enteral Nutrition I: Orogastric and Nasogastric Feeding
Orogastric (OG) and nasogastric (NG) feeding are two standard methods used for enteral nutrition. Enteral nutrition is often preferred over...
 01:28
Tracheostomy: Procedure and Tubes
Tracheostomy tubes can be made of semiflexible plastic (polyurethane or silicone), rigid plastic, or metal, and they come in...
 01:15
Enteral Nutrition II: Nasointestinal and Gastrostomy Feeding
Nasointestinal Feeding
Nasointestinal feeding involves placing a tube...
 01:23
Oxygen Delivering System III: Tracheostomy and T-piece
Tracheostomy
A tracheostomy is a surgically created opening (stoma) in the anterior part of the trachea. It is used to establish a patient airway, bypass an upper airway obstruction, simplify the removal of secretions, permit long-term...
 01:15
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...