Related Experiment Video
Updated: Aug 13, 2025


Author Spotlight: Exploring the Impact of Reduced Resistance Exercise Volume on Metabolic Health
Published on: December 1, 2023
Optimization of Albuminuria-Lowering Treatment in Diabetes by Crossover Rotation to Four Different Drug Classes: A
Viktor Rotbain Curovic1, Niels Jongs2, Marjolein Y A M Kroonen2
11Steno Diabetes Center Copenhagen, Herlev, Denmark.

Objective:
Renin-angiotensin system (RAS) inhibitors decrease the urinary albumin to creatinine ratio (UACR) but are ineffective in up to 40% of patients. We hypothesized that rotation through different drug classes overcomes RAS inhibitor resistance and tested this in a randomized crossover trial.
Research Design And Methods:
We assigned 26 adults with type 1 diabetes and 37 with type 2 diabetes and UACR between 30 and 500 mg/g and estimated glomerular filtration rate >45 mL/min/1.73 m2 to 4-week treatment periods with telmisartan 80 mg, empagliflozin 10 mg, linagliptin 5 mg, and baricitinib 2 mg in random order, separated by 4-week washout periods. Each participant was then re-exposed for 4 weeks to the drug that induced that individual's largest UACR reduction. Primary outcome was the difference in UACR response to the best-performing drug during the confirmation period versus UACR response to the other three drugs.
Results:
There was substantial variation in the best-performing drug. Telmisartan was best performing for 33 participants (52%), empagliflozin and linagliptin in 11 (17%), and baricitinib in 8 participants (13%). The individuals' best-performing drug changed UACR from baseline during the first and confirmatory exposures by a mean of -39.6% (95% CI -44.8, -33.8; P < 0.001) and -22.4% (95% CI -29.7, -12.5; P < 0.001), respectively. The Pearson correlation for first versus confirmatory exposure was 0.39 (P = 0.017). The mean change in UACR with the other three drugs was +1.6% (95% CI -4.3%, 8.0%; P = 0.593 versus baseline; difference versus individuals' best-performing drug at confirmation, 30.9% [95% CI 18.0, 45.3]; P < 0.001).
Conclusions:
We demonstrated a large and reproducible variation in participants' responses to different UACR-lowering drug classes. These data support systematic rotation through different drug classes to overcome therapy resistance to RAS inhibition.


Related Concept Videos
 01:08
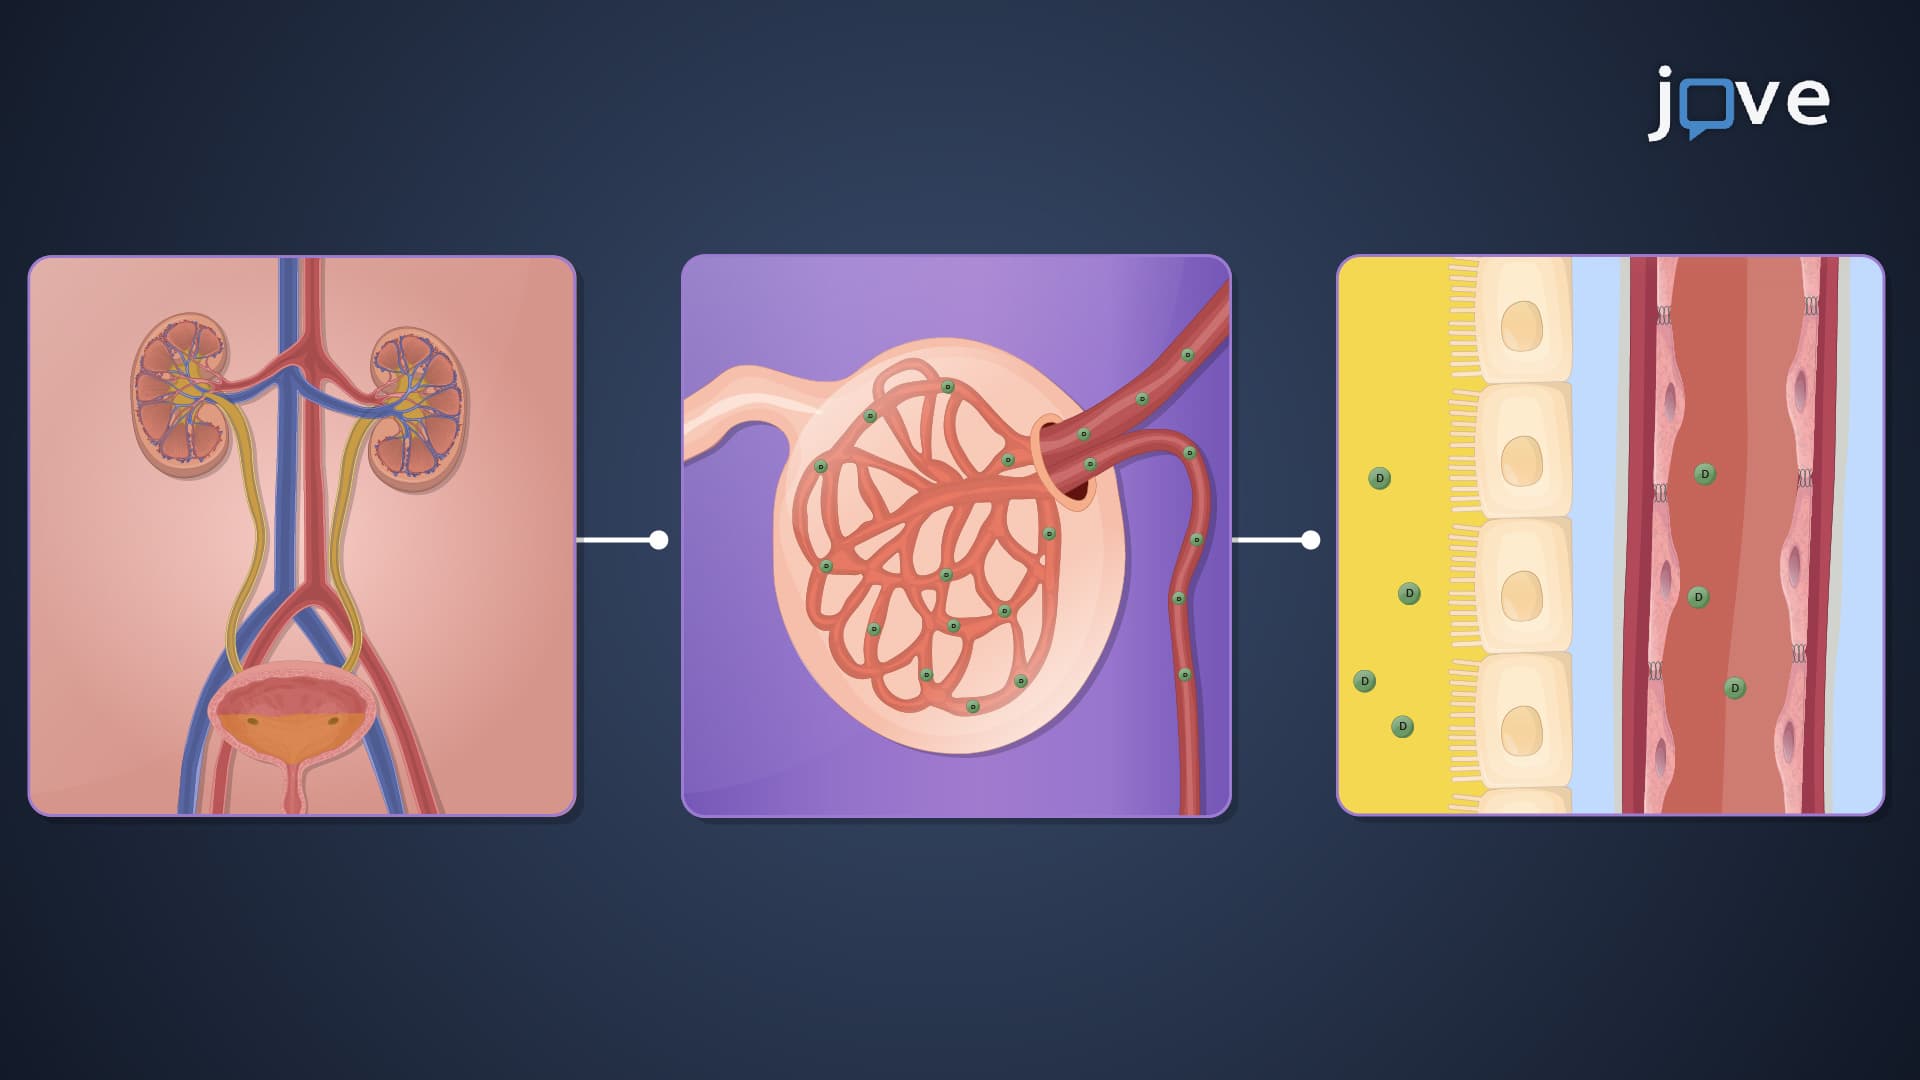
Renal Drug Clearance: Comparison Between Renal Excretion Methods
Renal clearance is often associated with the renal glomerular filtration rate (GFR), which represents the rate at which plasma is filtered through the glomeruli in the kidney. When drug reabsorption is minimal and there is no active secretion, renal clearance is closely related to the...
 01:06
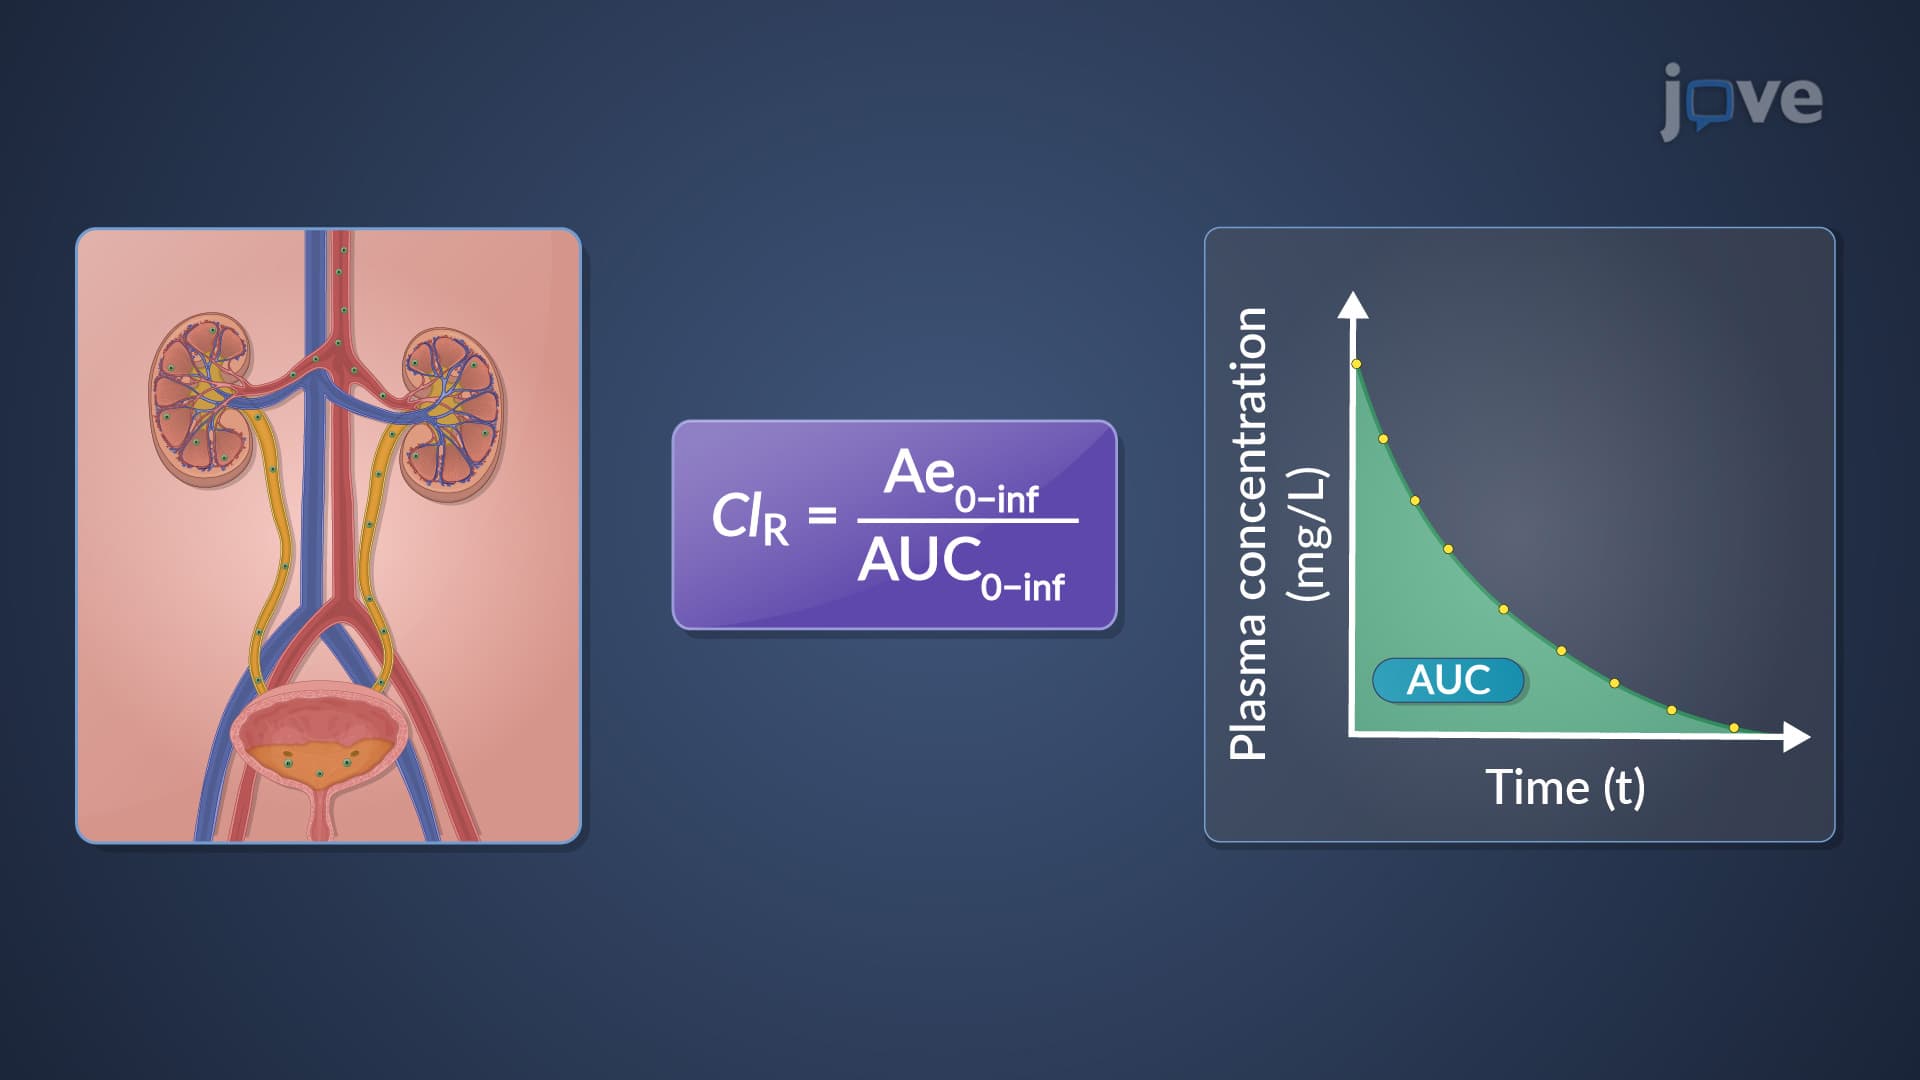
Renal Drug Clearance: Overview
Renal clearance can be calculated using different methods. One approach is to divide the urinary drug excretion rate by the plasma drug concentration. This method directly measures renal clearance, indicating the kidneys' efficiency in...
 01:15
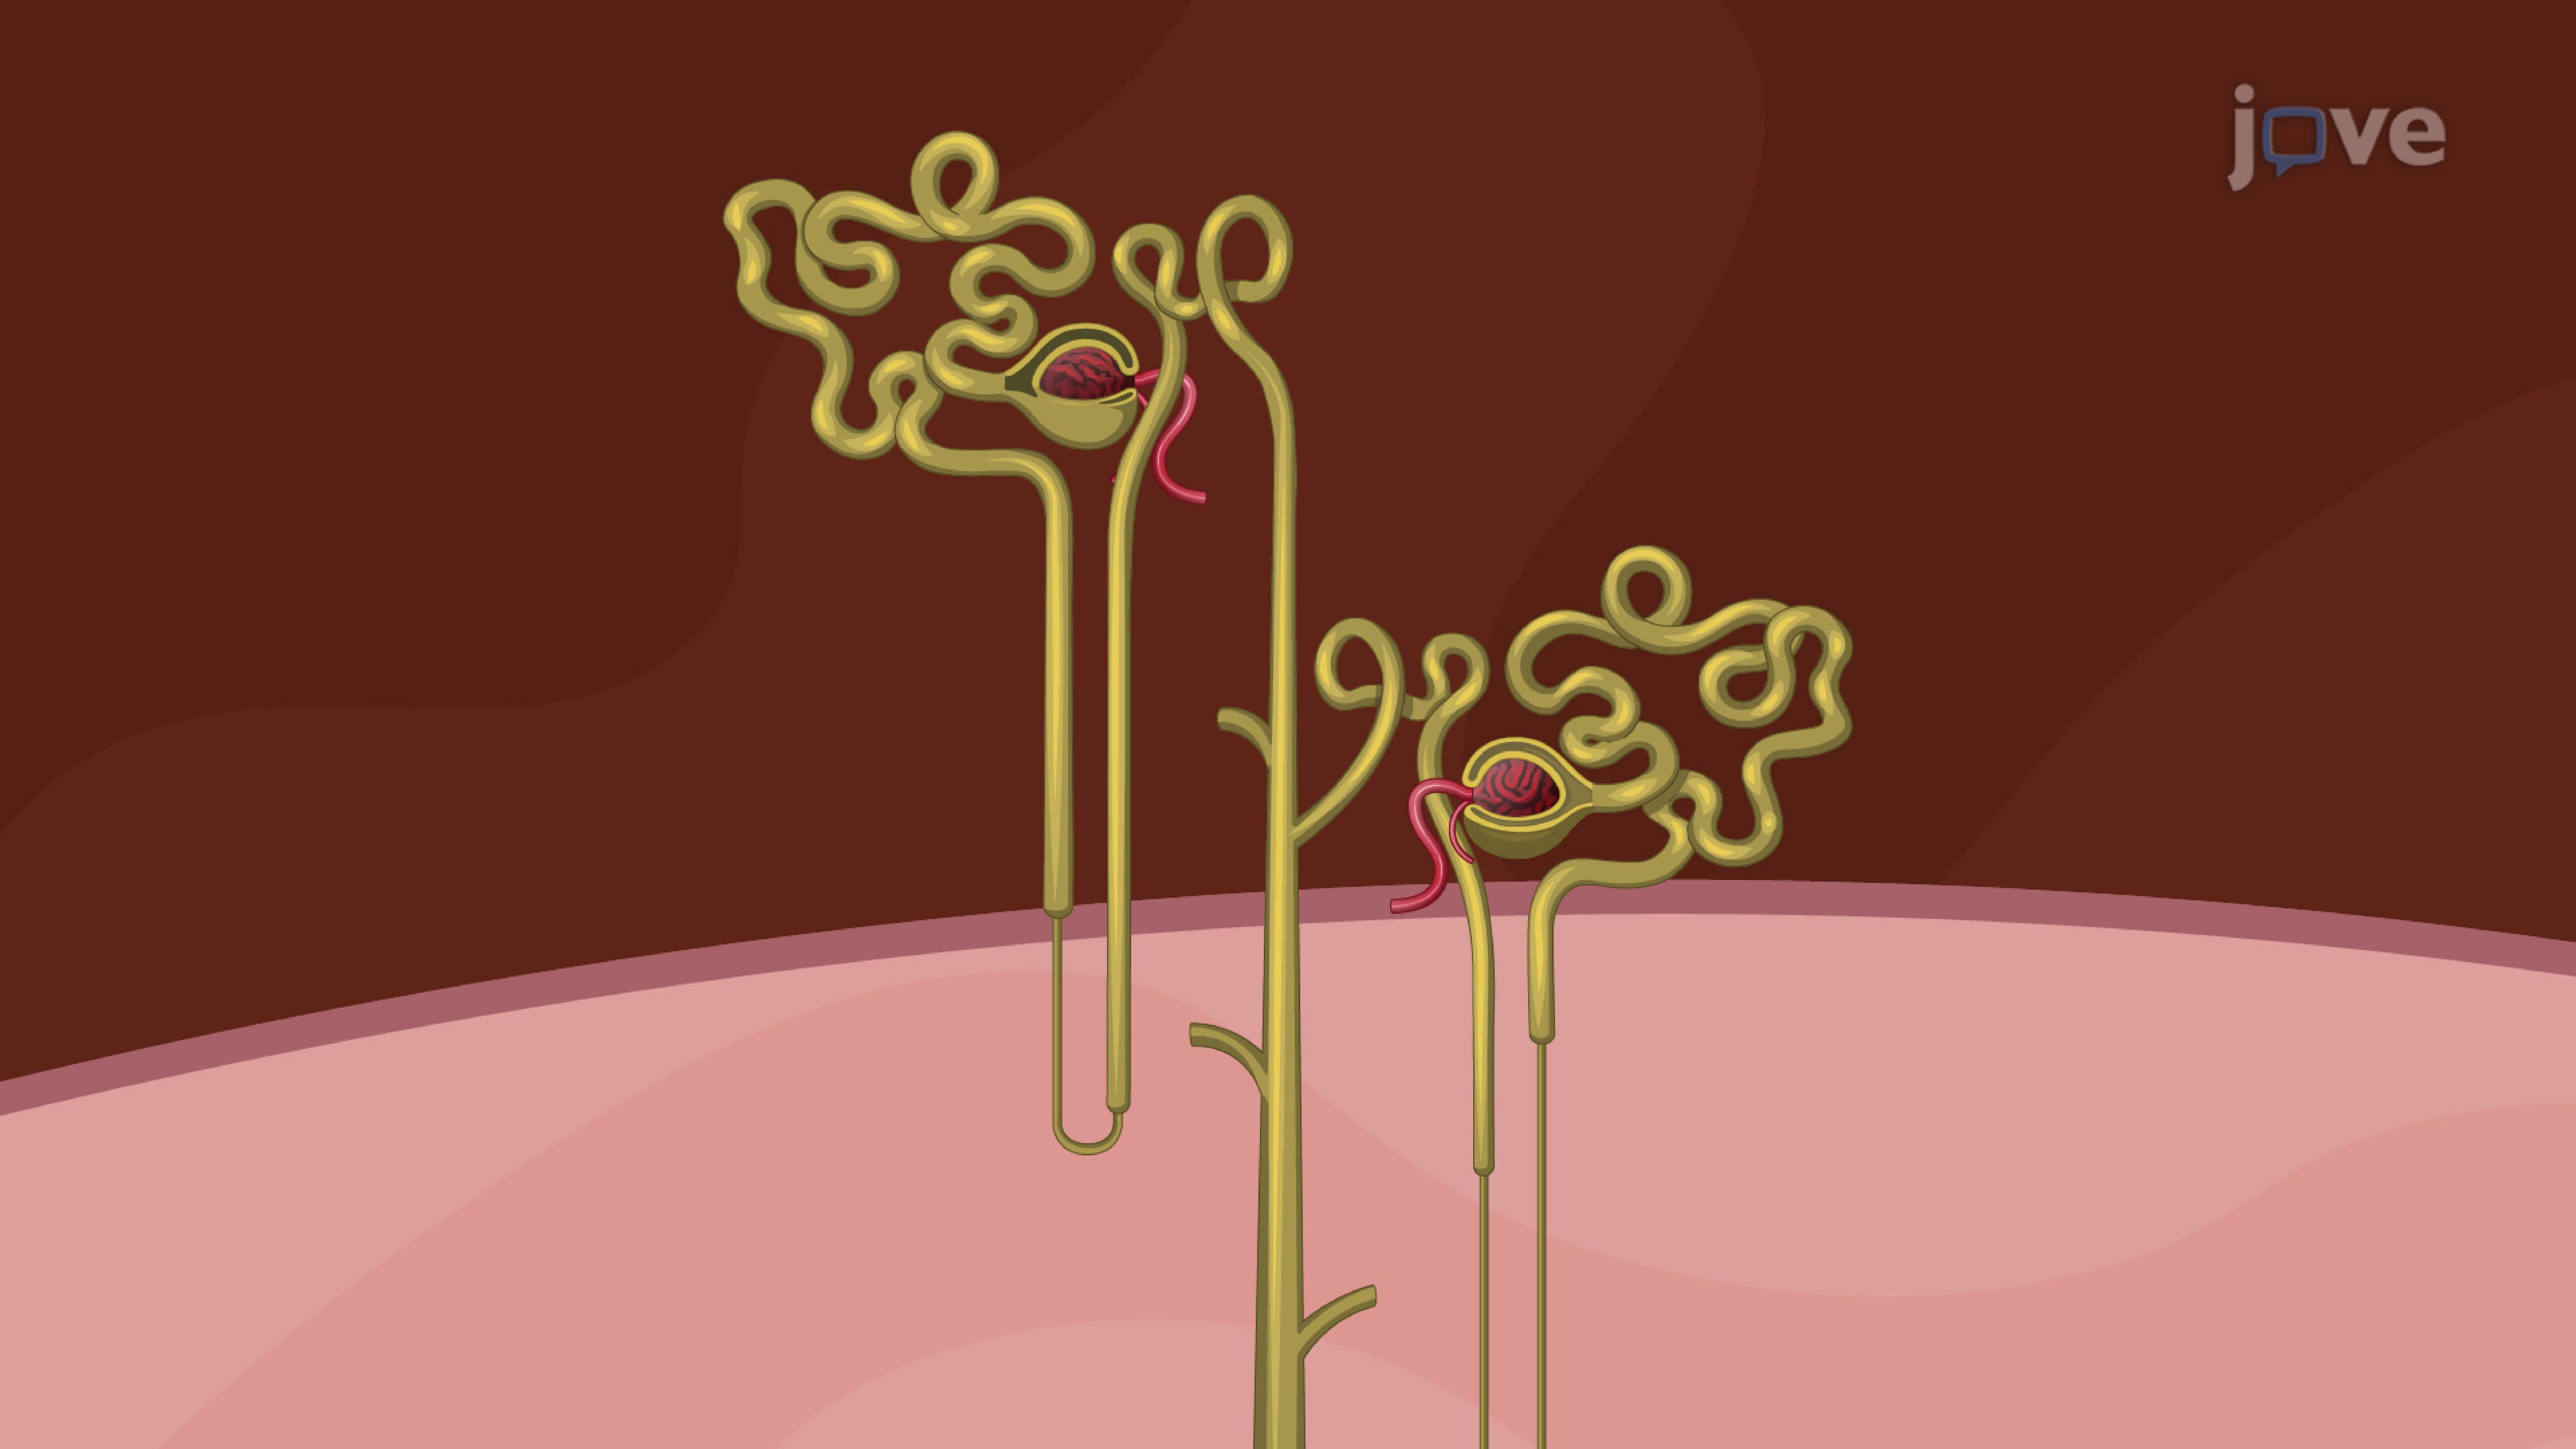
Renal Drug Excretion: Overview
A nephron consists of two primary structures: the renal corpuscle and the renal tubule. The renal corpuscle contains the glomerulus, a network of capillaries where the first step of renal excretion, glomerular filtration, occurs. Blood pressure forces water, ions, and small molecules...
 01:28
Renal Drug Excretion: Tubular Secretion
 01:23
Dipeptidyl Peptidase 4 Inhibitors
 01:09
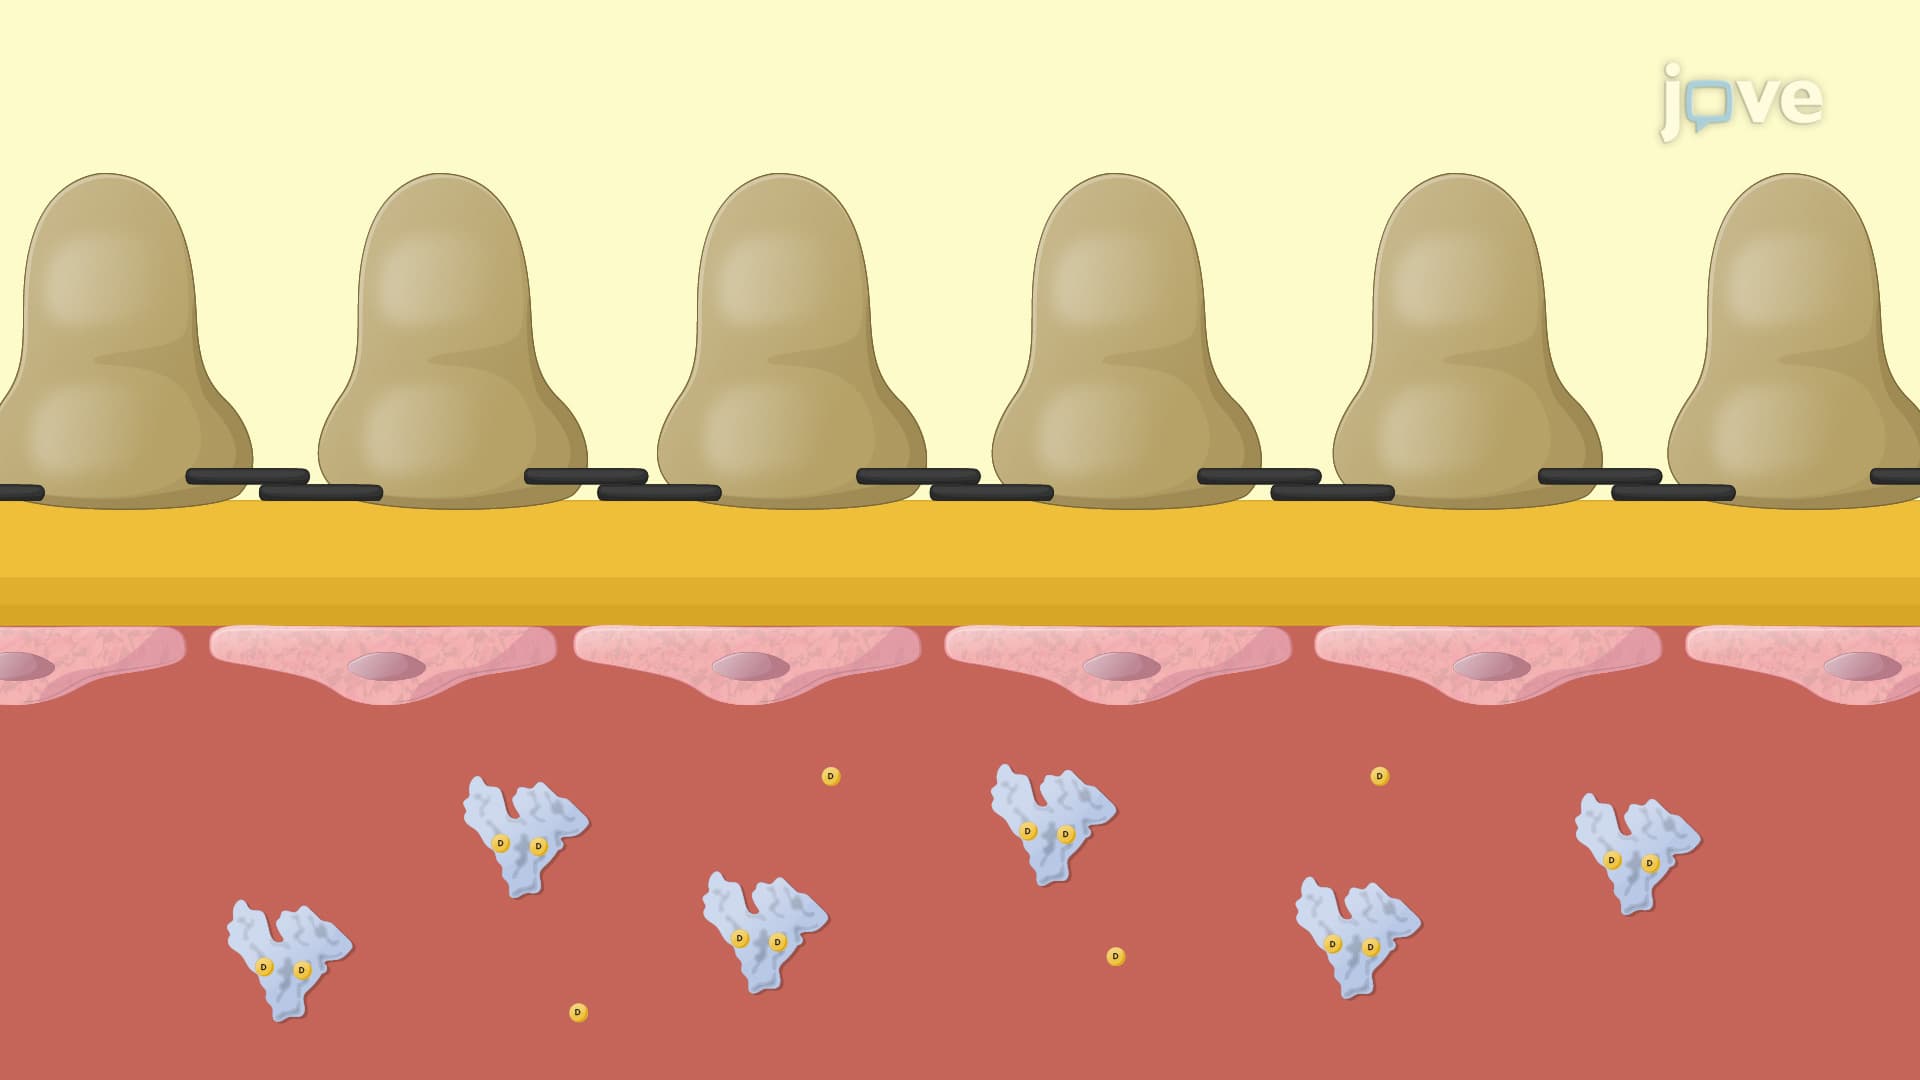
Factors Affecting Renal Clearance: Drug Distribution and Drug Interactions
One important factor is the relationship between renal clearance and the apparent volume of distribution. Renal clearance tends to be inversely proportional to the apparent volume of distribution. Drugs with an extensive distribution volume or those...