Related Experiment Video
Updated: Aug 13, 2025
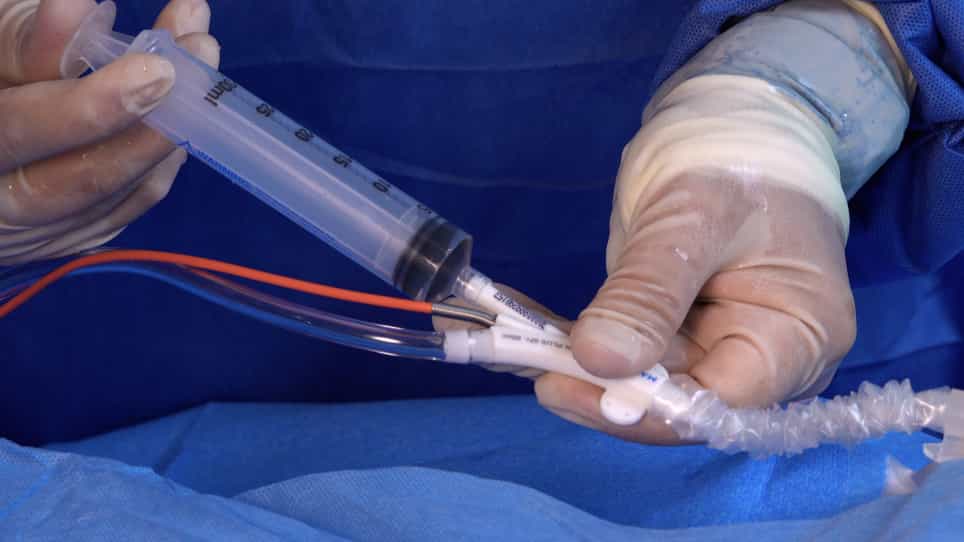

The Intra-Aortic Balloon Pump
Published on: February 5, 2021
βeta blocker interruption after uncomplicated myocardial infarction: rationale and design of the randomized ABYSS
Johanne Silvain1, Guillaume Cayla2, Emile Ferrari3
1Sorbonne Université, ACTION Study Group, INSERM UMRS1166, Hôpital Pitié-Salpêtrière (AP-HP), Paris, France.

Insights
Discontinuing beta-blockers after myocardial infarction (MI) is safe for patients with preserved ejection fraction. The ABYSS trial found no increased risk of major cardiovascular events when beta-blocker therapy was stopped in stable post-MI individuals.
Area of Science:
- Cardiology
- Clinical Trials
- Pharmacology
Background:
- Long-term beta-blocker use post-myocardial infarction (MI) with preserved ejection fraction is not well-studied with modern therapies.
- The efficacy of beta-blockers in stable post-MI patients without heart failure or reduced ejection fraction remains unclear.
Purpose of the Study:
- To evaluate the safety and efficacy of discontinuing beta-blocker therapy in stable post-MI patients with preserved left ventricular ejection fraction (LVEF).
- To determine if beta-blocker interruption is non-inferior to continuation regarding major adverse cardiovascular events.
Main Methods:
- The Assessment of Beta-blocker interruption 1 Year after an uncomplicated myocardial infarction on Safety and Symptomatic cardiac events requiring hospitalization (ABYSS) trial enrolled 3,700 patients.
- Patients with prior MI (>6 months) and LVEF >40%, on chronic beta-blocker therapy, were randomized to either interrupt or continue beta-blocker treatment.
- The primary endpoint was a composite of all-cause death, stroke, MI, or cardiovascular hospitalization. Quality of life was assessed using the EQ5D-5L questionnaire.
Main Results:
- Enrollment for the ABYSS trial has been completed.
- The study is designed to demonstrate the non-inferiority of beta-blocker interruption versus continuation.
- Patient-reported outcomes, including quality of life, are secondary endpoints.
Conclusions:
- The ABYSS trial investigates the cardiovascular safety of discontinuing beta-blockers in stabilized post-MI patients with preserved LVEF and no heart failure.
- This study reappraises the necessity of lifelong beta-blocker therapy in this specific patient population.
Background:
The long-term use of β-blocker after myocardial infarction (MI) when global left ventricular ejection fraction (LVEF) is preserved has not been studied in the era of modern myocardial reperfusion and secondary prevention therapies. It is unknown whether β-blockers are useful in stable post-MI patients without reduced LVEF and without heart failure.
Methods:
The Assessment of β-blocker interruption 1 Year after an uncomplicated myocardial infarction on Safety and Symptomatic cardiac events requiring hospitalization (ABYSS) Trial enrolled in 49 centers in France, 3,700 patients with a prior (>6 months) history of MI and a LVEF >40%, chronically treated with a β-blocker and without any major cardiovascular event (MACE) in the past 6 months. These patients were randomized to interruption or continuation of their β-blocker therapy. The primary objective is to demonstrate the noninferiority of interruption vs continuation of the β-blocker therapy on the primary composite endpoint of all-cause death, stroke, MI, hospitalization for any cardiovascular reason at the end of follow-up (accrual follow-up) with a one-year minimum follow-up for the last randomized patient. Secondary objectives will focus on patient reported outcomes with the evaluation of the quality of life before and after randomization with the EQ5D-5L questionnaire. Enrolment has been completed.
Conclusion:
The ABYSS trial evaluates the cardiovascular safety of β-blocker interruption in stabilized post-MI patients without heart failure nor reduced LVEF. ABYSS trial is a reappraisal of β-blockers life-long therapy in stable post-MI patients without reduced LVEF.
Clinical Trial Registration:
NCT03498066 (clinicaltrials.gov).
More Related Videos
 23:33
The WATCHMAN Left Atrial Appendage Closure Device for Atrial Fibrillation
Published on: February 28, 2012
 18:11
A Research Method For Detecting Transient Myocardial Ischemia In Patients With Suspected Acute Coronary Syndrome Using Continuous ST-segment Analysis
Published on: December 28, 2012
Related Concept Videos
 01:22
Heart Failure Drugs: β-Blockers
 01:31
Adrenergic Antagonists: ɑ and β-Receptor Blockers
 01:27
Adrenergic Antagonists: Pharmacological Actions of β-Receptor Blockers
 01:25
Antianginal Drugs: Calcium Channel Blockers and Ranolazine
CCBs, a diverse class that includes dihydropyridines (nifedipine) and diphenylalkylamines (verapamil and diltiazem), exert their effect by blocking calcium channels in cardiac and smooth muscle cells. This...
 01:26
Angina IV: Management
 01:28
Antihypertensive Drugs: Types of β-Blockers