Related Experiment Video
Updated: Aug 13, 2025
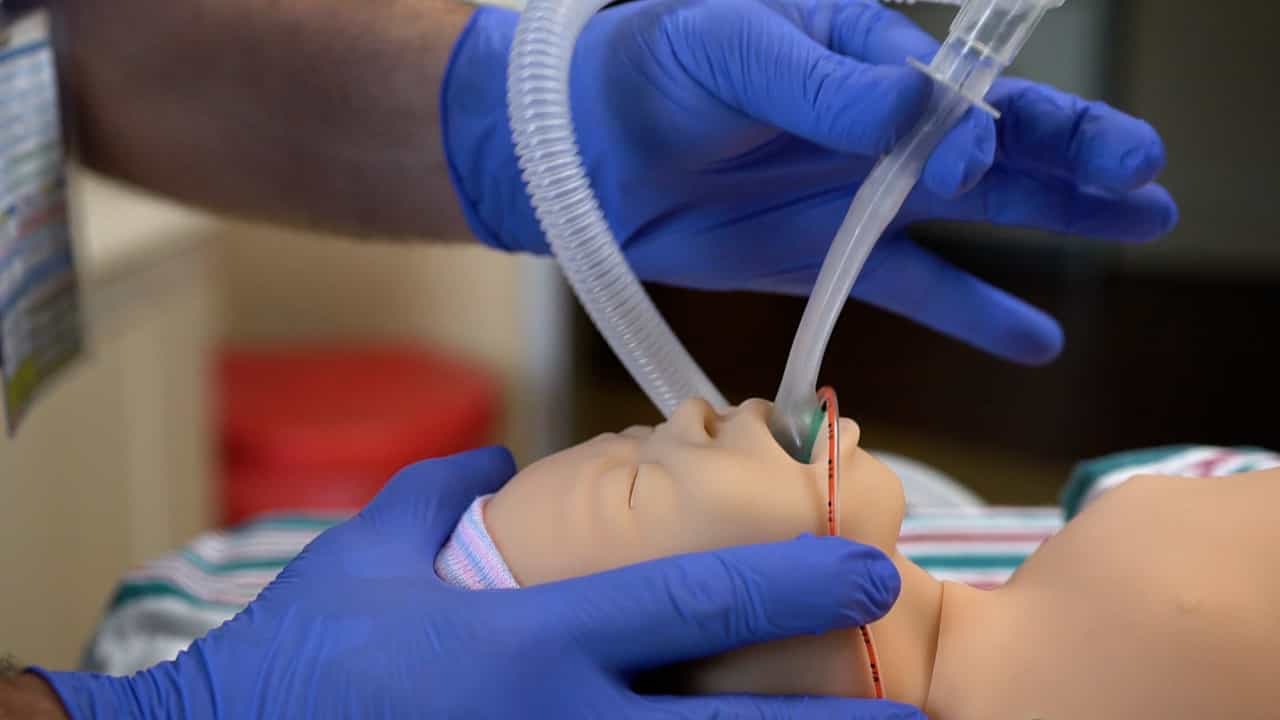

Laryngeal Mask Airway LMA Placement in a Neonatal Patient Simulator Using a Non-Inflatable Supraglottic Airway SGA
Published on: July 14, 2023
Premedication before laryngoscopy in neonates: Evidence-based statement from the French society of neonatology (SFN)
Xavier Durrmeyer1,2, Elizabeth Walter-Nicolet3,4, Clément Chollat5
1Neonatal Intensive Care Unit, Centre Hospitalier Intercommunal de Créteil, Créteil, France.

Context:
Laryngoscopy is frequently required in neonatal intensive care. Awake laryngoscopy has deleterious effects but practice remains heterogeneous regarding premedication use. The goal of this statement was to provide evidence-based good practice guidance for clinicians regarding premedication before tracheal intubation, less invasive surfactant administration (LISA) and laryngeal mask insertion in neonates.
Methods:
A group of experts brought together by the French Society of Neonatology (SFN) addressed 4 fields related to premedication before upper airway access in neonates: (1) tracheal intubation; (2) less invasive surfactant administration; (3) laryngeal mask insertion; (4) use of atropine for the 3 previous procedures. Evidence was gathered and assessed on predefined questions related to these fields. Consensual statements were issued using the GRADE methodology.
Results:
Among the 15 formalized good practice statements, 2 were strong recommendations to do (Grade 1+) or not to do (Grade 1-), and 4 were discretionary recommendations to do (Grade 2+). For 9 good practice statements, the GRADE method could not be applied, resulting in an expert opinion. For tracheal intubation premedication was considered mandatory except for life-threatening situations (Grade 1+). Recommended premedications were a combination of opioid + muscle blocker (Grade 2+) or propofol in the absence of hemodynamic compromise or hypotension (Grade 2+) while the use of a sole opioid was discouraged (Grade 1-). Statements regarding other molecules before tracheal intubation were expert opinions. For LISA premedication was recommended (Grade 2+) with the use of propofol (Grade 2+). Statements regarding other molecules before LISA were expert opinions. For laryngeal mask insertion and atropine use, no specific data was found and expert opinions were provided.
Conclusion:
This statement should help clinical decision regarding premedication before neonatal upper airway access and favor standardization of practices.

Related Concept Videos
 01:31
Skeletal Muscle Relaxants: Therapeutic Uses
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques