Related Experiment Video
Updated: Aug 13, 2025

Automated Measurement of Pulmonary Emphysema and Small Airway Remodeling in Cigarette Smoke-exposed Mice
Published on: January 16, 2015
Centrilobular Emphysema Is Associated with Pectoralis Muscle Reduction in Current Smokers without Airflow Limitation
Tomoki Maetani1, Naoya Tanabe1, Yusuke Shiraishi1
1Department of Respiratory Medicine, Graduate School of Medicine, Kyoto University, Kyoto, Japan.

Background:
Physiological and prognostic associations of centrilobular emphysema (CLE) and paraseptal emphysema (PSE) in smokers with and without chronic obstructive pulmonary disease (COPD) have been increasingly recognized, but the associations with extrapulmonary abnormalities, such as muscle wasting, osteoporosis, and cardiovascular diseases, remain unestablished.
Objectives:
The aim of the study was to investigate whether CLE was associated with extrapulmonary abnormalities independent of concomitant PSE in smokers without airflow limitation.
Methods:
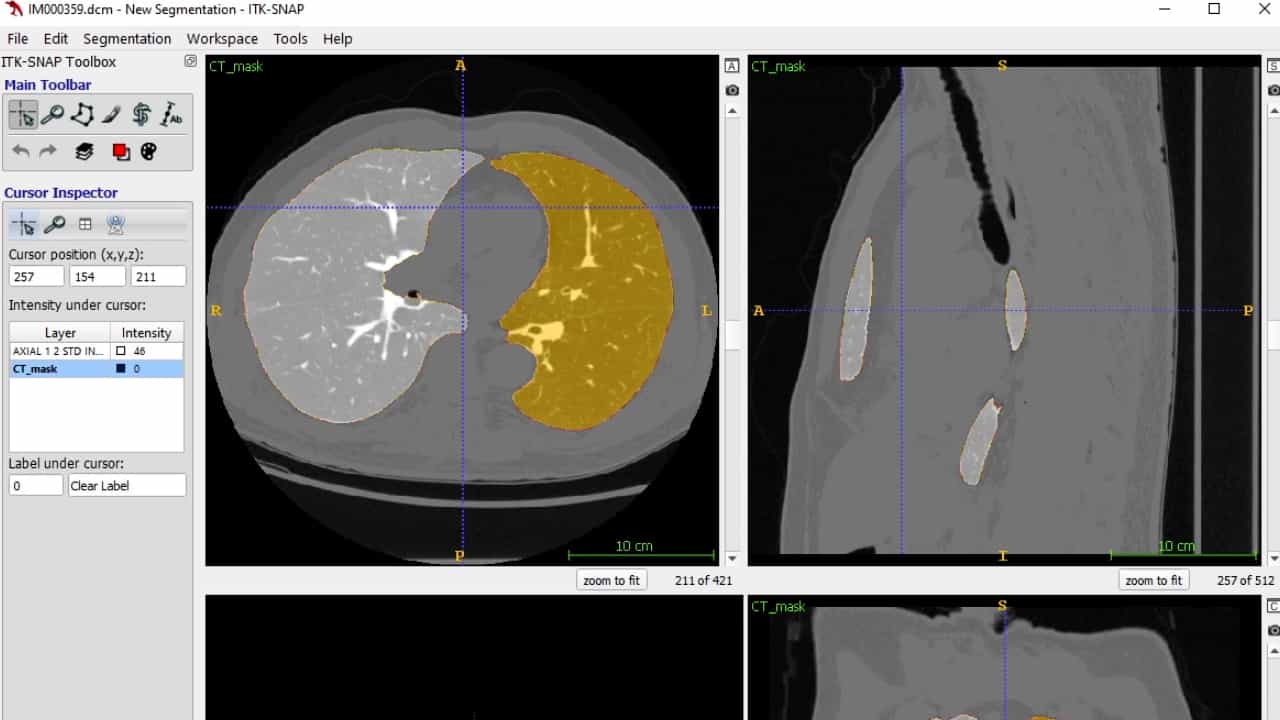
This retrospective study consecutively enrolled current smokers without airflow limitation who underwent lung cancer screening with computed tomography and spirometry. CLE and PSE were visually identified based on the Fleischner Society classification system. Cross-sectional areas of pectoralis muscles (PM) and adjacent subcutaneous adipose tissue (SAT), bone mineral density (BMD), and coronary artery calcification (CAC) were evaluated.
Results:
Of 310 current smokers without airflow limitation, 83 (26.8%) had CLE. The PSE prevalence was higher (67.5% vs. 23.3%), and PM area, SAT area, and BMD were lower in smokers with CLE than in those without (PM area (mean), 34.5 versus 38.6 cm2; SAT area (mean), 29.3 versus 36.8 cm2; BMD (mean), 158.3 versus 178.4 Hounsfield unit), while CAC presence did not differ. In multivariable models, CLE was associated with lower PM area but not with SAT area or BMD, after adjusting for PSE presence, demographics, and forced expiratory volume in 1 s.
Conclusions:
The observed association between CLE and lower PM area suggests that susceptibility to skeletal muscle loss could be high in smokers with CLE even without COPD.
More Related Videos
Related Concept Videos
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:22
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction
 01:25
Chronic Obstructive Pulmonary Disease-III: Symptoms and Complications.
Symptoms of COPD can be classified as primary or systemic. Primary symptoms relate to reduced airflow, while systemic or extrapulmonary symptoms relate to COPD's broader impact on the body.
Primary Symptoms of COPD:
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History