Related Experiment Video
Updated: Aug 12, 2025

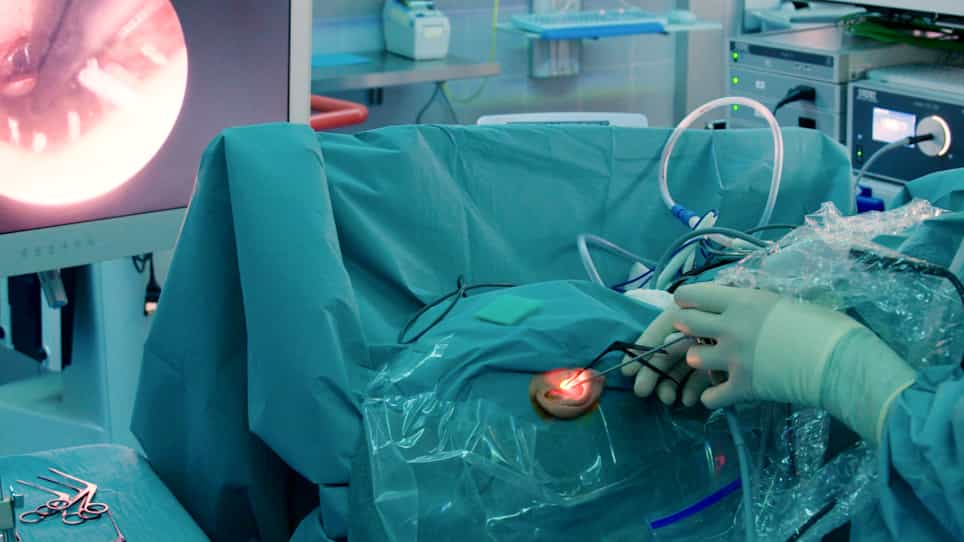
Role of Diffusion MRI Tractography in Endoscopic Endonasal Skull Base Surgery
Published on: July 5, 2021
Clival Chordomas in the Endoscopic Endonasal Era: Clinical Management, Outcomes, and Complications
Zane Schnurman1, Carolina Gesteira Benjamin2, Mary Miceli1
1Department of Neurosurgery, NYU Langone Health, New York, New York, USA.

Background:
Surgical management of skull base chordomas has changed significantly in the past 2 decades, most notably with use of the endoscopic endonasal approach (EEA), although high quality outcome data using these modern approaches remain scarce.
Objective:
To evaluate outcomes in a large series of patients treated by a single surgeon, using primarily the EEA.
Methods:
Between 2006 and 2020, 68 patients with skull base chordoma underwent resection using mostly the EEA. Complications, outcomes, and potential contributing factors were evaluated using Kaplan-Meier survival analysis and univariable and multivariable Cox proportional hazards models.
Results:
Overall 5-year survival was 76.3% (95% CI 61.5%-86.0%), and 5-year progression-free survival was 55.9% (95% CI 40.0%-69.0%). In multivariable analysis, radical resection was associated with significant reduction in risk of death (hazard ratio [HR] 0.04, 95% CI 0.005-0.33, P = .003) and disease progression (HR 0.05, 95% CI 0.01-0.18, P < .001). Better preoperative function status reduced risk of death (HR 0.42 per 10-point increase in Karnofsky Performance Scale, 95% CI 0.28-0.63, P < .001) and progression (HR 0.60 per 10-point increase in Karnofsky Performance Scale, 95% CI 0.45-0.78, P < .001). Localization at the clivus reduced risk of death (HR 0.02, 95% CI 0.002-0.15, P < .001) and progression (HR 0.24, 95% CI 0.09-0.68, P = .007) compared with tumors at the craniovertebral junction.
Conclusion:
In multivariable analysis, overall survival and progression-free survival of chordoma resection was most positively affected by radical resection, better preoperative functional status, and tumor location at the clivus rather than craniovertebral junction.

Related Concept Videos
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...