
Differences in red blood cell mass profiles impact intravascular volume and outcome risk in chronic heart failure
Wayne L Miller1, Diane E Grill2, Brian P Mullan3
1Department of Cardiovascular Diseases, Mayo Clinic, 200 First Street, SW, Rochester, MN, USA.

Aims:
To identify different red blood cell mass (RBCM) profiles, separate from haemoglobin concentrations, and their impact on blood volume expansion and clinical outcomes in chronic heart failure.
Methods And Results:
RBCM was measured at hospital discharge using standardized nuclear medicine indicator-dilution methodology in patients following diuretic treatment for clinical congestion. Individual RBCM phenotypes were prospectively identified and analysed for heart failure-related mortality or first rehospitalization over 1 year. Of 132 patients, 42 (32%) demonstrated normal RBCM, 36 (27%) RBCM deficit (true anaemia), and 54 (41%) RBCM excess (erythrocythemia). Dilutional 'anaemia' defined by haemoglobin <12 g/dL with normal or an excess in RBCM with plasma volume expansion was identified in 37 (28%) patients. There were 61 composite outcome events, which included 38 deaths (29% of cohort) occurring over the 1 year follow-up period [14/36 (39%) in RBCM deficit, 12/42 (29%) in normal RBCM, and 12/54 (22%) in RBCM excess subgroups]. By Kaplan-Meier and multivariate analyses, RBCM excess was independently associated with the best event-free survival while RBCM deficit (true anaemia) the poorest outcomes; both compared with normal RBCM (P < 0.001). Dilutional 'anaemia' demonstrated a lower risk compared with true anaemia (P = 0.03).
Conclusions:
Markedly different RBCM profiles are identifiable among comparably compensated heart failure patients, and this variability carries significant implications for post-hospital outcomes. Novel to this analysis and in contrast to RBCM deficit is the independent association of RBCM excess with better event-free survival compared with normal RBCM. The distinction of RBCM profiles to guide risk stratification and individualized patient management strategies warrants further study.
More Related Videos
 08:35
Oxygenation-sensitive Cardiac MRI with Vasoactive Breathing Maneuvers for the Non-invasive Assessment of Coronary Microvascular Dysfunction
Published on: August 17, 2022
 07:13
A Rat Model of Pressure Overload Induced Moderate Remodeling and Systolic Dysfunction as Opposed to Overt Systolic Heart Failure
Published on: April 30, 2020
Related Concept Videos
 01:17
Pathophysiology of Heart Failure
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send...
 01:29
Heart Failure II: Pathophysiology
 01:27
Regulation of Stroke Volume
Preload refers to the degree of stretch on the heart before it contracts. It's analogous to the stretching of a rubber band; the more it's stretched, the more forcefully it snaps back. This concept is encapsulated in the Frank-Starling law of the...
 01:19
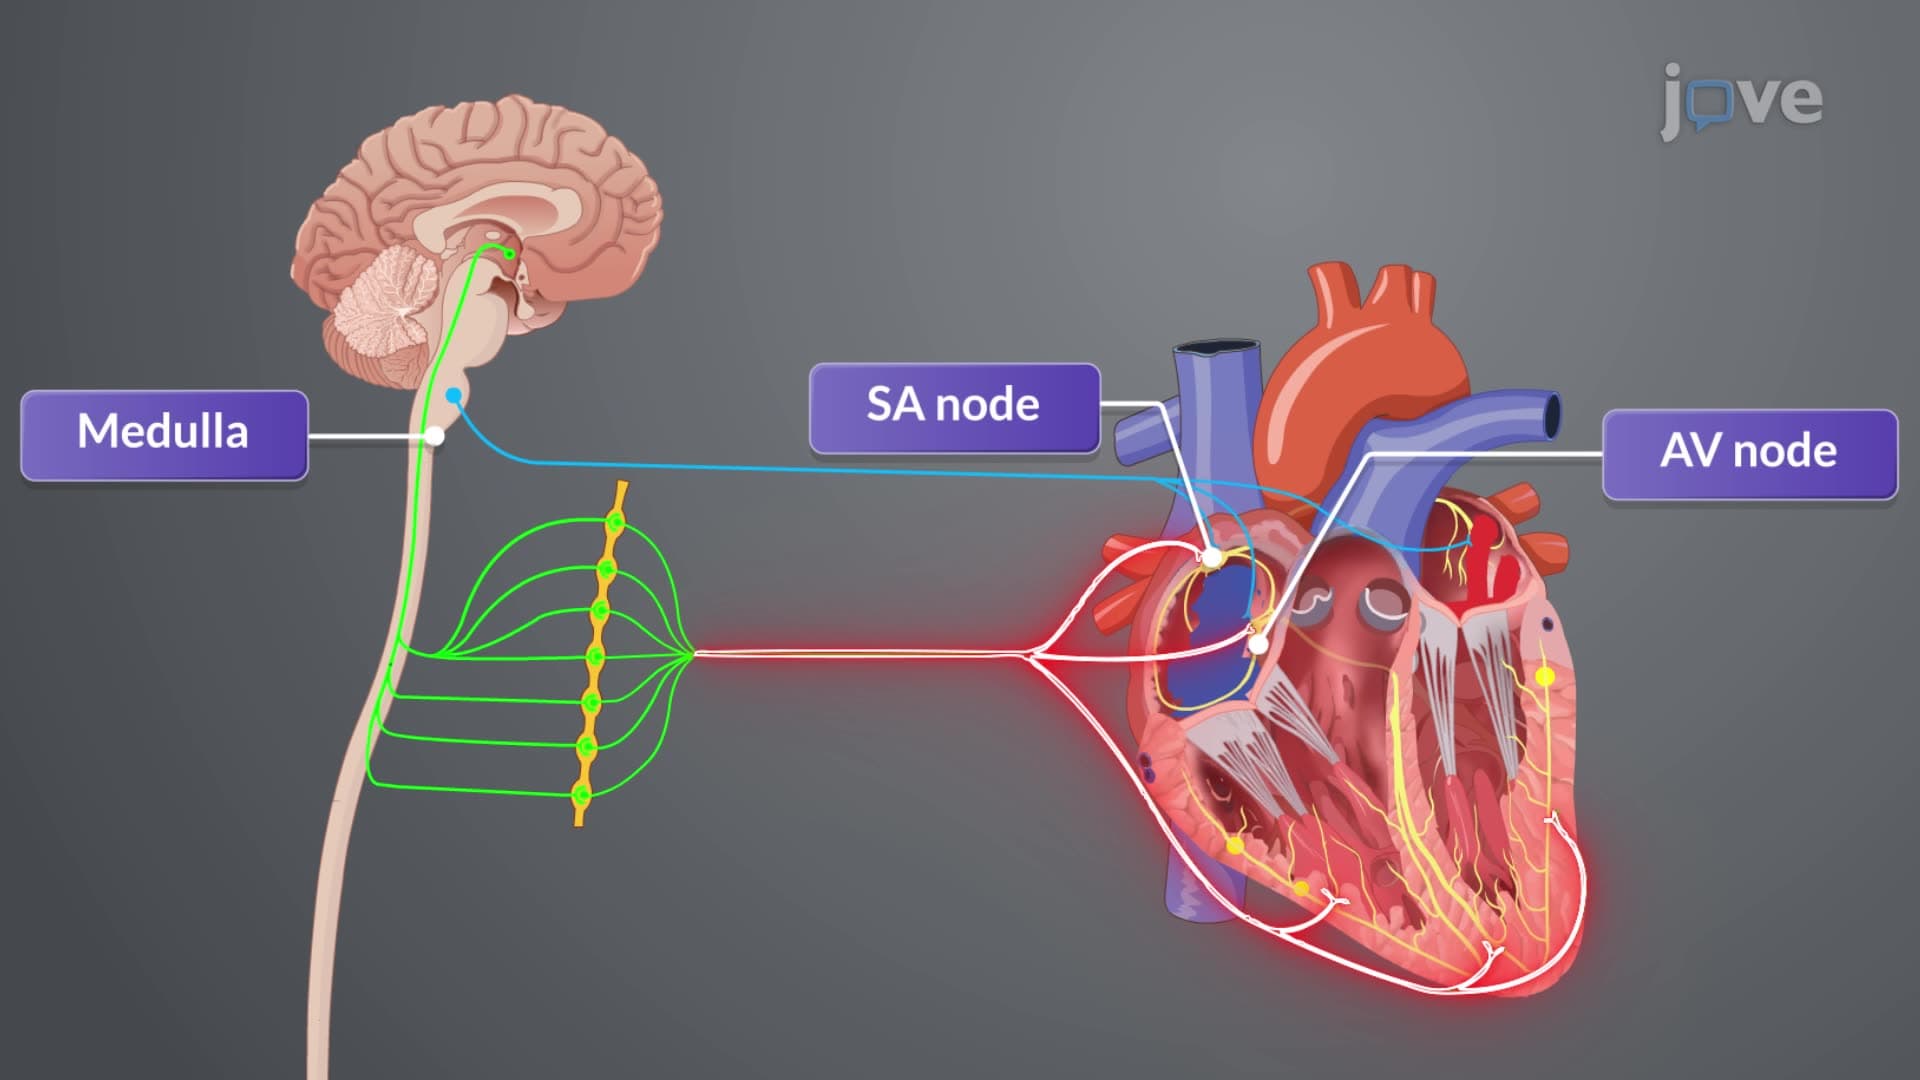
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart...