Related Experiment Video
Updated: Aug 12, 2025


Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
Craniocervical fusion in the paediatric population - case series of 21 patients
Oliver Richards1, Fozia Saeed1, Christopher Derham1
1Department of Neurosurgery, The Children's Hospital at The General Infirmary at Leeds, Leeds, United Kingdom.

Insights
Pediatric craniocervical fusion is a safe and effective treatment for instability, with 90% achieving bony fusion. Image guidance aids in complex cases, improving neurological outcomes.
Area of Science:
- Neurosurgery
- Pediatric Orthopedics
- Spinal Surgery
Background:
- Craniocervical junction (CCJ) instability in children presents unique surgical challenges due to anatomical variations and smaller structures.
- Syndromic abnormalities can further complicate CCJ pathologies in pediatric patients.
- Effective management strategies are crucial for improving outcomes in this vulnerable population.
Purpose of the Study:
- To review a series of pediatric patients undergoing craniocervical fusion.
- To identify common pathologies requiring CCJ stabilization.
- To evaluate the utility of intraoperative image guidance in these procedures.
Main Methods:
- Retrospective review of 21 pediatric patients undergoing craniocervical fixation (occipitocervical or atlantoaxial) over 12 years.
- Analysis of patient presentation, investigations, surgical procedures, and outcomes.
- Assessment of intraoperative navigation use and clinical/radiological results.
Main Results:
- 12 patients had C1-2 fixation, 9 had occipitocervical fusion for trauma, os odontoideum, congenital, or post-infectious instability.
- Average follow-up was 34 months; 90% showed radiological evidence of bony fusion.
- Neurological improvement or stabilization occurred in all patients; 5 patients with Trisomy 21 underwent C1-2 fixation.
Conclusions:
- Craniocervical fixation is a safe and viable treatment for pediatric CCJ disorders.
- Intraoperative navigation (frameless stereotaxy) can be beneficial in cases with distorted anatomy.
- Surgical stabilization leads to positive neurological and radiological outcomes in pediatric patients.
Purpose:
Craniocervical junction instability in a paediatric population presents a formidable challenge to the neurosurgeon. With a variety of anatomical variations, diminutive bony and ligamentous structures, possible superimposed syndromic abnormalities, the craniocervical junction is a technically challenging region to operate within. We aimed to review our series of patients to identify the common pathologies necessitating craniocervical fusion along with the use of intraoperative image guidance.
Methods:
We performed a retrospective review of twenty-one patients, with a mean age of 8.1 years, undergoing craniocervical fixations, involving either occipitocervical fusion or atlantoaxial fixation, from a single institution over a twelve-year period. The presentation, preoperative investigations, indication for surgery, surgical procedure, use of intraoperative navigation and clinical and radiological results were examined.
Results:
Twelve patients underwent primary C1-2 fixation, with the remaining 9 undergoing occipitocervical fusion. Five patients underwent surgery for traumatic instability, seven for os odontoideum, six for congenital anomalies and three for post-infectious instability. Follow up for 20 patients averaged 34 months (range 2-93 months). Five patients had Trisomy 21 and all underwent C1-2 fixation. Frameless stereotactic image guidance was utilised in five patients. No patients suffered immediate complications resulting from craniocervical junction fusion. Patients were observed to either neurologically improve (n = 6), or arrest their neurological deterioration following surgical intervention (n = 14), with concomitant radiological evidence of osseous fusion at follow up in 18 of 20 patients (90%). Two patients (10%) had radiological evidence of screw lucency, but neither required intervention because of being asymptomatic.
Conclusions:
Craniocervical fixation in a paediatric population is a viable and safe treatment modality for the management of disorders requiring stabilisation at the craniocervical junction. Our experience of utilising frameless stereotaxy in the setting of grossly distorted anatomical landmarks is also reported.
Related Concept Videos
 01:22
Sutures of the Skull
Sutures are immobile joints between adjacent bones of the skull. The narrow gap between the bones is filled with dense, fibrous connective tissue that unites the bones. The long sutures located between the skull bones are not straight but instead follow irregular, tightly twisting paths. These twisting lines tightly...
 01:19
Cranial and Spinal Meninges
Cranial Meninges
These meningeal layers cover the cranium. The dura mater is the outermost layer of cranial meninges. It is a thick and durable membrane of dense...
 01:16
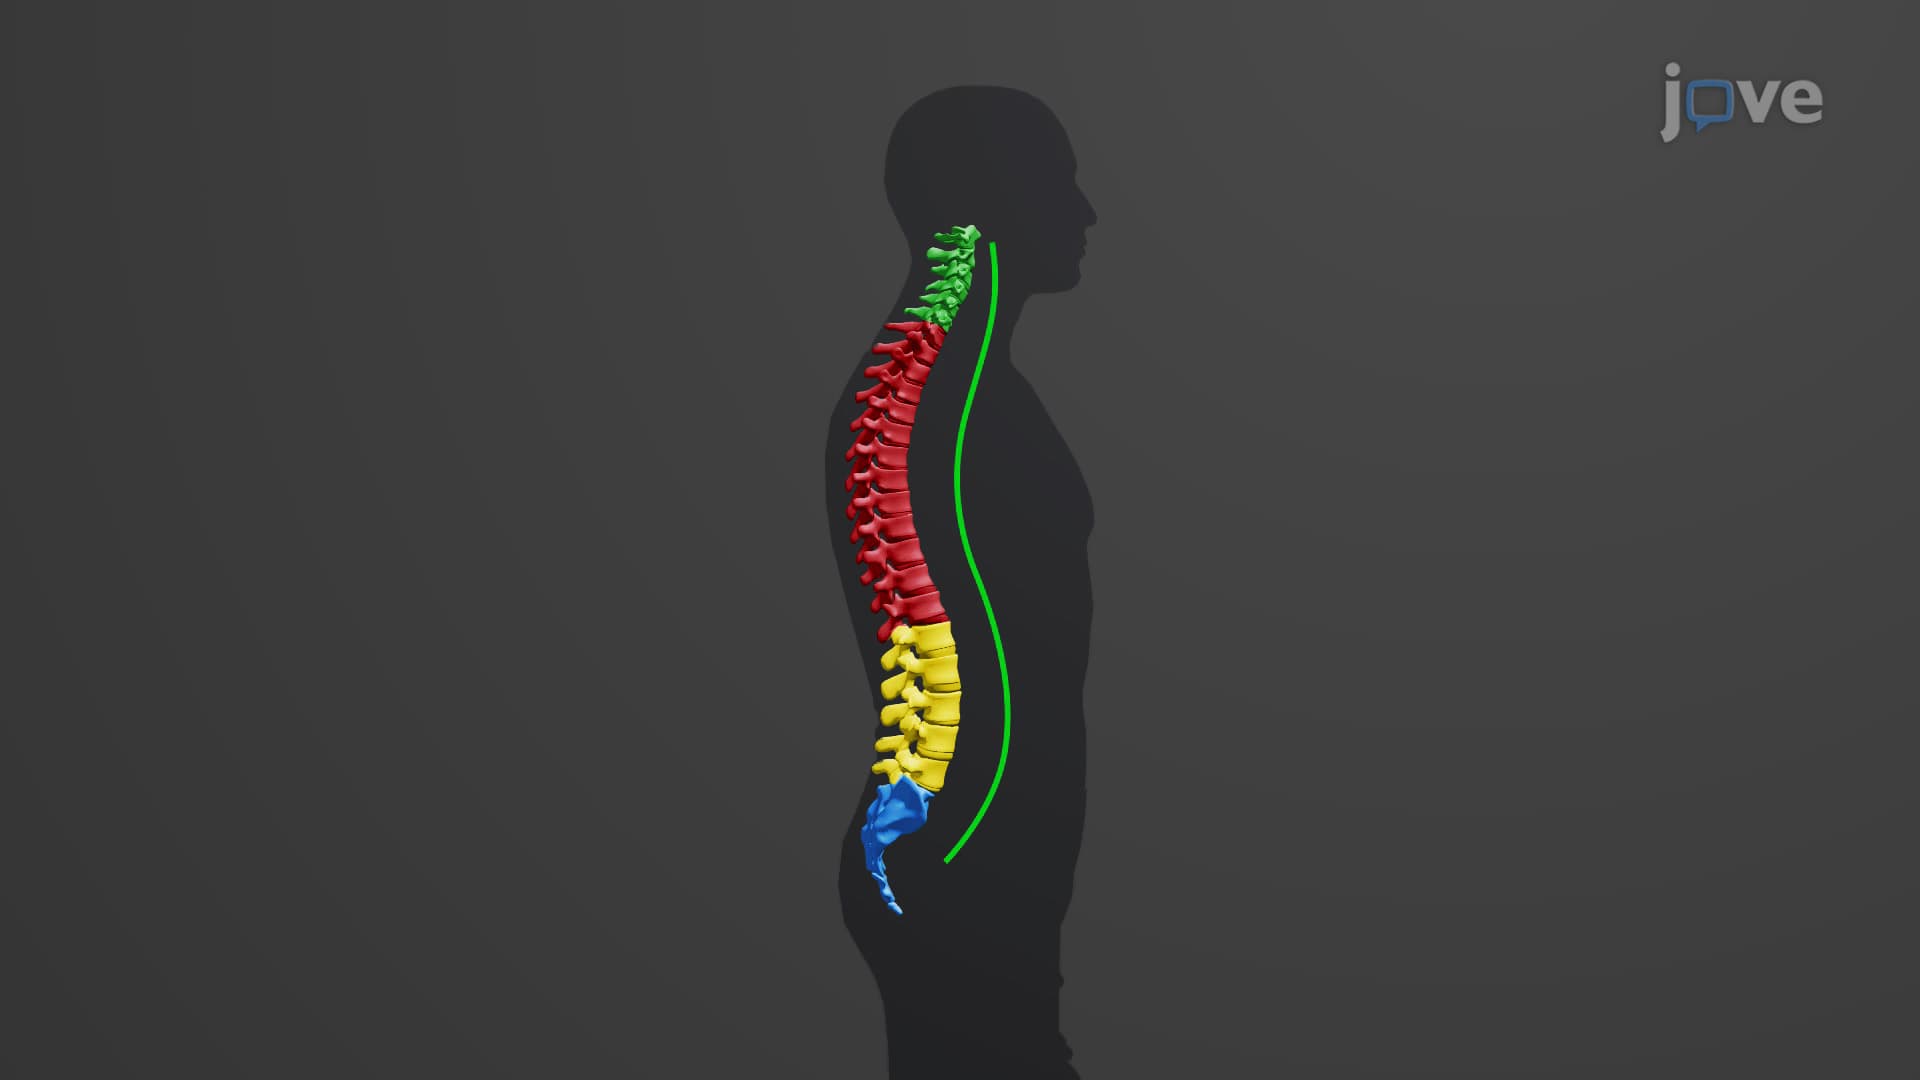
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form...