Related Experiment Video
Updated: Aug 12, 2025
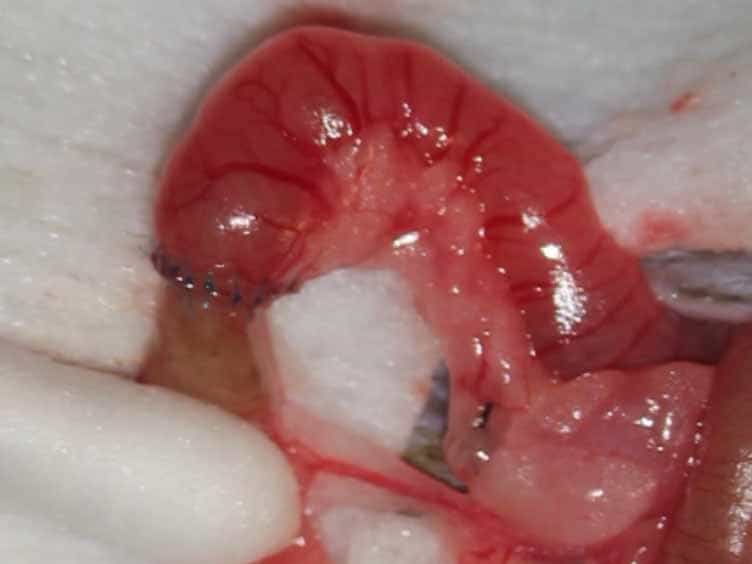
Murine Ileocolic Bowel Resection with Primary Anastomosis
Published on: October 29, 2014
Is the use of nonsteroidal anti-inflammatories after bowel anastomosis in trauma safe?
Thomas W Clements1, Jan-Michael Van Gent, Gabrielle E Hatton
1From the Department of Surgery and The Center for Translational Injury Research University of Texas Health Science Center at Houston; Red Duke Trauma Institute, and Mcgovern School of Medicine.

Background:
With an increasing interest in multimodal and opioid-reducing pain strategies, nonsteroidal anti-inflammatory drugs (NSAIDs) have become common place in the care of injured patients. Long-standing concerns of increased anastomotic leak (AL) rate with the use of NSAIDs, however, have persisted. We hypothesized that there would be no significant risk associated with NSAID use after bowel anastomosis in trauma patients.
Methods:
All patients presenting to a level 1 trauma center who required intestinal resection and anastomosis from 2011 to 2017 were reviewed. Patients receiving NSAIDs were compared with those managed without NSAIDs. Primary outcome of interest was anastomosis-related complications (AL, intra-abdominal abscess, anastomotic bleed, fascial dehiscence, fascial dehiscence, and enterocutaneous fistula). Multivariable logistic regression analyses were performed with propensity adjustment for inverse probability of NSAID treatment weights.
Results:
A total of 295 patients met the inclusion criteria with 192 receiving NSAIDs. Patients receiving NSAIDs had lower abdominal Abbreviated Injury Scale and Injury Severity Score ( p < 0.046). Arrival systolic blood pressure, diastolic blood pressure, and Glasgow Coma Scale were higher in the NSAID group ( p < 0.013). After propensity weighting, NSAID use was not a major predictor of anastomotic complication ( p = 0.39). There was an increased risk of AL with perioperative vasopressor exposure (odds ratio [OR], 3.33; 95% confidence interval [CI], 1.17-9.05; p < 0.001). Increasing red blood cell transfusions in the first 24 hours were associated with intra-abdominal complications (OR, 1.02; 95% CI, 1.00-1.04; p = 0.05). Nonsteroidal anti-inflammatory drug exposure demonstrated a weak association with AL (OR, 1.92; 95% CI, 0.97-3.90; p = 0.06).
Conclusion:
Consistent with previous studies, perioperative vasopressor exposure and increased number of red blood cell transfusions are risk factors for ALs and intra-abdominal complications, respectively. Nonsteroidal anti-inflammatory drug use in trauma patients with multiple risk factors may be associated with an increased risk of AL and should be used with caution in the setting of other established risk factors.
Level Of Evidence:
Therapeutic/Care Management; Level III.
Related Concept Videos
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:22
Aneurysm IV: Nursing Management
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:29
Drugs for Treatment of Ulcerative Colitis in IBD
 01:20
Drugs for Peptic Ulcer Disease: Prostaglandin Analogs as Mucosal Protective Agents
Non-steroidal anti-inflammatory drugs (NSAIDs) can induce peptic ulcers by inhibiting cyclooxygenase, decreasing...