Related Experiment Video
Updated: Aug 11, 2025
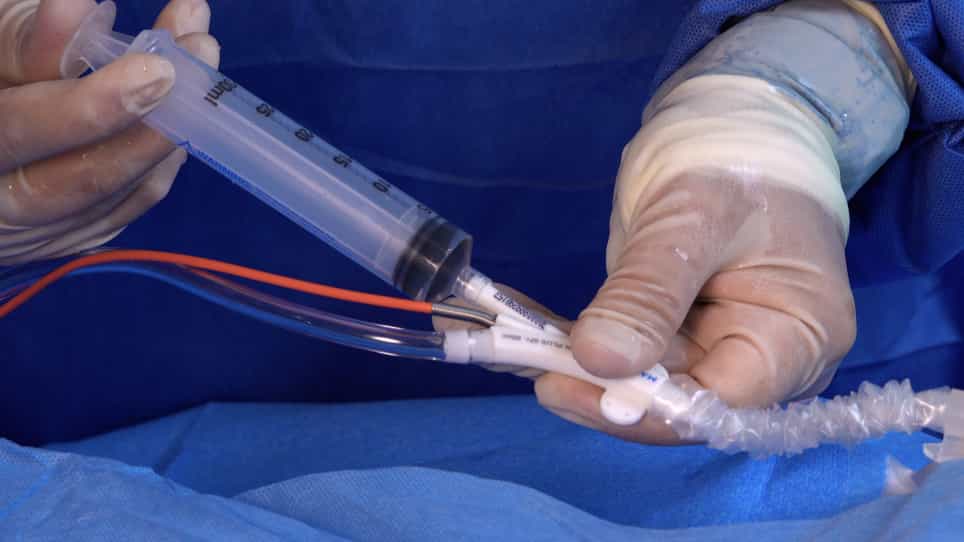

The Intra-Aortic Balloon Pump
Published on: February 5, 2021
Perfusionist removal of intra-aortic balloon pump catheters improves efficiency without an increase in complication
Richard Saczkowski1, Saverio Spada1, Kris Hromadnik2
1Interior Health Cardiac Sciences Program, Department of Cardiovascular Perfusion, Kelowna General Hospital, Kelowna, BC, Canada.

Insights
Certified clinical perfusionists (CCPs) can safely remove intra-aortic balloon pump (IABP) catheters, matching physician outcomes while improving clinical efficiency and resource allocation. This initiative enhances patient care in high-acuity settings.
Area of Science:
- Cardiovascular Medicine
- Medical Devices
- Healthcare Management
Background:
- Intra-aortic balloon pump (IABP) therapy is crucial but resource-intensive in high-acuity care areas.
- Limited bed space and high demand necessitate efficient management of IABP therapy.
- Initiatives to optimize IABP catheter removal are essential for improving healthcare efficiency.
Purpose of the Study:
- To compare the safety and efficacy of IABP catheter removal by certified clinical perfusionists (CCPs) versus physicians.
- To evaluate primary outcomes including site hematoma and limb-related complications.
- To assess the impact on clinical efficiency and resource allocation through staff surveys.
Main Methods:
- A comparative study involving 350 patients undergoing IABP removal.
- Outcomes data collected from the IABP quality assurance database.
- Surveys administered to bedside nurses, managers, CCPs, and physicians to gather qualitative feedback.
Main Results:
- No significant difference in limb complications or mortality between CCP and physician removal groups.
- Physician-led removal was associated with a higher rate of grade 3 hematomas (p=0.03).
- Survey data indicated improved efficiency in bed space allocation and reduced physician workload.
Conclusions:
- Perfusionist-led IABP catheter removal is a safe alternative to physician removal.
- This approach can enhance program efficiency and optimize resource utilization.
- Implementing CCP-led IABP removal programs can benefit high-acuity clinical settings.
Introduction:
The intra-aortic balloon pump (IABP) is one of the most utilized cardiac assist devices. Patients receiving IABP therapy are typically managed in high acuity clinical care areas with limited bed space and high demand. Our center instituted a certified clinical perfusionist (CCP) led initiative to remove IABP catheters in order to reduce IABP therapy time, hasten removal and improve efficiency.
Methods:
The purpose of the study is to compare outcomes for IABP removal by a certified clinical perfusionist to a physician. The primary outcome measures were site hematoma score and limb related complications. A survey was submitted to bedside nurses, managers/patient care coordinators, CCP's and physicians. The IABP quality assurance database was interrogated for the study.
Results:
There were 350 patients eligible for inclusion. The cohort was well balanced between CCP (n = 284) and physician (n = 66) groups for patient demographics, indication, insertion specifics and type of medical intervention. The majority of patients had no bruise or hematoma with perfusionist (n = 246, 87%) or physician (n = 58, 88%) (p = 0.78) removal. The physician group demonstrated a higher rate of grade 3 hematomas (p = 0.03). There was no statistically significant difference between CCP and physician groups for limb complications and mortality. Survey results showed an improved efficiency in bed space allocation, physician workload and a decreased IABP support time.
Conclusion:
There is no difference in limb complications between perfusionist and physician removal of IABP catheters. The survey demonstrate an improvement in resource allocation and efficiency. A perfusionist led IABP removal program can be done safely and may help improve program efficiency.
More Related Videos

Related Concept Videos
 01:26
Cardiac Catheterization IV: Nursing Management
 01:21
Cardiac Catheterization II: Right Heart Catheterization
 01:24
Cardiac Catheterization III: Left Heart Catheterization