Related Experiment Video
Updated: Aug 11, 2025

Primary Culture of Rat Adrenocortical Cells and Assays of Steroidogenic Functions
Published on: March 12, 2019
Adrenocortical, somatotropic, and antidiuretic response to nasal glucagon in healthy subjects
Emanuele Varaldo1, Fabio Bioletto1, Daniela Cuboni1
1Division of Endocrinology, Diabetology and Metabolism, Department of Medical Sciences, University of Turin, Turin 10126, Italy.

Objective:
The glucagon stimulation test involves the peptide intramuscular or subcutaneous administration for the diagnosis of hypopituitarism. To date, no data are available regarding its intranasal formulation. Our study intended to investigate the role of intranasal glucagon as a potential stimulus test for the evaluation of the corticotropic, somatotropic, and antidiuretic axes.
Design:
Non-randomized, single-blinded, cross-over study including 10 healthy subjects (50% women).
Methods:
All participants underwent 2 days of testing, and intranasal glucagon or placebo was administered. At baseline, every 15' up to +90', and then every 30' up to +180', a blood sample was taken for adrenocorticotropic hormone (ACTH), cortisol, growth hormone (GH), copeptin, glucose, insulin, sodium, potassium, and plasma osmolarity. At baseline and at the end of the test, urinary osmolarity was evaluated as well.
Results:
After administration of both glucagon and placebo, ACTH and cortisol values decreased progressively (P < 0.001), but in the drug group, the reduction in cortisol was less accentuated up to +90' (P < 0.05). Growth hormone values decreased after placebo administration (P < 0.001); on the other hand, after glucagon, an increasing, yet non-significant trend was observed (P = 0.096) with the difference between the two groups evident starting from +120' onwards (P < 0.005). The placebo administration led to a reduction of copeptin, while its stability was observed after glucagon administration. Six subjects developed hypokalemia (ie, potassium <3.5 mmol/L) post-glucagon, with the nadir at 45' (3.6 [3.2-3.8] mmol/L) significantly correlated with the immediate post-glycemic rise insulin peak (Spearman's rho -0.719; P = 0.019). No significant differences were observed compared to the other analytes tested.
Conclusions:
Intranasal glucagon administration is not an effective stimulus for hypophyseal secretion. Hypokalemia secondary to hyperinsulinemic rebound appears to be a frequent complication of its acute administration.


Related Concept Videos
 01:31
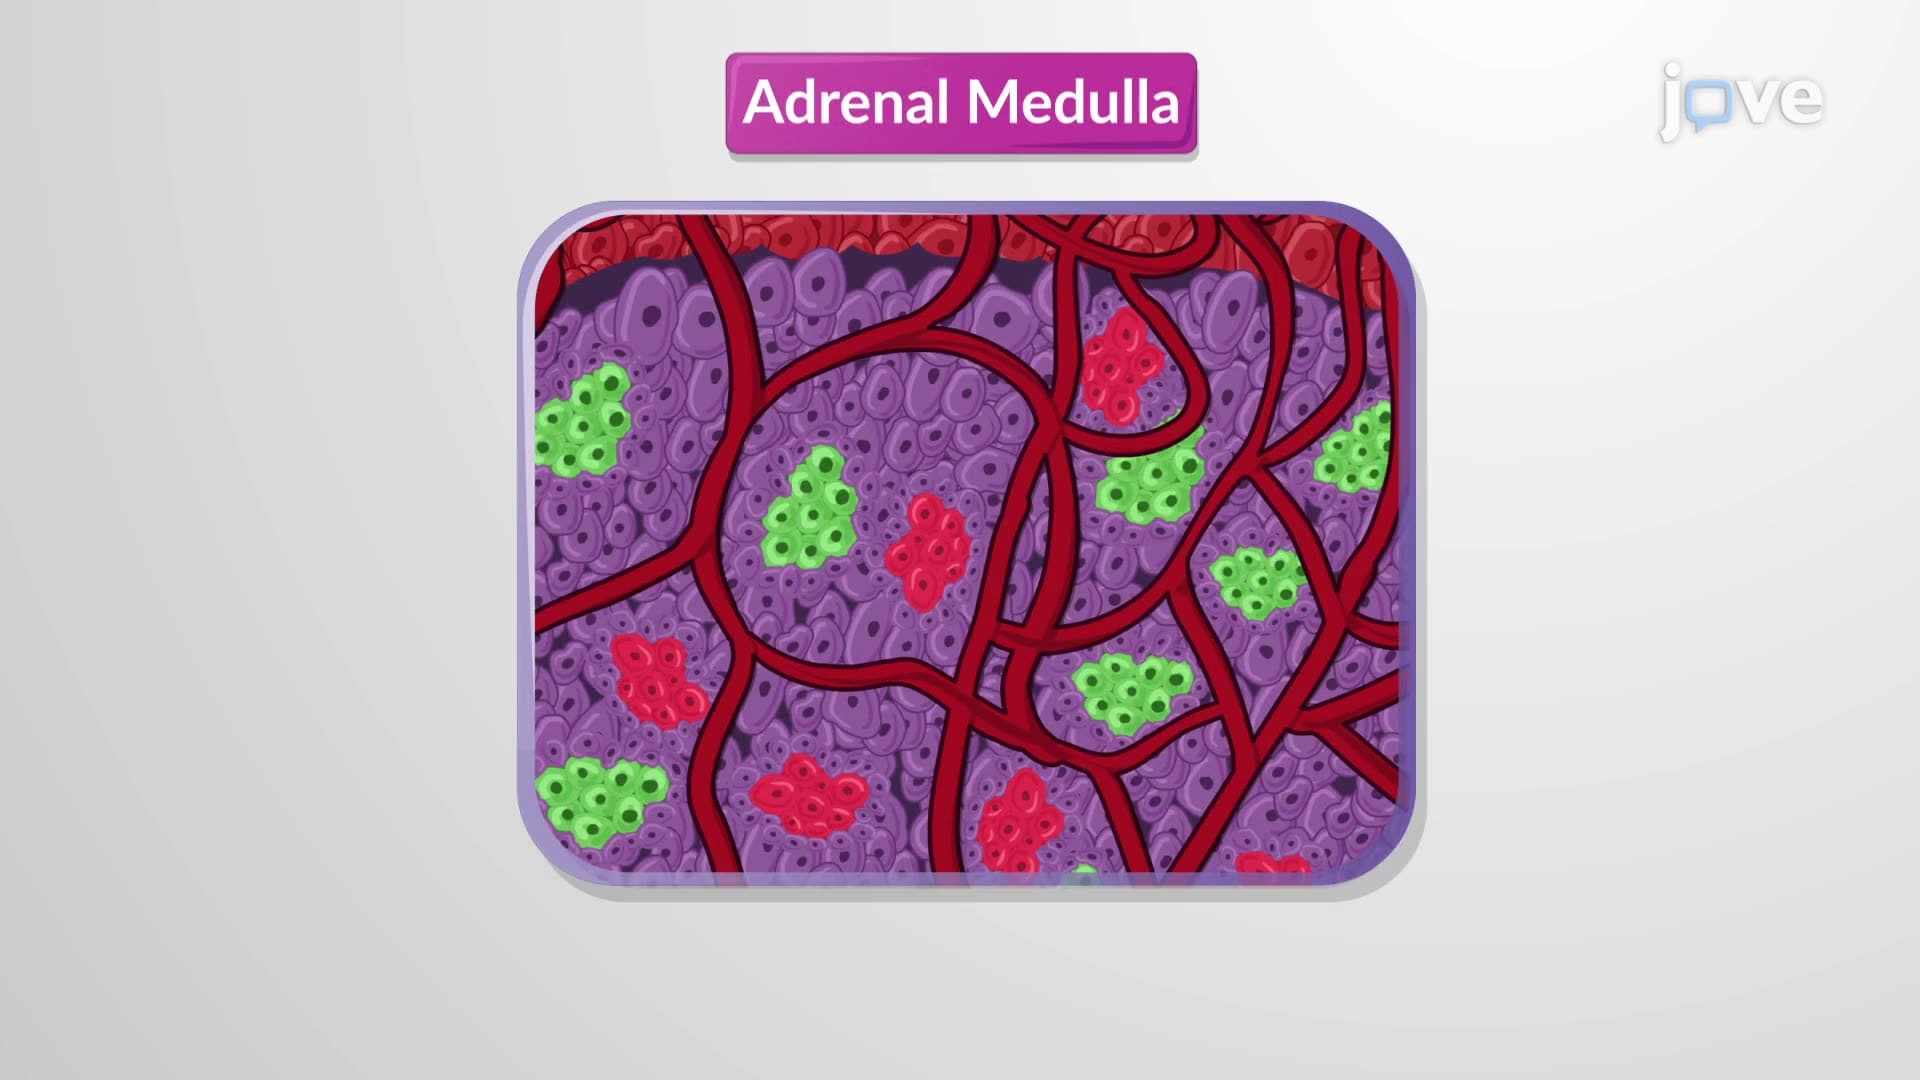
Hormones of the Adrenal Glands
The adrenal cortex, a powerhouse of hormone synthesis, generates over two dozen corticosteroid hormones. The zona glomerulosa produces mineralocorticoids, exemplified by aldosterone, influencing the electrolyte composition of body fluids. The synthesis of glucocorticoids such as cortisol and...
 01:15
Hypoglycemia and Glucagon
 01:37
Hypothalamic-Pituitary Axis
 01:17
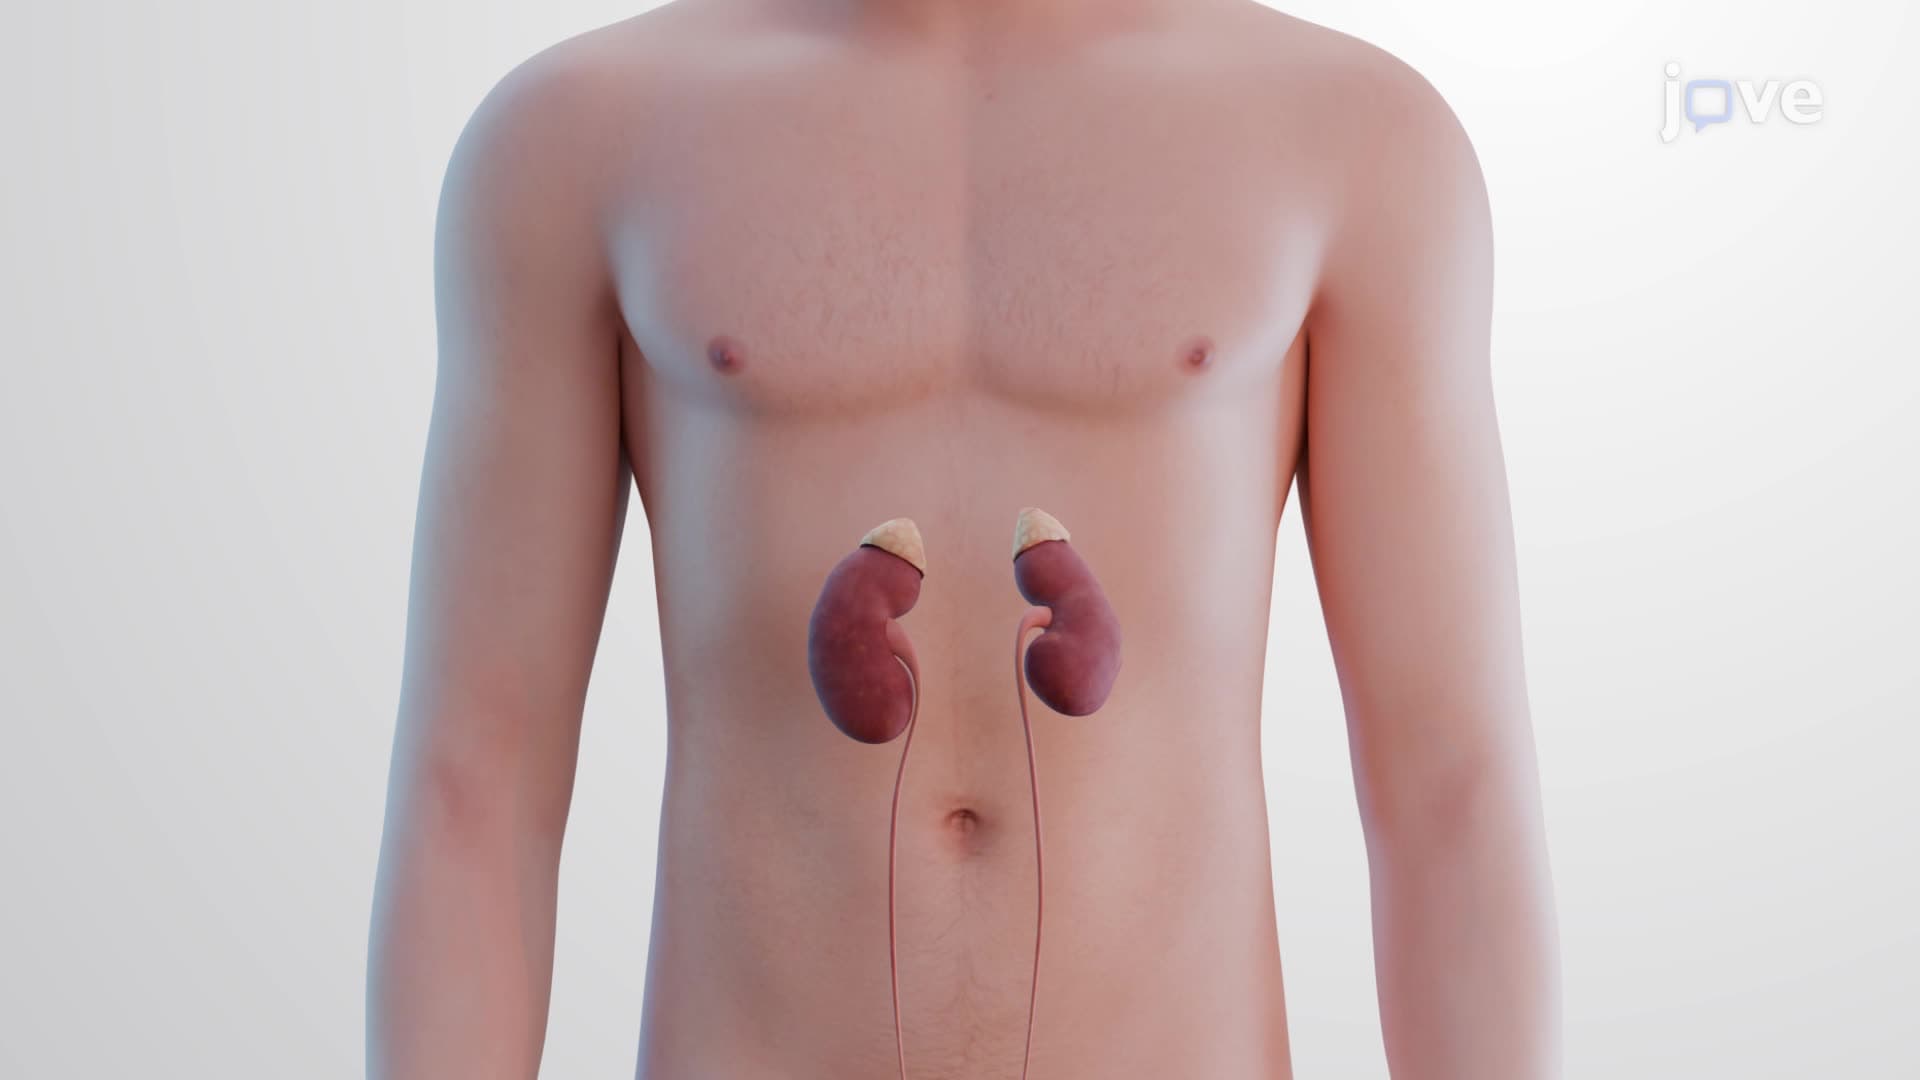
Anatomy of the Adrenal Glands
These glands possess a distinctive yellow tinge due to the stored cholesterol and fatty acids required for hormone synthesis. They are encased in a fibrous capsule and cushioned by fat.
The adrenal gland comprises two distinct...
 01:26
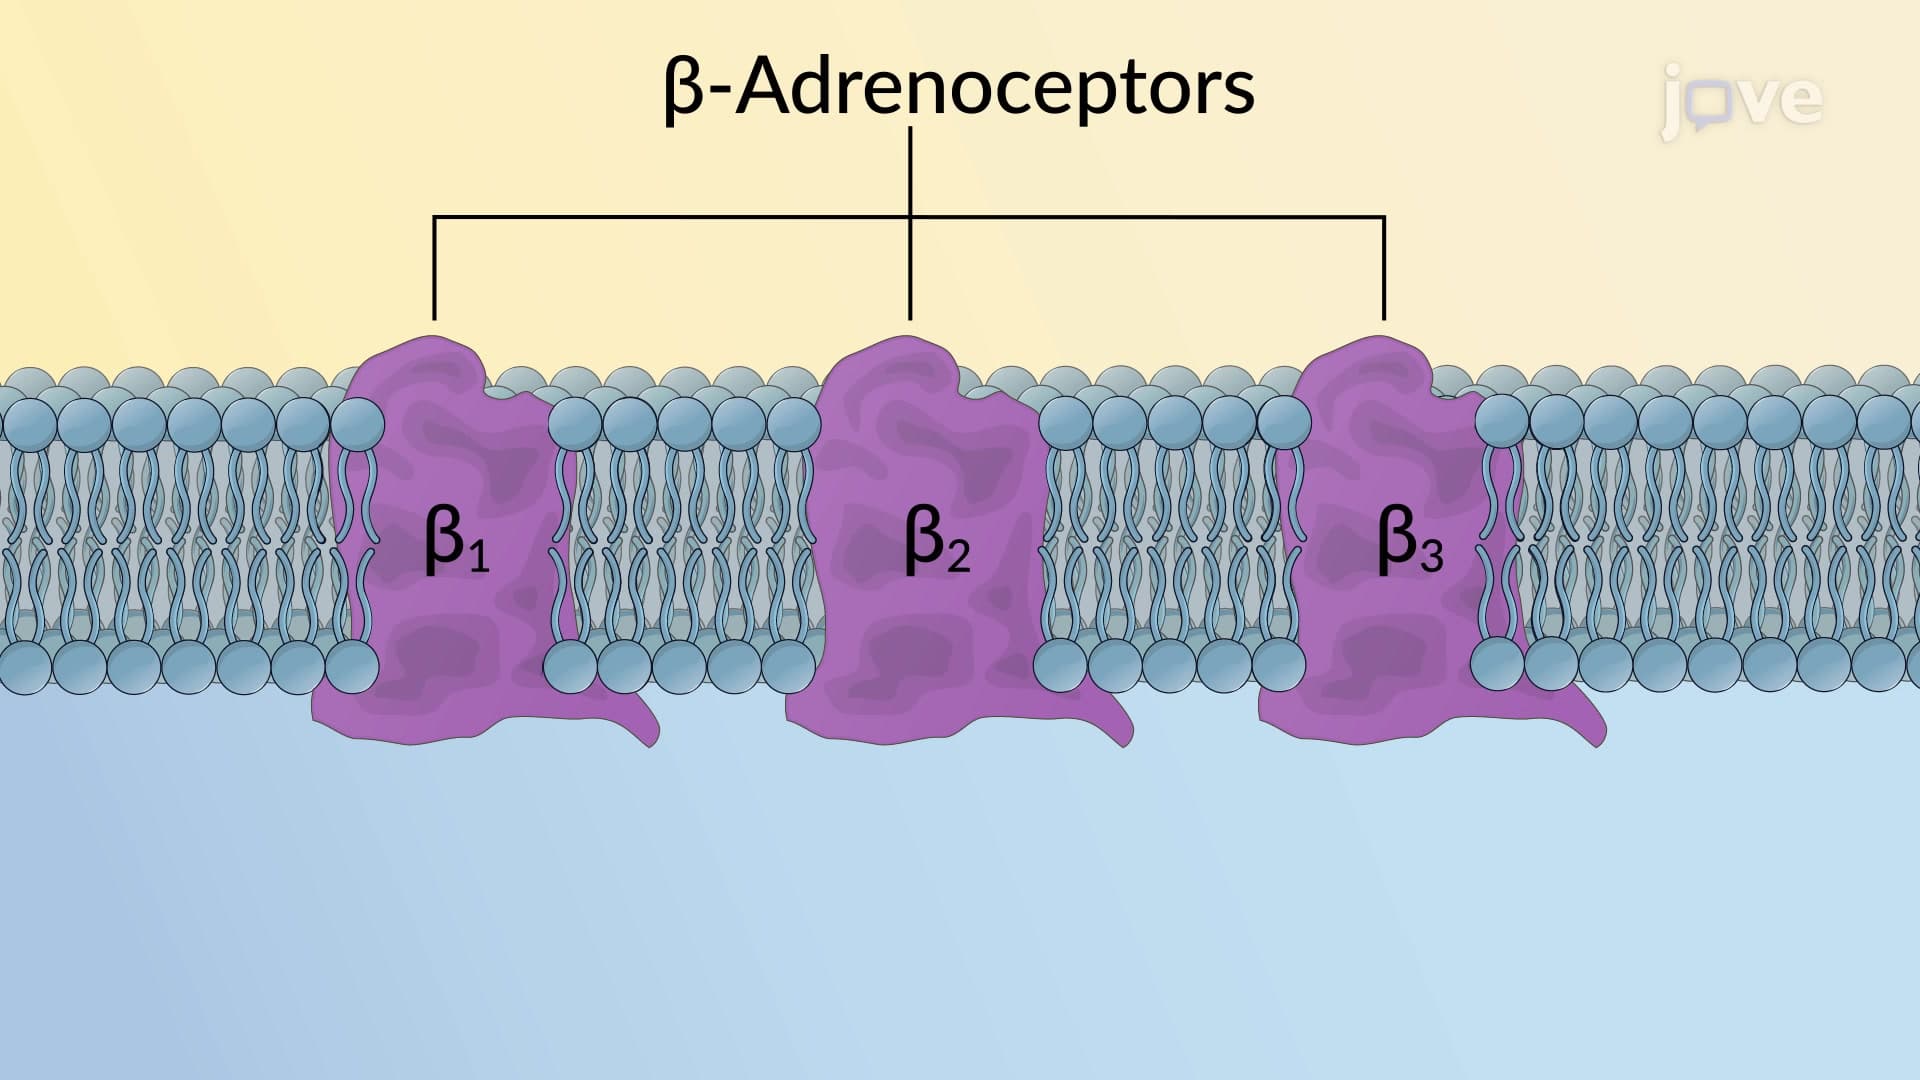
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors...
 01:16
Hormones Regulating Blood Glucose
In addition to accelerating glucose uptake and utilization, insulin has...