Related Experiment Video
Updated: Aug 11, 2025
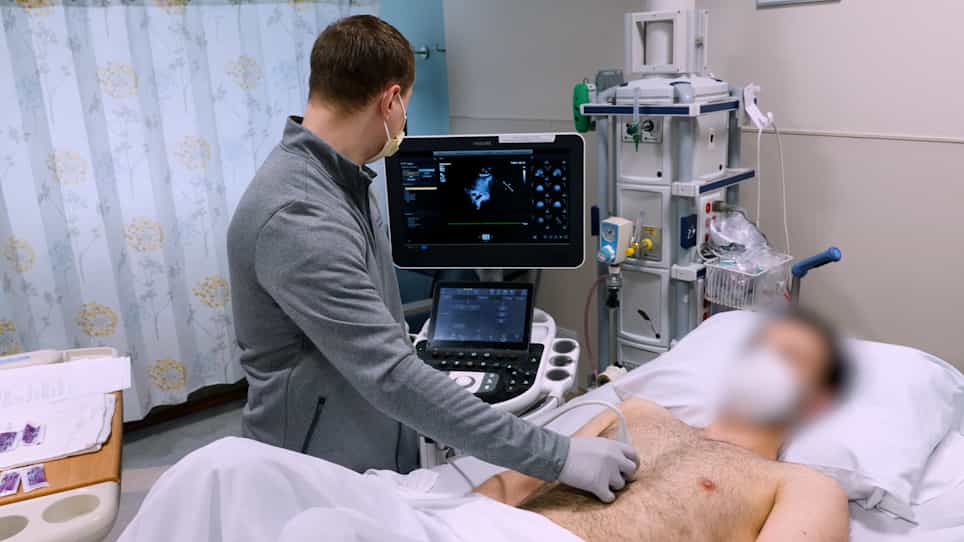

Image Acquisition Method for the Sonographic Assessment of the Inferior Vena Cava
Published on: January 13, 2023
Accuracy of Respiratory Variation in Inferior Vena Cava Diameter to Predict Fluid Responsiveness in Children Under
Nathalia Barros Campos1, Lícia Bertanha de Lima1, Isabel de Siqueira Ferraz1
1Pediatric Intensive Care Unit, Department of Pediatrics, State University of Campinas (UNICAMP), 126, Tessália Vieira de Camargo Street, Campinas, SP, 13083-887, Brazil.

Abstract:
Proper assessment of fluid responsiveness using accurate predictors is crucial to guide fluid therapy and avoid the serious adverse effects of fluid overload. The main objective of this study was to investigate the accuracy of respiratory variations in inferior vena cava diameter (∆IVC) to predict fluid responsiveness in mechanically ventilated children. This prospective single-center study included 32 children (median age and weight of 17 months and 10 kg, respectively) who received a fluid infusion of 10 ml kg-1 of crystalloid solutions over 10 min. ∆IVC and respiratory variation in aortic blood flow peak velocity (∆Vpeak) were determined over one controlled respiratory cycle before and after fluid loading. Thirteen (41%) participants were fluid-responders. ∆IVC, ∆Vpeak, stroke volume index, and cardiac index were found to be predictors of fluid responsiveness. However, the area under the ROC curve of ∆IVC was smaller when compared to ∆Vpeak (0.709 vs. 0.935, p < 0.012). The best cut-off values were 7.7% for ∆IVC (sensitivity, 69.2%; specificity 78.9%, positive predictive value, 69.2%; and negative predictive value, 78.9%) and 18.2% for ∆Vpeak (sensitivity, 84.6%; specificity, 89.5%; positive predictive value, 84.6%; negative predictive value, 89.5%). Changes in stroke volume were positively correlated with ∆IVC (ρ = 0.566, p < 0.001) and ∆Vpeak (ρ = 0.603, p < 0.001). A significant correlation was also found between changes in MAP and ∆Vpeak (ρ = 0.382; p = 0.031), but the same was not observed with ∆IVC (ρ = 0.011; p = 0.951). In conclusion, ∆IVC was found to have a moderate accuracy in predicting fluid responsiveness in mechanically ventilated children and is an inferior predictor when compared to ∆Vpeak.

Related Concept Videos
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:15
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:22
Respiratory Volumes and Capacities
 01:19
Special considerations while measuring oxygen saturation
Ensuring accuracy in vital sign recordings while prioritizing patient comfort and minimizing anxiety is...
 01:19
Respiratory Assessment: Purpose and Indications
Objectives and Importance:
The primary goal of respiratory assessment is to evaluate patients at early risk of clinical deterioration. Since respiratory distress often precedes other signs of declining health, breathing patterns and sounds become a...