Related Experiment Video
Updated: Aug 11, 2025
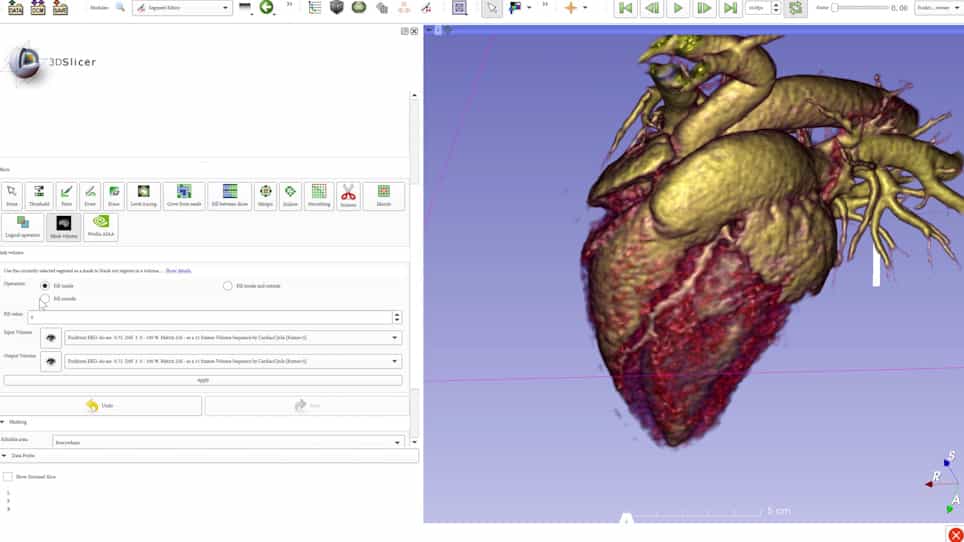

Four-Dimensional Computed Tomography-Guided Valve Sizing for Transcatheter Pulmonary Valve Replacement
Published on: January 20, 2022
Biventricular shape modes discriminate pulmonary valve replacement in tetralogy of Fallot better than imaging indices
Sachin Govil1, Charlène Mauger2,3, Sanjeet Hegde4,5
1Department of Bioengineering, University of California San Diego, 9500 Gilman Drive, MC 0412, La Jolla, CA, 92093-0412, USA.

Abstract:
Current indications for pulmonary valve replacement (PVR) in repaired tetralogy of Fallot (rTOF) rely on cardiovascular magnetic resonance (CMR) image-based indices but are inconsistently applied, lead to mixed outcomes, and remain debated. This study aimed to test the hypothesis that specific markers of biventricular shape may discriminate differences between rTOF patients who did and did not require subsequent PVR better than standard imaging indices. In this cross-sectional retrospective study, biventricular shape models were customized to CMR images from 84 rTOF patients. A statistical atlas of end-diastolic shape was constructed using principal component analysis. Multivariate regression was used to quantify shape mode and imaging index associations with subsequent intervention status (PVR, n = 48 vs. No-PVR, n = 36), while accounting for confounders. Clustering analysis was used to test the ability of the most significant shape modes and imaging indices to discriminate PVR status as evaluated by a Matthews correlation coefficient (MCC). Geometric strain analysis was also conducted to assess shape mode associations with systolic function. PVR status correlated significantly with shape modes associated with right ventricular (RV) apical dilation and left ventricular (LV) dilation (p < 0.01), RV basal bulging and LV conicity (p < 0.05), and pulmonary valve dilation (p < 0.01). PVR status also correlated significantly with RV ejection fraction (p < 0.05) and correlated marginally with LV end-systolic volume index (p < 0.07). Shape modes discriminated subsequent PVR better than standard imaging indices (MCC = 0.49 and MCC = 0.28, respectively) and were significantly associated with RV and LV radial systolic strain. Biventricular shape modes discriminated differences between patients who did and did not require subsequent PVR better than standard imaging indices in current use. These regional features of cardiac morphology may provide insight into adaptive vs. maladaptive types of structural remodeling and point toward an improved quantitative, patient-specific assessment tool for clinical use.
More Related Videos
 09:22
Chronic Thromboembolic Pulmonary Hypertension and Assessment of Right Ventricular Function in the Piglet
Published on: November 4, 2015
 05:31
Transcatheter Pulmonary Valve Replacement from Autologous Pericardium with a Self-Expandable Nitinol Stent in an Adult Sheep Model
Published on: June 8, 2022
Related Concept Videos
 01:20
Mitral Regurgitation I: Introduction
 01:27
Mitral Valve Prolapse I: Introduction
 01:16
Chambers of the Heart
Deoxygenated blood from the body is received in the right...
 01:16
Heart Valves
The AV valves prevent the backflow of blood from the ventricles to the atria during ventricular contraction. These valves function with the assistance of the chordae tendineae and papillary muscles. When the ventricles are relaxed, the chordae tendineae are slack, allowing blood to flow from the atria into the...
 01:22
Mitral Stenosis I: Introduction
 01:14
Ventilatory Modes
There are three ventilatory modes: full support, partial support, and spontaneous. These are described below.
Full Support Modes
Full support modes include controlled mechanical ventilation, continuous mandatory...