Related Experiment Video
Updated: Aug 11, 2025

Cell-based Assay Protocol for the Prognostic Prediction of Idiopathic Scoliosis Using Cellular Dielectric Spectroscopy
Published on: October 16, 2013
Pedicle morphometry analysis of main thoracic apex adolescent idiopathic scoliosis
Yudha Mathan Sakti1, Zikrina Abyanti Lanodiyu2, Mahardhika Ichsantyaridha2
1Orthopedic and Traumatology Department, Sardjito General Hospital/Gadjah Mada University, Yogyakarta, Indonesia. orthopaedi426@gmail.com.

Introduction:
Screw insertion during scoliosis surgery uses free-hand pedicle screw insertion methods. However, there is a wide variation in pedicle shapes, sizes, and morphometry, especially in scoliosis patients. CT scan pedicle measurements in main thoracic Lenke type 1 adolescent idiopathic scoliosis can help visualize this diversity. This study aimed to highlight the features of pedicle morphometry on the concave and convex sides, including pedicle diameter (width in axial and height in the sagittal plane), the depth to the anterior cortex, and Watanabe Pedicle classification in patients with main thoracic apex adolescent idiopathic scoliosis.
Materials And Methods:
This study was a cross-sectional observational study of Adolescent Idiopathic Scoliosis (AIS) patients whose apex in the main thoracic patient underwent deformity correction procedures. We used a three-dimensional CT scan to evaluate pedicle morphometry on the apex vertebrae, three consecutive vertebrae above and below the apex.
Results:
A total of 6 patients with apex main thoracic AIS with 84 pedicles consisting of 42 pedicles from each concave and convex curve were analyzed. All of the samples were female, with the mean age at the procedure being 21.2 ± 5.56. The mean cobb angle was 62° ± 23°, with the main apex between VT8-VT10. The size of the pedicle was bigger from upper to lower vertebrae. The mean pedicle depth, pedicle width, and pedicle height for the concave side were 36.06 ± 4.31 mm, 3.91 ± 0.66 mm, and 9.16 ± 1.52 mm, respectively. Meanwhile, the convex side is 37.52 ± 1.84 mm, 5.20 ± 0.55 mm, and 11.05 ± 0.70 mm, respectively. We found a significant difference between the concave and convex sides for the pedicle width and height. The concave and convex sides were mainly classified as type C (38%) and type A (50%) Watanabe pedicle.
Conclusion:
Pedicle width and pedicle height are significantly different between the concave and the convex side with convex side has better Watanabe pedicle classification. Pre-operative CT evaluation is essential for planning proper pedicle screw placement in AIS patients.

Related Concept Videos
 01:12
General Case of Eccentric Axial Loading
Consider a member subjected to equal and opposite forces that are applied along a line that does not coincide with the member's neutral axis. In unsymmetrical...
 01:16
Eccentric Axial Loading in a Plane of Symmetry
 01:09
Overview of the Axial Skeleton
The axial skeleton of the...
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...
 01:15
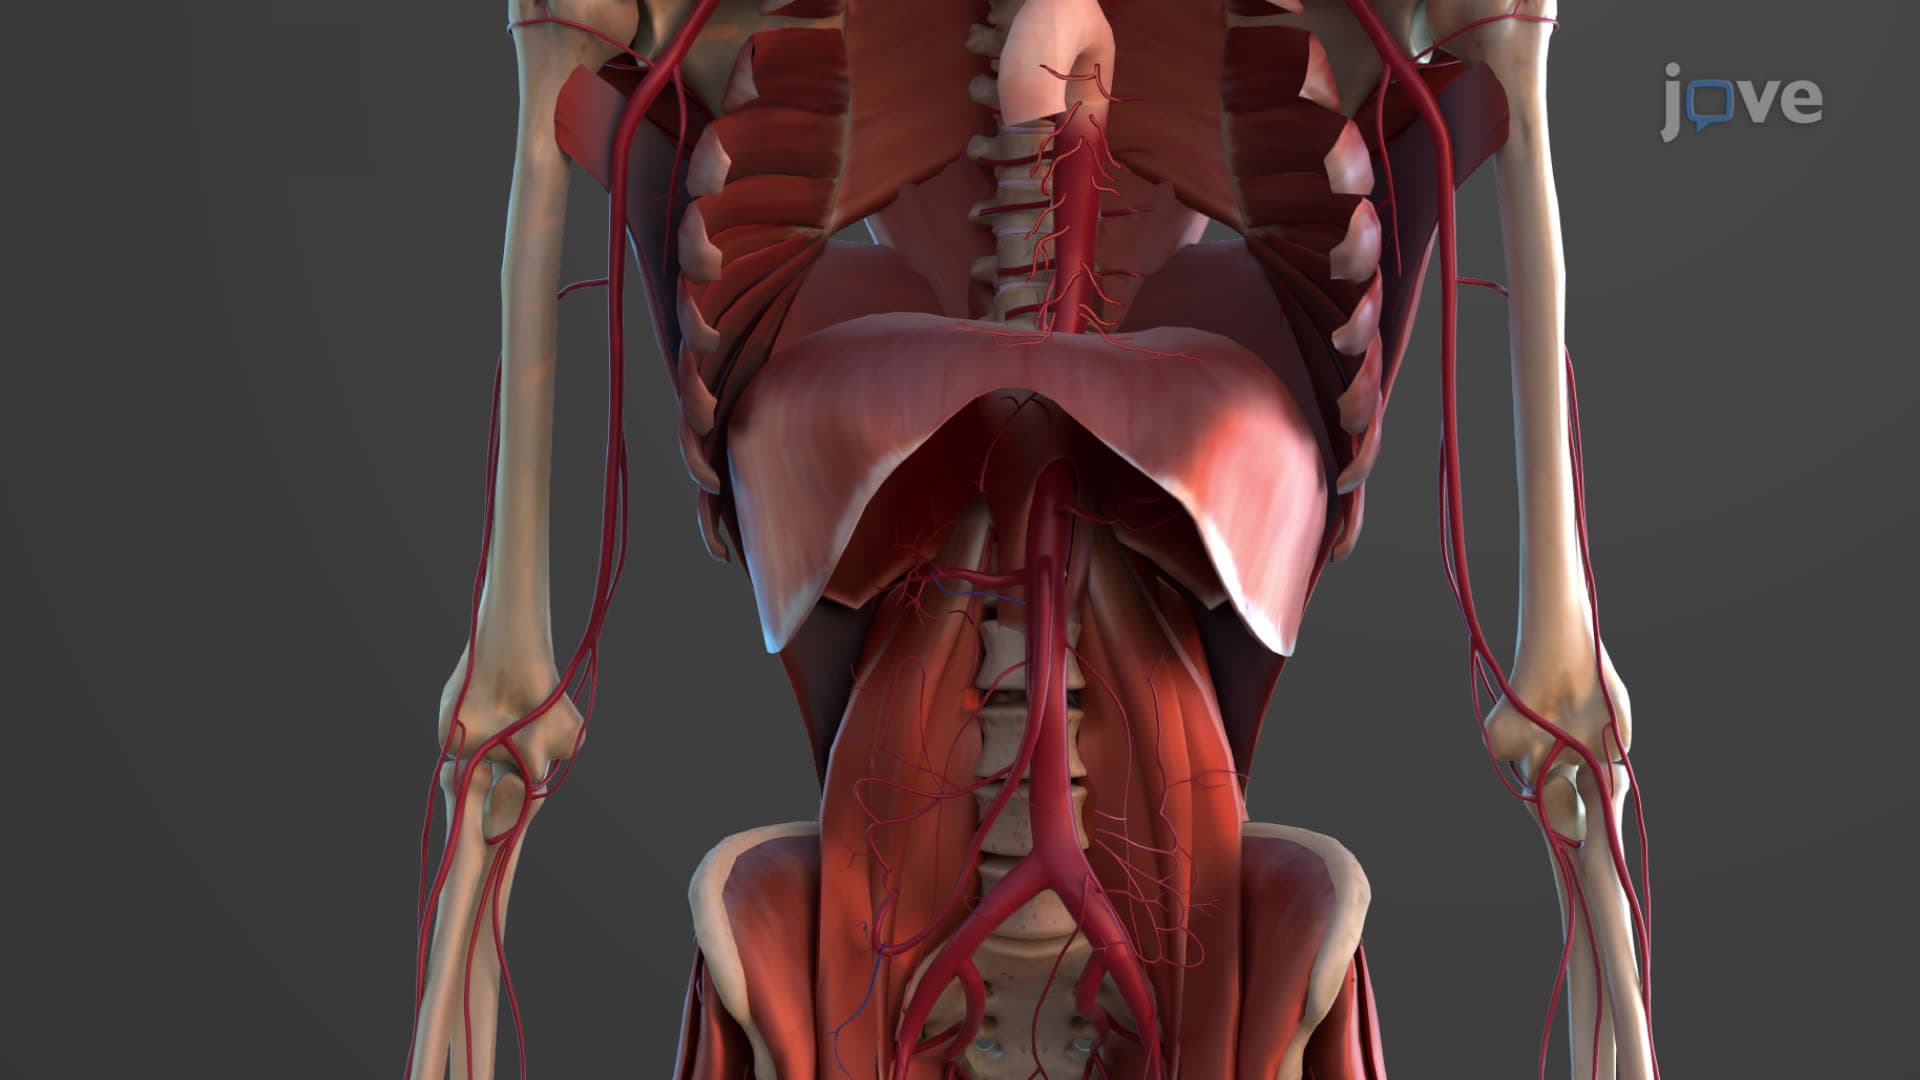
Thoracic Aorta
 01:16
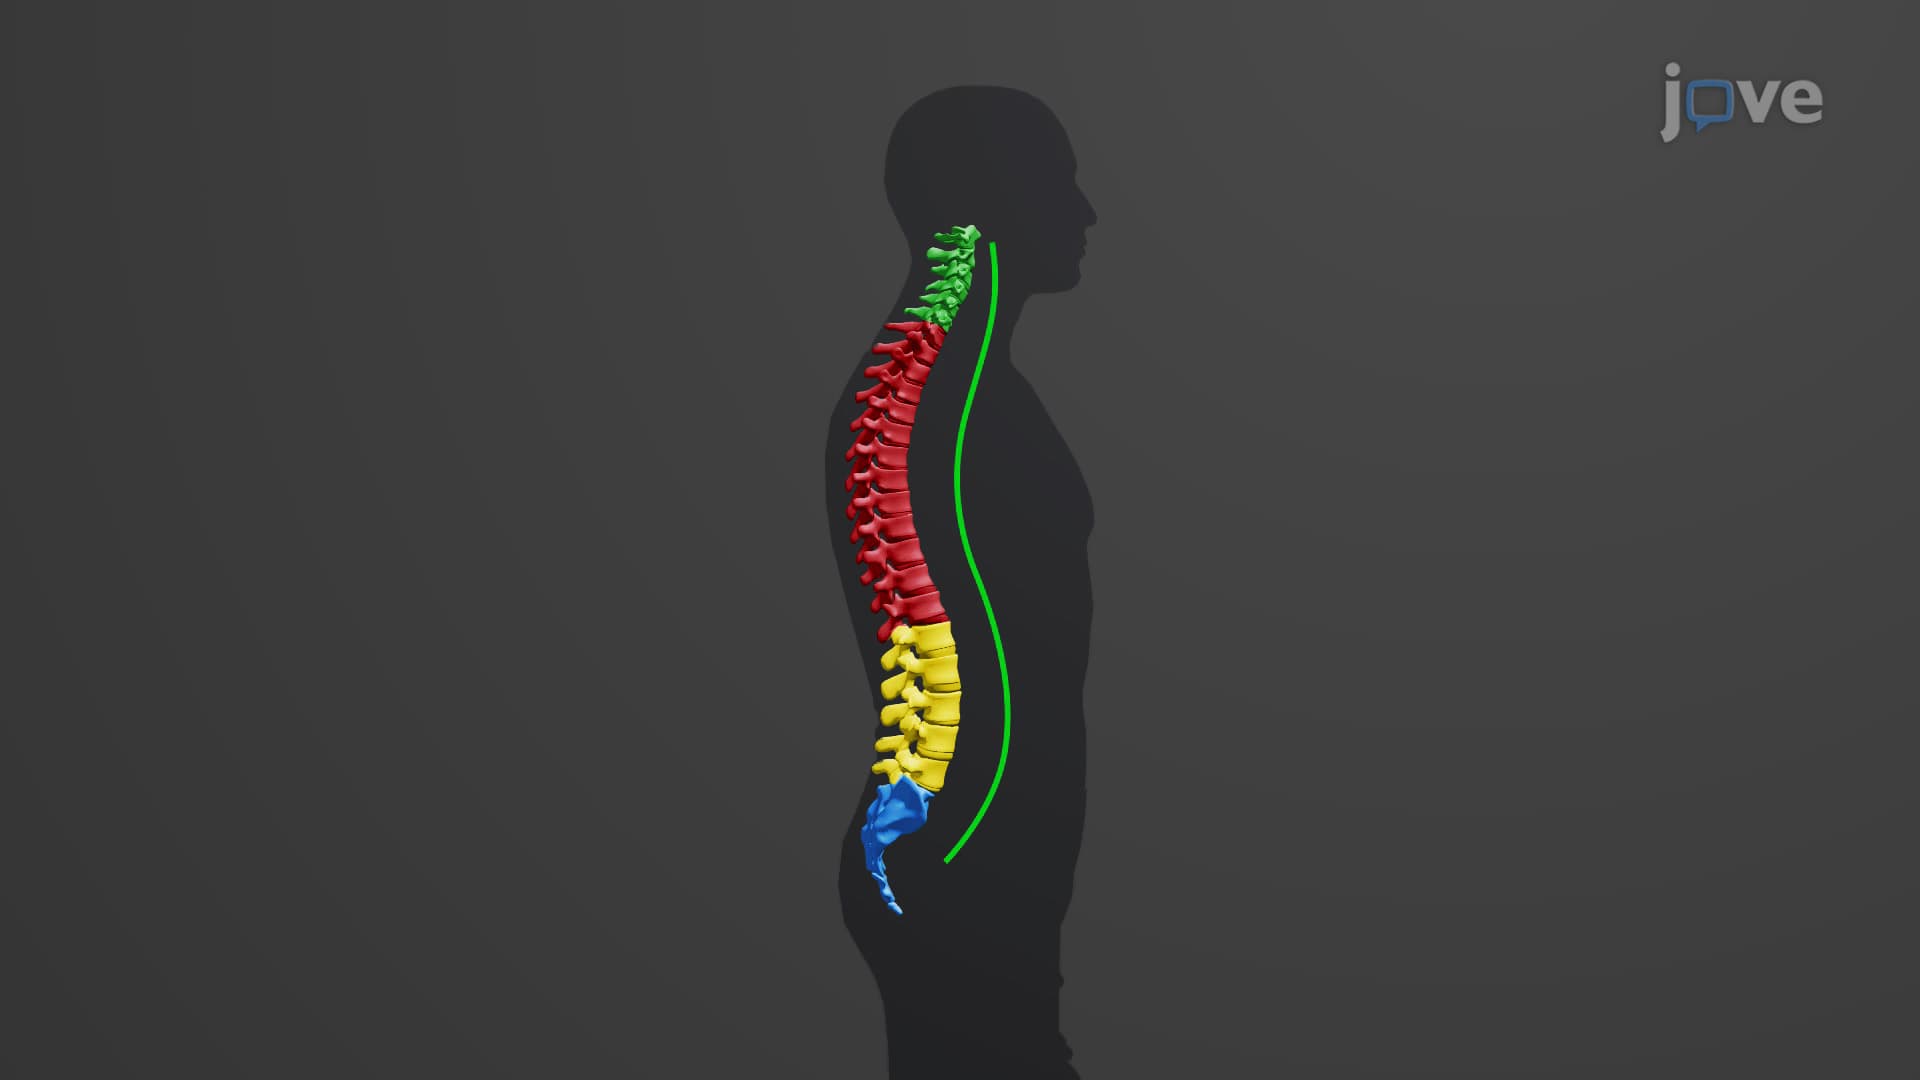
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form...