Related Experiment Video
Updated: Aug 11, 2025
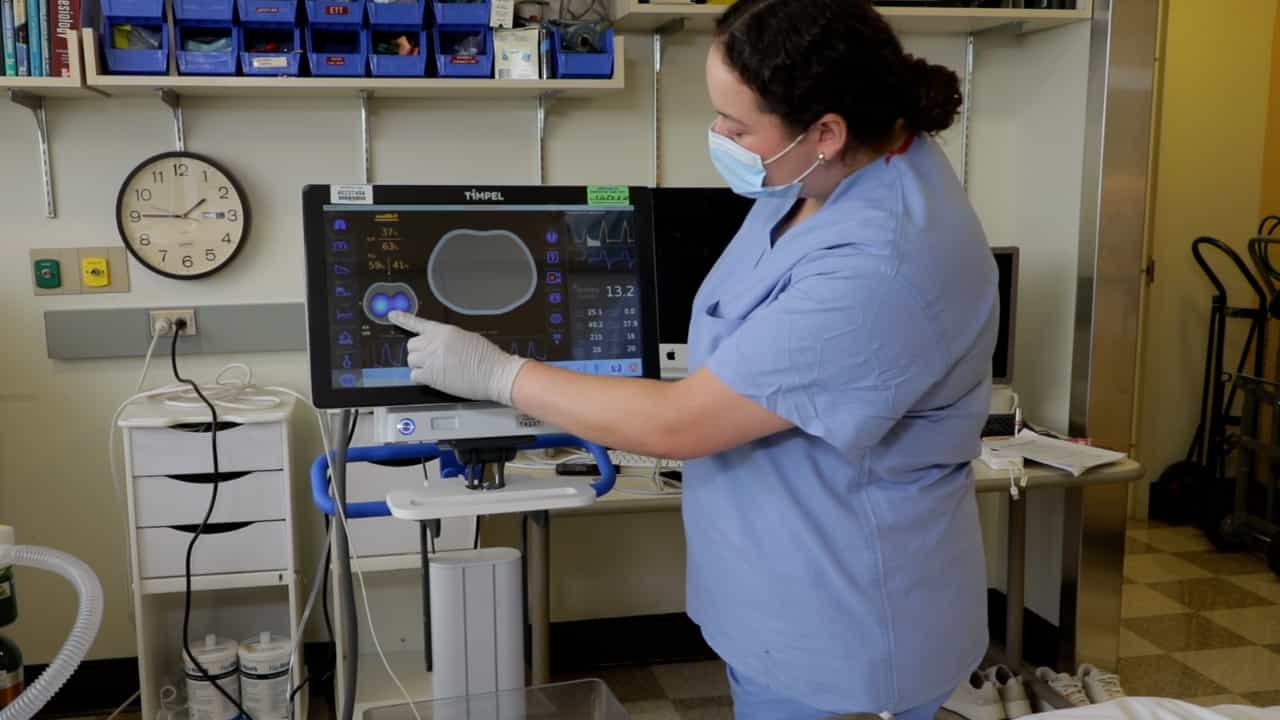
Monitoring Lung Function with Electrical Impedance Tomography in the Intensive Care Unit
Published on: September 6, 2024
The end-tidal alveolar dead space fraction for risk stratification during the first week of invasive mechanical
Anoopindar K Bhalla1, Ariya Chau2, Robinder G Khemani3
1Department of Anesthesiology and Critical Care Medicine, Children's Hospital Los Angeles, Department of Pediatrics, Keck School of Medicine, University of Southern California, 4650 Sunset Blvd, MS#12, Los Angeles, CA, 90027, USA. abhalla@chla.usc.edu.

Background:
The end-tidal alveolar dead space fraction (AVDSf = [PaCO2-PETCO2]/PaCO2) is a metric used to estimate alveolar dead space. Higher AVDSf on the first day of mechanical ventilation is associated with mortality and fewer ventilator-free days. It is not clear if AVDSf is associated with length of ventilation in survivors, how AVDSf performs for risk stratification beyond the first day of ventilation, or whether AVDSf adds predictive value to oxygenation (oxygenation index [OI]) or severity of illness (Pediatric Risk of Mortality [PRISM III]) markers.
Methods:
Retrospective single-center observational cohort study of children and young adults receiving invasive mechanical ventilation. In those with arterial or capillary blood gases, AVDSf was calculated at the time of every blood gas for the first week of mechanical ventilation.
Results:
There were 2335 children and young adults (median age 5.8 years [IQR 1.2, 13.2]) enrolled with 8004 analyzed AVDSf values. Higher AVDSf was associated with mortality and longer length of ventilation in survivors throughout the first week of ventilation after controlling for OI and PRISM III. Higher OI was not associated with increased mortality until ≥ 48 h of ventilation after controlling for AVDSf and PRISM III. When using standardized variables, AVDSf effect estimates were generally higher than OI for mortality, whereas OI effect estimates were generally higher than AVDSf for the length of ventilation in survivors. An AVDSf > 0.3 was associated with a higher mortality than an AVDSf < 0.2 within each pediatric acute respiratory distress syndrome severity category. The maximum AVDSf within 12 h of intensive care unit admission demonstrated good risk stratification for mortality (AUC 0.768 [95% CI 0.732, 0.803]). AVDSf did not improve mortality risk stratification when added to PRISM III but did improve mortality risk stratification when added to the gas exchange components of PRISM III (minimum 12-h PaO2 and maximum 12-h PCO2) (p < 0.00001).
Conclusions:
AVDSf is associated with mortality and length of ventilation in survivors throughout the first week of invasive mechanical ventilation. Some analyses suggest AVDSf may better stratify mortality risk than OI, whereas OI may better stratify risk for prolonged ventilation in survivors than AVDSf.
More Related Videos
 06:22
Surfactant Depletion Combined with Injurious Ventilation Results in a Reproducible Model of the Acute Respiratory Distress Syndrome ARDS
Published on: April 7, 2021
 09:36
Halogenated Agent Delivery in Porcine Model of Acute Respiratory Distress Syndrome via an Intensive Care Unit Type Device
Published on: September 24, 2020
Related Concept Videos
 01:29
Mechanical Ventilation I: Indication and Settings
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:22
Respiratory Volumes and Capacities
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation...
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement: