Related Experiment Video
Updated: Aug 8, 2026


Noninvasive Determination of Vortex Formation Time Using Transesophageal Echocardiography During Cardiac Surgery
Published on: November 28, 2018
Accuracy of stroke volume variation and pulse pressure variation in predicting fluid responsiveness undergoing
Cuicui Wang1, Zhe Feng1, Jinchen Cai1
1Department of Anesthesiology, The Sixth Medical Center of PLA General Hospital, Beijing, China.

Background:
Stroke volume variation (SVV) and pulse pressure variation (PPV) are based on the interaction between the heart and lungs during mechanical ventilation. However, debate continues as to whether SVV and PPV can accurately predict fluid responsiveness during the one-lung ventilation (OLV). We therefore undertook a systematic review and meta-analysis of clinical trials that investigated the diagnostic value of SVV and PPV in predicting fluid responsiveness undergoing OLV during thoracic surgery.
Methods:
The MEDLINE, EMBASE, WANFANG, and CENTRAL databases were systematically searched for studies on the use of SVV and/or PPV in patients undergoing OLV from 2010 to 2021. Heterogeneity was assessed using I2 statistics. The funnel diagram analysis was used to test publication bias. A fixed-effects model was used to calculate the pooled values of sensitivity, specificity, the diagnostic odds ratio (DOR), and the relevant 95% confidence intervals (95% CIs). The summary receiver operating characteristic (SROC) curves were estimated, and the areas under the SROC curve were calculated.
Results:
In total nine studies, comprising 452 patients were ultimately included in this meta-analysis, including 217 (48%) responders and 235 (52%) nonresponders. After combining the correlation coefficients, a slight heterogeneity was found between SVV and PPV in these selected studies (I2 SVV =19.7%, I2 PPV =15.3%), and the funnel diagram also showed that the P values of SVV and PPV were 0.33 and 0.26. After the pooled analysis, the respective sensitivity of SVV and PPV in predicting fluid responsiveness was 0.66 and 0.61, the specificity was 0.62 and 0.53, the positive likelihood ratios were 1.7 and 1.3, the negative likelihood ratios were 0.55 and 0.74, and the DORs were 3 and 2. The areas under the SROC curve of SVV and PPV were 0.68 and 0.60, respectively, according to STATA SE16 software, and the combined areas under the receiver operating characteristic (ROC) curve of SVV and PPV were 0.681 and 0.604, respectively, according to MedCalc19.0.4 software.
Conclusions:
Current evidence suggests that SVV and PPV are not suitable for guiding intraoperative fluid therapy due to their poor ability to predict fluid responsiveness in patients undergoing OLV, and we need a better indicator instead.
Related Concept Videos
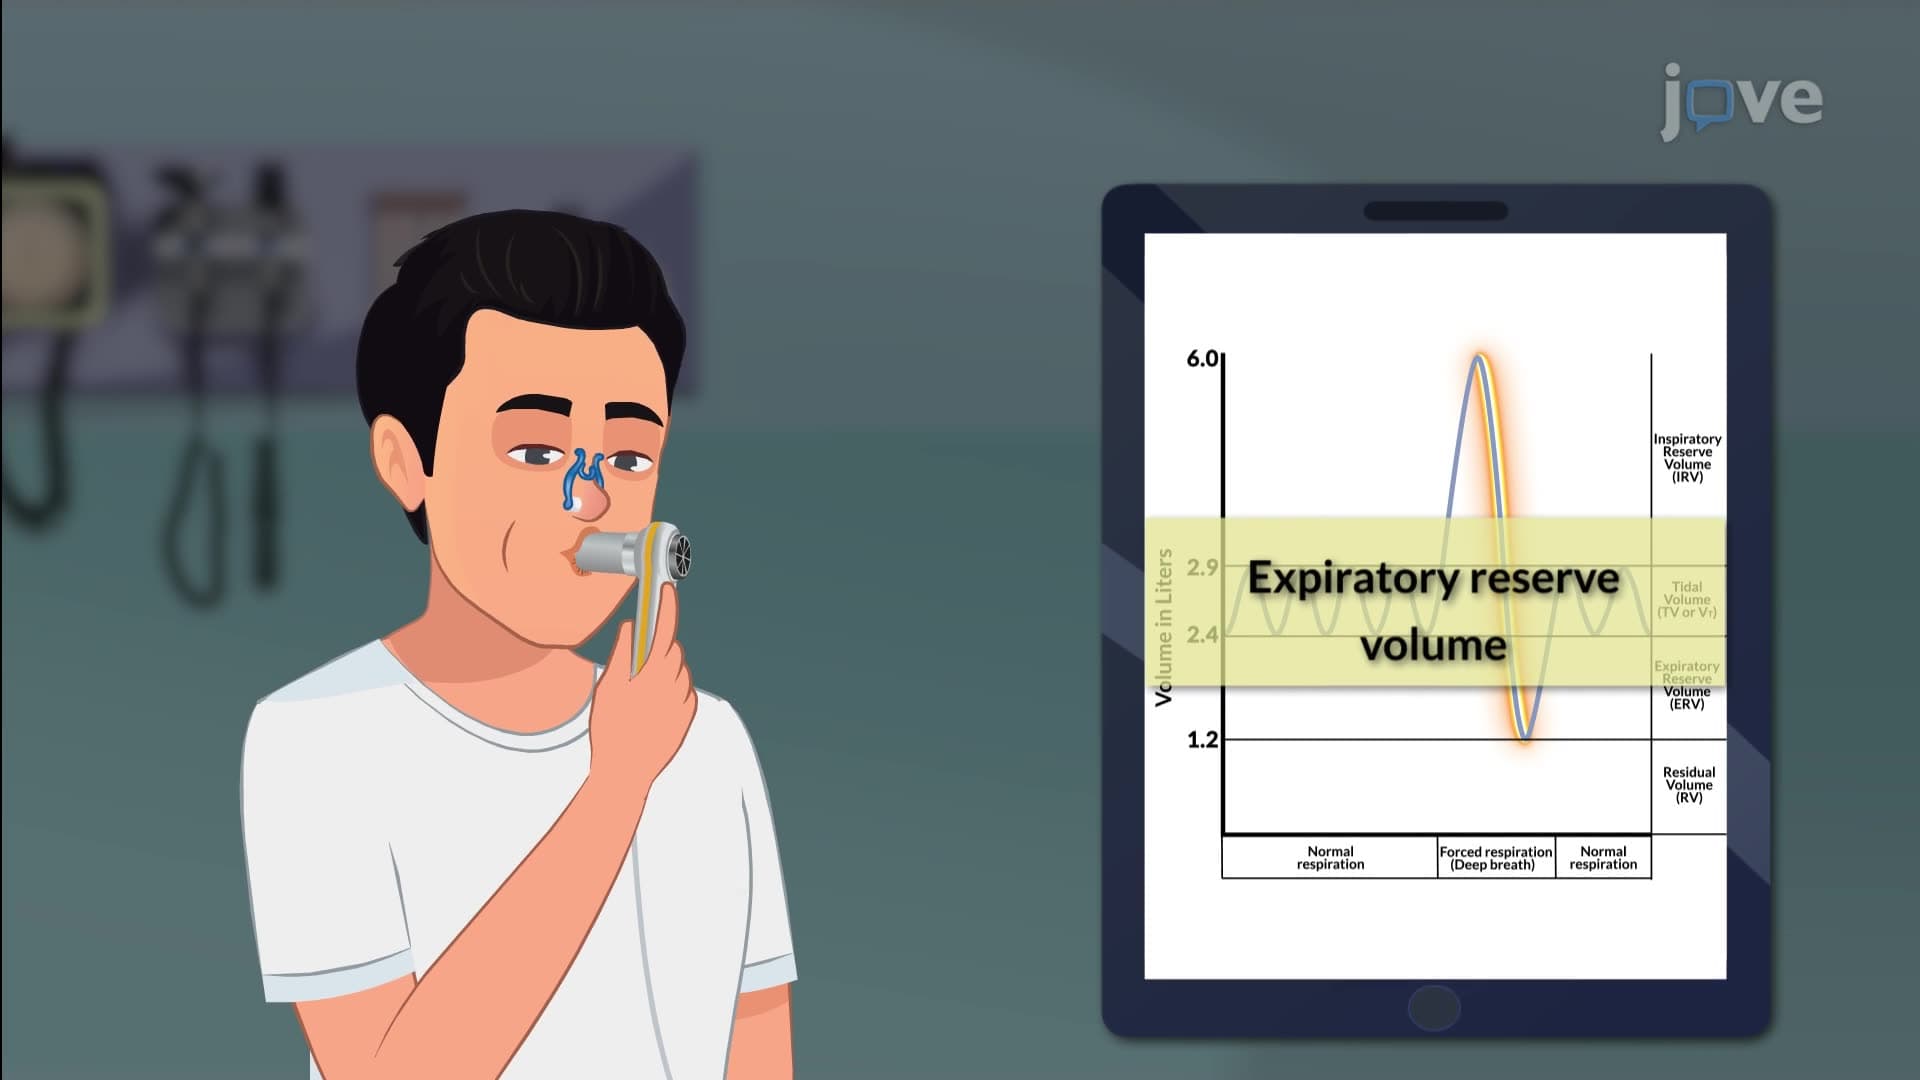 01:15
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:27
Regulation of Stroke Volume
Preload refers to the degree of stretch on the heart before it contracts. It's analogous to the stretching of a rubber band; the more it's stretched, the more forcefully it snaps back. This concept is encapsulated in the Frank-Starling law of the...
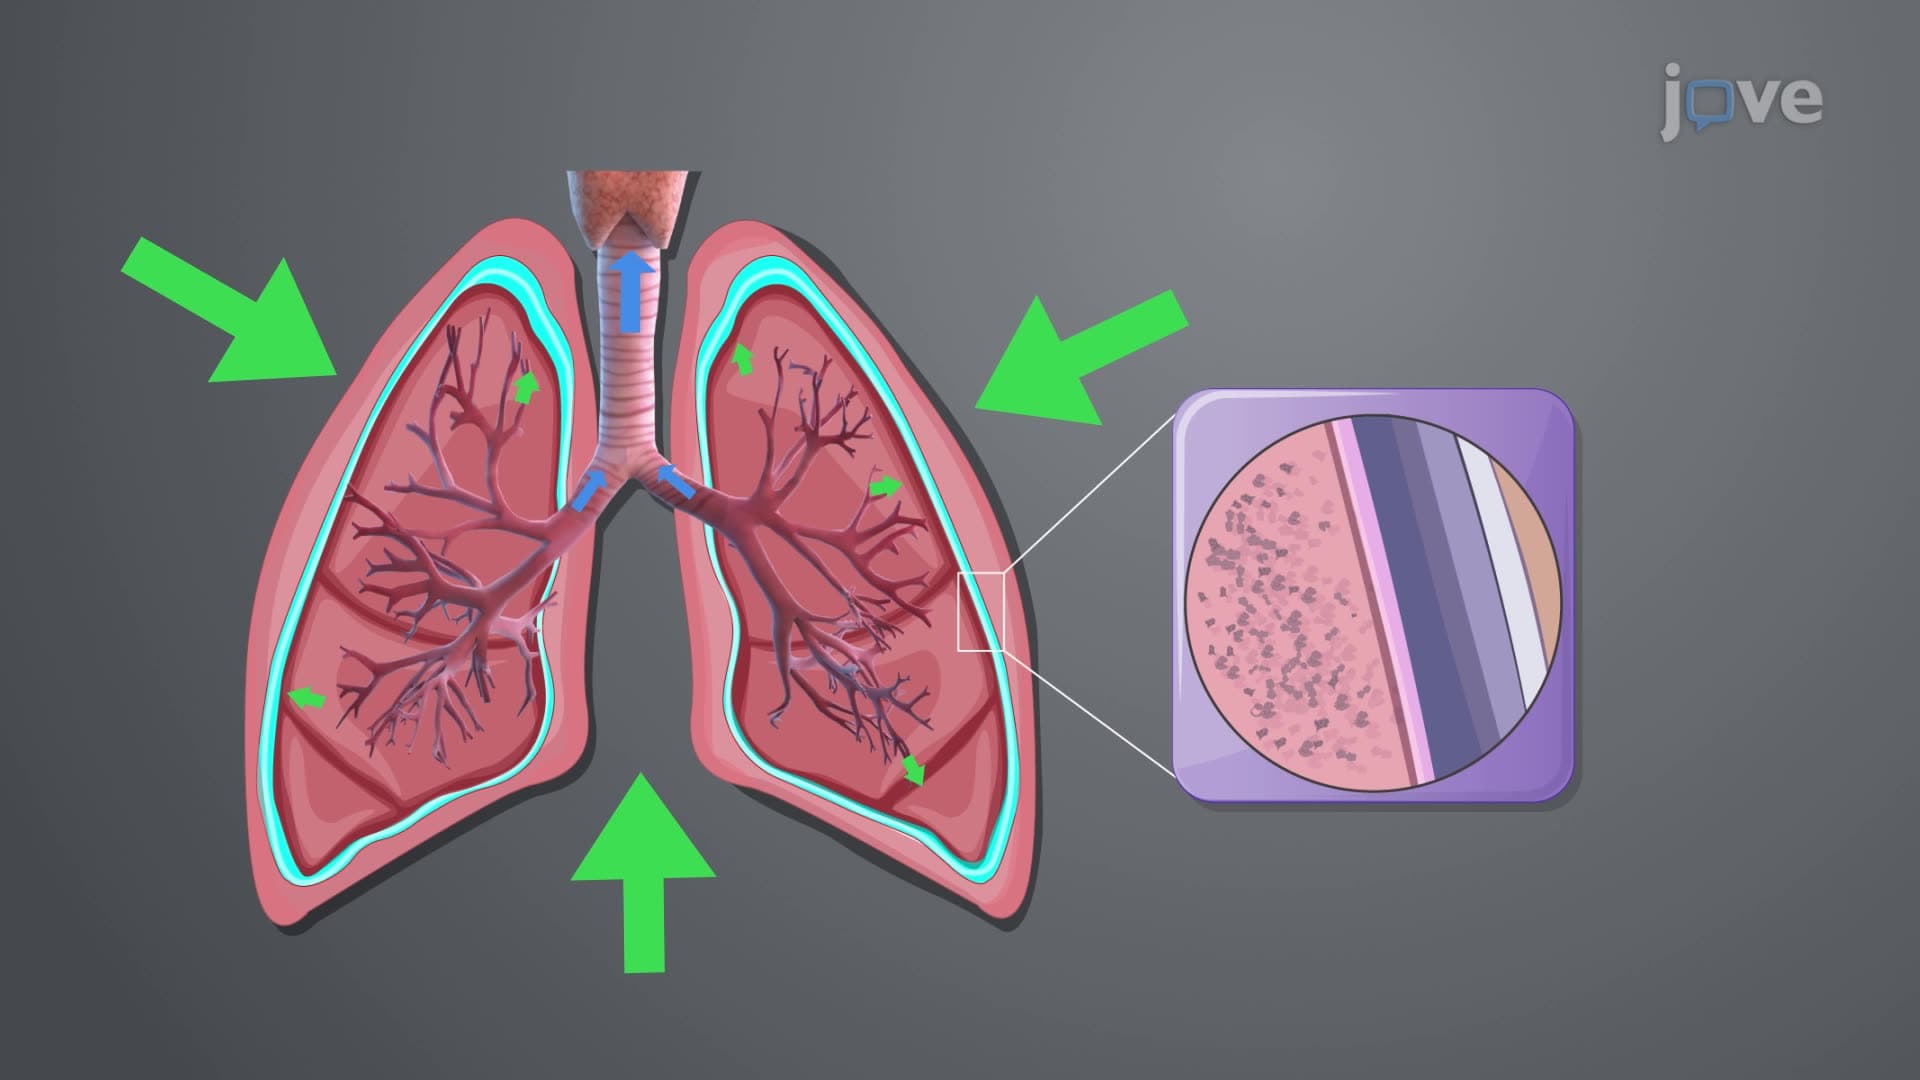 01:24
Pressure Relationships in Thoracic Cavity
Breathing Mechanisms
Both intra-alveolar and intrapleural pressures rely on specific lung properties. The ability to breathe—allowing air to enter the lungs during...
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...