Related Experiment Video
Updated: Aug 9, 2025


Simultaneous Laryngopharyngeal and Conventional Esophageal pH Monitoring
Published on: December 14, 2020
Role of Laryngopharyngeal Reflux Changes in Children with Adenoid Hypertrophy: A Randomized Controlled Prospective
Yu Zhou1, Ruixia Ma2, Jiangbo Luo3
1Department of Otorhinolaryngology Head and Neck Surgery, General Hospital of Ningxia Medical University, Yinchuan, Ningxia 750001, China.

Insights
Laryngopharyngeal reflux (LPR) is linked to adenoid hypertrophy (AH) in children. Salivary pepsin shows a correlation with AH severity, but reflux symptom index and reflux finding score have low sensitivity for diagnosing LPR in this population.
Area of Science:
- Otolaryngology
- Pediatric Gastroenterology
- Reflux Disease
Background:
- Adenoid hypertrophy (AH) is common in children and can be associated with various symptoms.
- Laryngopharyngeal reflux (LPR) is a condition where stomach acid travels up to the throat, potentially causing irritation and other issues.
- The relationship between LPR and AH in pediatric populations requires further investigation.
Purpose of the Study:
- To assess changes in laryngopharyngeal reflux (LPR) in children with adenoid hypertrophy (AH).
- To evaluate the diagnostic accuracy of the reflux symptom index (RSI) and reflux finding score (RFS) in identifying LPR in children with AH.
- To determine the correlation between salivary pepsin levels and the severity of AH.
Main Methods:
- A prospective, randomized, controlled study was conducted.
- Participants included children diagnosed with adenoid hypertrophy.
- Laryngopharyngeal reflux was assessed using RSI and RFS scores, and salivary pepsin concentration was measured.
Main Results:
- Salivary pepsin was detected in 69.77% of samples and positively correlated with AH grade (r=0.576, P<0.01).
- The sensitivity and specificity of RSI and RFS for diagnosing LPR were low (5.77% and 35.03% for RSI; 91.74% and 55.89% for RFS).
- Significant differences in acid reflux episodes were observed between LPR-positive and LPR-negative groups.
Conclusions:
- Laryngopharyngeal reflux plays a role in the progression of adenoid hypertrophy in children.
- The low sensitivity of RSI and RFS makes them unsuitable for diagnosing LPR in children with AH.
- Further research is needed to establish effective diagnostic methods for LPR in this pediatric population.
Objectives:
This prospective randomized controlled analysis aimed to assess the changes in laryngopharyngeal reflux (LPR) in children with adenoid hypertrophy (AH). Study design: a prospective, randomized, and controlled analysis.
Methods:
The reflux symptom index (RSI) and the reflux finding score (RFS) scores were used to evaluate the laryngopharyngeal reflux changes in children diagnosed with adenoid hypertrophy. The pepsin concentration in salivary samples was examined, and the positive pepsin was used to assess the sensitivity and specificity of RSI, RFS, and RSI combined with RFS in forecasting LPR.
Results:
In 43 children with AH, the sensitivity of the RSI and RFS scale (used alone or in combination) in diagnosing pharyngeal reflux in children with adenoid hypertrophy was lower. Pepsin expression was identified in 43 items of salivary samples, with a total positive rate of 69.77%, most of which were optimistic. The expression level of pepsin was positively correlated with the grade of adenoid hypertrophy (r = 0.576, P < 0.01). Based on the positive rate of pepsin, we found that the sensitivity and specificity of RSI and RFS were 5.77%, 35.03%, and 91.74%, 55.89%. Moreover, there was a noticeable distinction in the number of acid reflux episodes between the LPR-positive and LPR-negative groups.
Conclusion:
There is a special connection between LPR change and children's AH. LPR exerts a crucial role in the progression of children's AH. Because of the low sensitivity of RSI and RFS, it is not suitable for LPR children to choose AH.
More Related Videos


Related Concept Videos
 01:23
Chronic Pharyngitis
Etiology
It often arises from persistent viral or bacterial infections affecting sinuses and tonsils.
Additional contributing factors include inadequate dental hygiene, mouth breathing, recurring tonsillitis, allergic rhinitis, laryngopharyngeal reflux, and exposure to smoke, chemicals, and other environmental pollutants. Allergic reactions to pollen, mold, and pet dander, chronic cough, excessive voice usage,...
 01:29
Anatomy of Respiratory System I: Upper Respiratory Tract
Nose and nasal cavity
The nose and nasal cavity represent the main external openings of the respiratory tract....
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...
 01:20
Pharynx
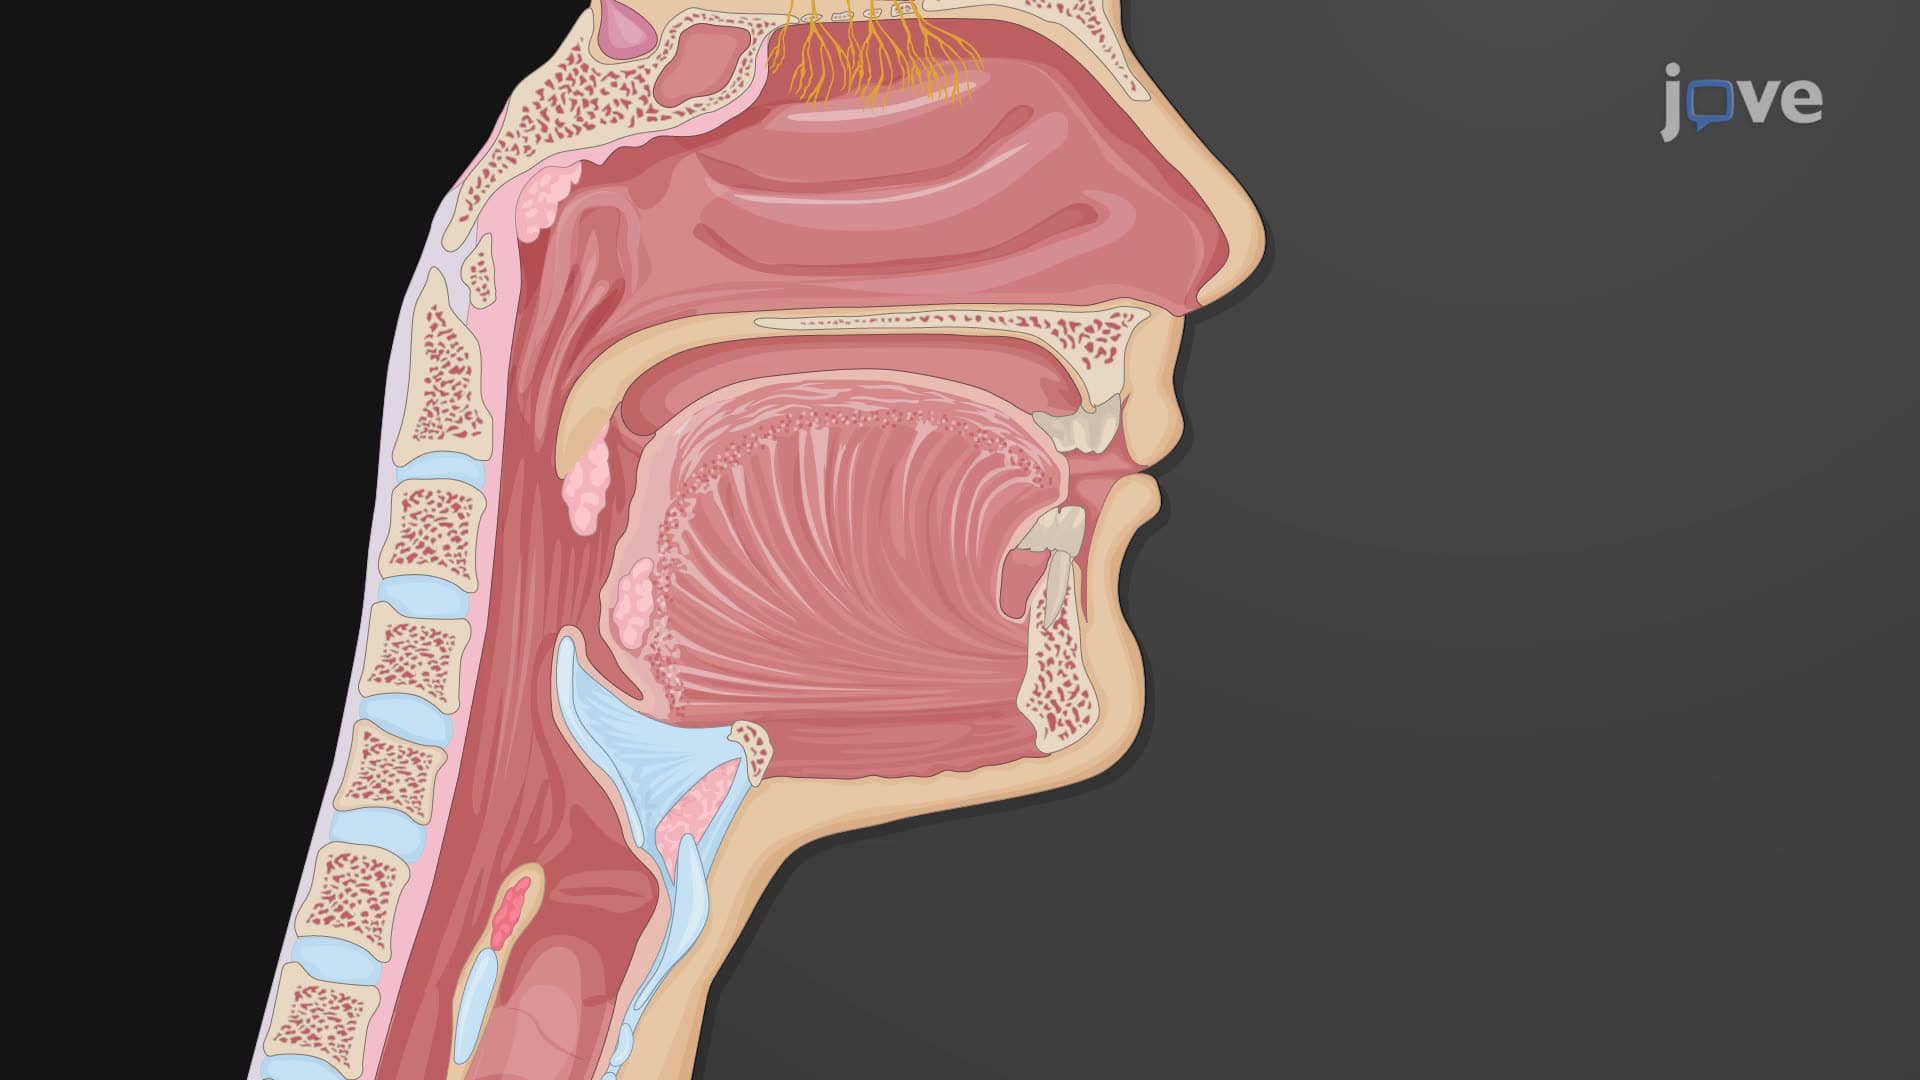
Nasopharynx
The nasopharynx, bordered by the conchae of the nasal cavity, serves exclusively as an air conduit. In its superior region, the pharyngeal tonsils or adenoids are located. These tonsils are clusters of lymphoid reticular tissue akin to a lymph node. The precise...
 01:21
Larynx
Anatomy of the Larynx
The larynx consists of various components, including cartilage, muscles, and vocal cords. Its structure includes three large unpaired cartilages—the thyroid, cricoid, and epiglottis—and three smaller paired cartilages—the arytenoids,...
 01:23
Upper Respiratory Drugs: Antitussives, Expectorants, and Mucolytics
Antitussives include codeine, dextromethorphan (Robitussin), and benzonatate (Tessalon). Codeine and dextromethorphan exert their effects centrally by suppressing the cough reflex center in the medulla. Benzonatate operates peripherally within the respiratory tract by...