Related Experiment Video
Updated: Aug 9, 2025


A Mouse Model of Direct Anastomosis via the Prespinal Route for Crossing Nerve Transfer Surgery
Published on: October 19, 2021
Posterior division of ipsilateral C7 transfer to C5 for shoulder abduction limitation
Xinying Huang1,2,3,4, Zongqi You1,2,3, Yaoxian Xiang1,2,3
1Department of Hand Surgery, Huashan Hospital, Fudan University, Shanghai, China.

Background:
Reparation of C5 by proximal selective ipsilateral C7 transfer has been reported for the treatment of neurogenic shoulder abduction limitation as an alternative to the reparation of the suprascapular nerve (SSN) and the axillary nerve (AXN) by distal nerve transfers. However, there is a lack of evidence to support either strategy leading to better outcomes based on long-term follow-up.
Objective:
The purpose of the study was to investigate the safety and long-term outcomes of the posterior division of ipsilateral C7 (PDIC7) transfer to C5 in treating neurogenic shoulder abduction limitation.
Methods:
A total of 27 cases with limited shoulder abduction caused by C5 injury (24 cases of trauma, 2 cases of neuritis, and 1 case of iatrogenic injury) underwent PDIC7 transfer to the C5 root. A total of 12 cases (11 cases of trauma and 1 case of neuritis) of C5 injury underwent spinal accessory nerve (SAN) transfer to SSN plus the triceps muscular branch of the radial nerve (TMBRN) transfer to AXN. The patients were followed up for at least 12 months for muscle strength and shoulder abduction range of motion (ROM).
Results:
In cases that underwent PDIC7 transfer, the average shoulder abduction was 105.9° at the 12-month follow-up. In total, 26 of 27 patients recovered at least M3 (13 reached M4) (Medical Research Council Grading) of the deltoid. In cases that underwent SAN transfer to SSN plus TMBRN to AXN, the average shoulder abduction was 84.6° at the 12-month follow-up. In total, 11 of 12 patients recovered at least M3 (4 reached M4) of the deltoid.
Conclusion:
Posterior division of ipsilateral C7 transfer is a one-stage, safe, and effective surgical procedure for patients with neurogenic shoulder abduction limitation.

Related Concept Videos
 01:23
Muscles of the Shoulder
Anterior Thoracic Muscles
The anterior thoracic muscles include the serratus anterior, subclavius, and...
 01:31
Muscles that Move the Arm
The pectoralis major has two origins. Its clavicular head originates on the medial half of the clavicle. In contrast, the sternocostal head originates on the costal cartilages of ribs 1-6, the sternum, and the aponeurosis of the external oblique of the...
 01:19
Muscles that Move the Head
The bilateral sternocleidomastoid, or SCM, and the suprahyoid and infrahyoid muscles are significant head flexors. The SCM muscles originate at the sternum and clavicle and attach to the mastoid process of the temporal bone. The SCM contracts bilaterally to bend the head forward, whereas...
 01:22
Spinal Nerves: Plexus I
The Cervical Plexus
The cervical plexus, formed by the anterior rami of the first four...
 01:22
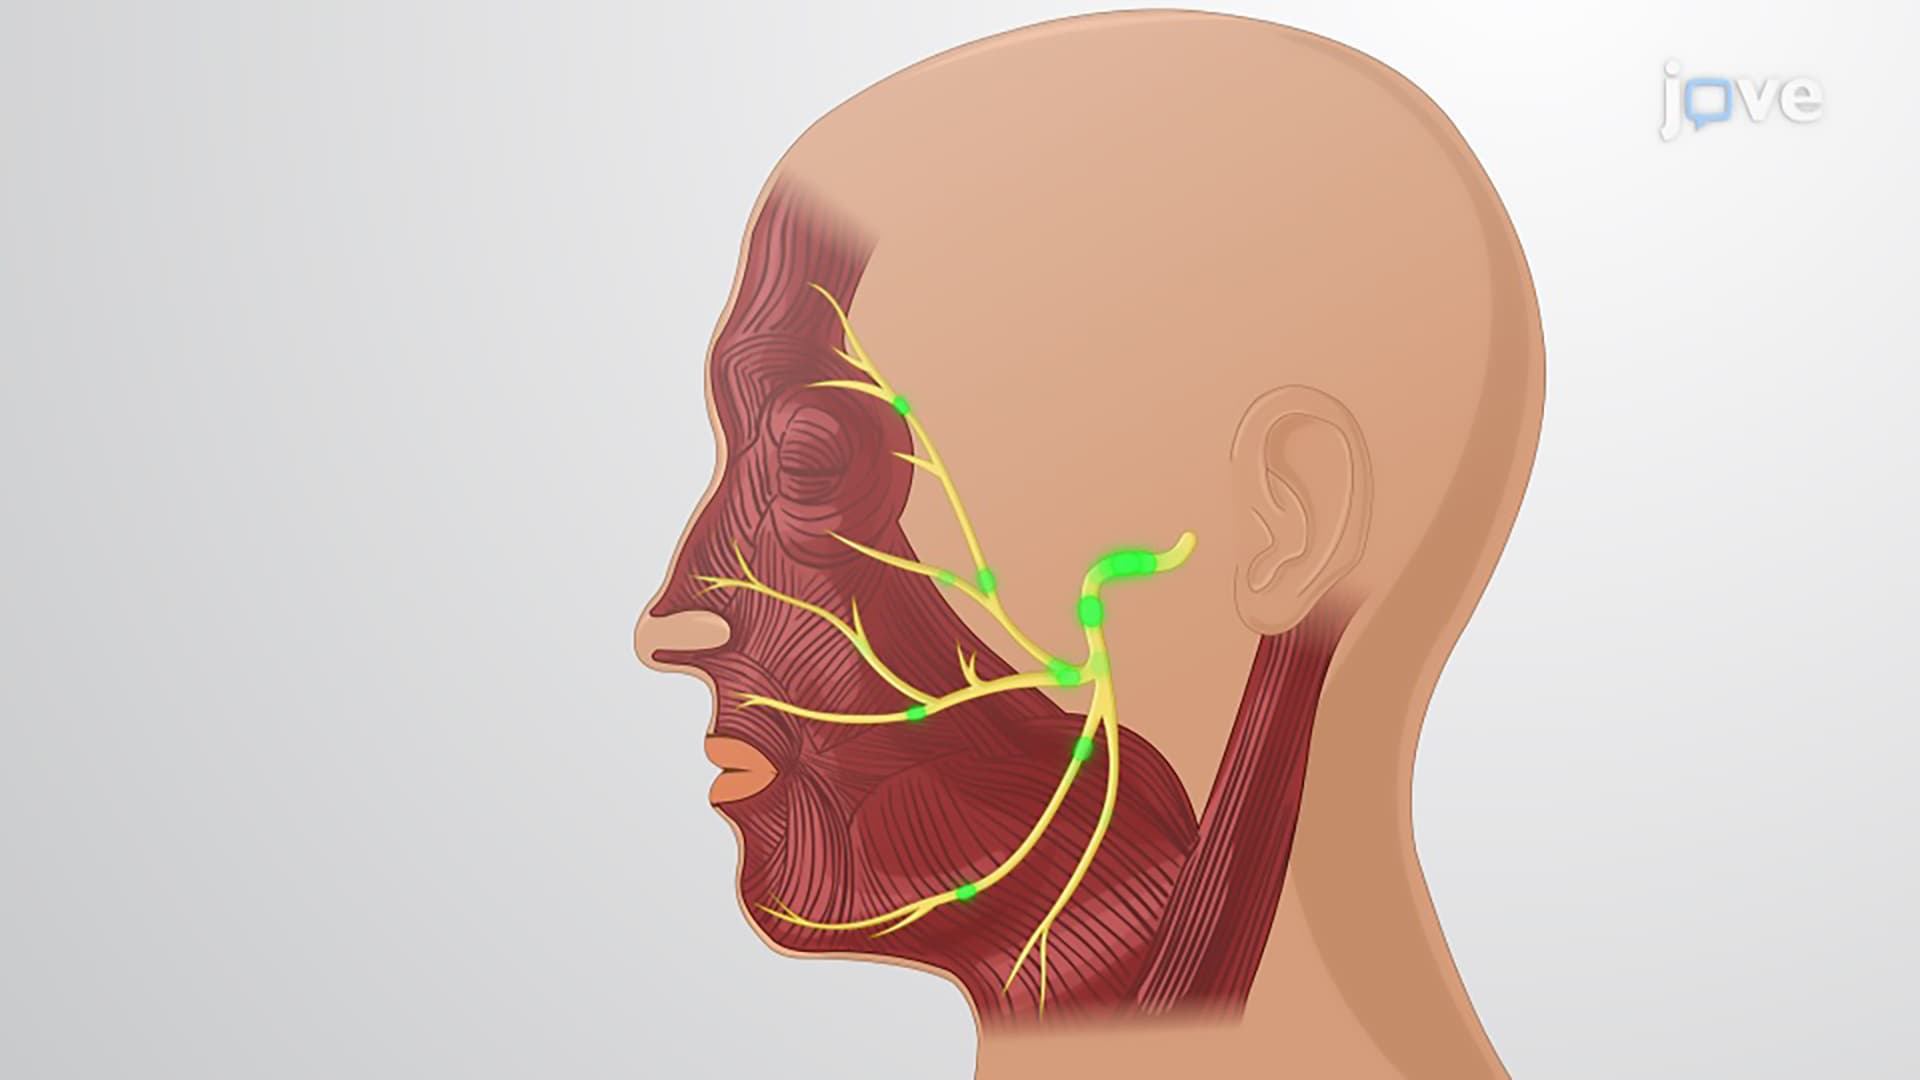
Cranial Nerves: Types Part II
Facial Nerve (Cranial Nerve VII)
Cranial nerve VII, or the facial nerve,...
 01:17
Cerebellum: Anatomical Regions
Cerebellar Structure
Externally, the cerebellum features a highly convoluted surface with numerous folia (narrow ridges) separated by shallow sulci (grooves). The cerebellum is divided into two hemispheres by a thin median structure known as the vermis. The...