Related Experiment Video
Updated: Aug 8, 2025
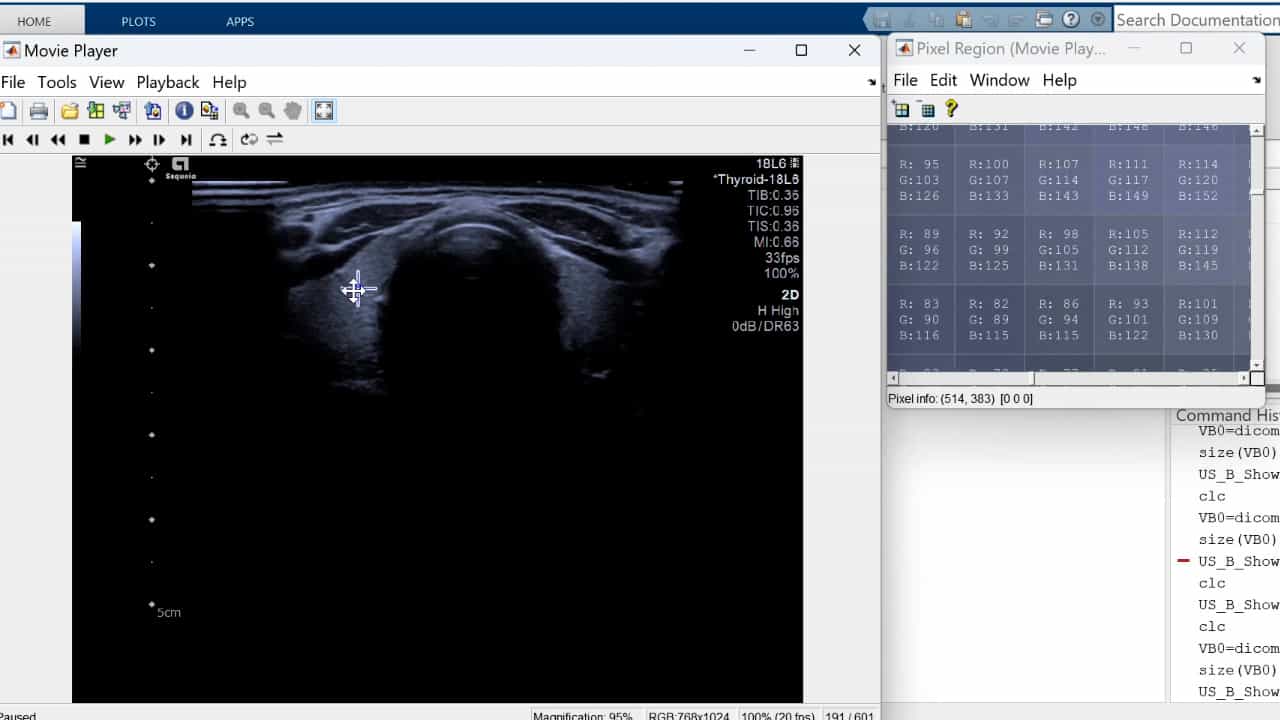

Author Spotlight: Integrating Ultrasound Imaging with Biochemical Markers for Thyroid Disease Diagnosis
Published on: February 9, 2024
Hyperthyroidism: aetiology, pathogenesis, diagnosis, management, complications, and prognosis
Wilmar M Wiersinga1, Kris G Poppe2, Grigoris Effraimidis3,4
1Department of Endocrinology and Metabolism, Academic Medical Center, University of Amsterdam, Netherlands.

Abstract:
Hyperthyroidism is a common condition with a global prevalence of 0·2-1·3%. When clinical suspicion of hyperthyroidism arises, it should be confirmed by biochemical tests (eg, low TSH, high free thyroxine [FT4], or high free tri-iodothyonine [FT3]). If hyperthyroidism is confirmed by biochemical tests, a nosological diagnosis should be done to find out which disease is causing the hyperthyroidism. Helpful tools are TSH-receptor antibodies, thyroid peroxidase antibodies, thyroid ultrasonography, and scintigraphy. Hyperthyroidism is mostly caused by Graves' hyperthyroidism (70%) or toxic nodular goitre (16%). Hyperthyroidism can also be caused by subacute granulomatous thyroiditis (3%) and drugs (9%) such as amiodarone, tyrosine kinase inhibitors, and immune checkpoint inhibitors. Disease-specific recommendations are given. Currently, Graves' hyperthyroidism is preferably treated with antithyroid drugs. However, recurrence of hyperthyroidism after a 12-18 month course of antithyroid drugs occurs in approximately 50% of patients. Being younger than 40 years, having FT4 concentrations that are 40 pmol/L or higher, having TSH-binding inhibitory immunoglobulins that are higher than 6 U/L, and having a goitre size that is equivalent to or larger than WHO grade 2 before the start of treatment with antithyroid drugs increase risk of recurrence. Long-term treatment with antithyroid drugs (ie, 5-10 years of treatment) is feasible and associated with fewer recurrences (15%) than short-term treatment (ie, 12-18 months of treatment). Toxic nodular goitre is mostly treated with radioiodine (131I) or thyroidectomy and is rarely treated with radiofrequency ablation. Destructive thyrotoxicosis is usually mild and transient, requiring steroids only in severe cases. Specific attention is given to patients with hyperthyroidism who are pregnant, have COVID-19, or have other complications (eg, atrial fibrillation, thyrotoxic periodic paralysis, and thyroid storm). Hyperthyroidism is associated with increased mortality. Prognosis might be improved by rapid and sustained control of hyperthyroidism. Innovative new treatments are expected for Graves' disease, by targeting B cells or TSH receptors.


Related Concept Videos
 01:23
The Thyroid Gland
The follicles have a central cavity lined by simple cuboidal to squamous epithelial cells called follicular cells. These cells produce the glycoprotein...
 01:20
Synthesis and Regulation of Thyroid Hormones
Upon reaching the thyroid gland, TSH stimulates the follicular cells' active uptake of iodide ions from the blood. The ions diffuse to the apical surface of the cells and are oxidized to iodine. The...
 01:18
Functions of Thyroid Hormones
TH is indispensable for the normal development and maturation of the skeletal, muscular, and nervous systems during fetal and childhood growth. It facilitates bone mineral turnover and regulates protein synthesis in developing tissues, contributing significantly to overall growth and...
 01:29
Hypertension II: Pathophysiology
 01:20
Asthma: Pathogenesis and Management
Asthma is classified as allergic and non-allergic. Allergens such as dust mites, pollen, and pet dander trigger allergic asthma, while factors like cold air, intense emotions, or exercise can induce non-allergic asthma.
 01:15
Diabetes: Management and Pharmacotherapy
Insulin remains the cornerstone of treatment for most patients with type 1 and many...