Related Experiment Video
Updated: Aug 8, 2025


ADSC-sheet Transplantation to Prevent Stricture after Extended Esophageal Endoscopic Submucosal Dissection
Published on: February 10, 2017
Combined treatment of refractory benign stricture after esophageal endoscopic mucosal dissection: A case report
Wen-Feng Pu1, Tao Zhang2, Zong-Han Du2
1Department of Gastroenterology, Nanchong Central Hospital, The Second Affiliated Hospital of North Sichuan Medical College, Nanchong 637000, Sichuan Province, China. 1047951869@qq.com.

Background:
Endoscopic submucosal dissection (ESD) post-procedure stricture is a relatively common long-term complication following ESD treatment. A range of approaches has been implemented for the treatment of post-procedural stricture using endoscopic techniques such as endoscopic dilation, self-expandable metallic stent insertion, local steroid injection in the esophagus, oral steroid administration, radial incision and cutting (RIC). The actual efficacy of these different therapeutic options is highly variable, and uniform international standards for the prevention or treatment of stricture.
Case Summary:
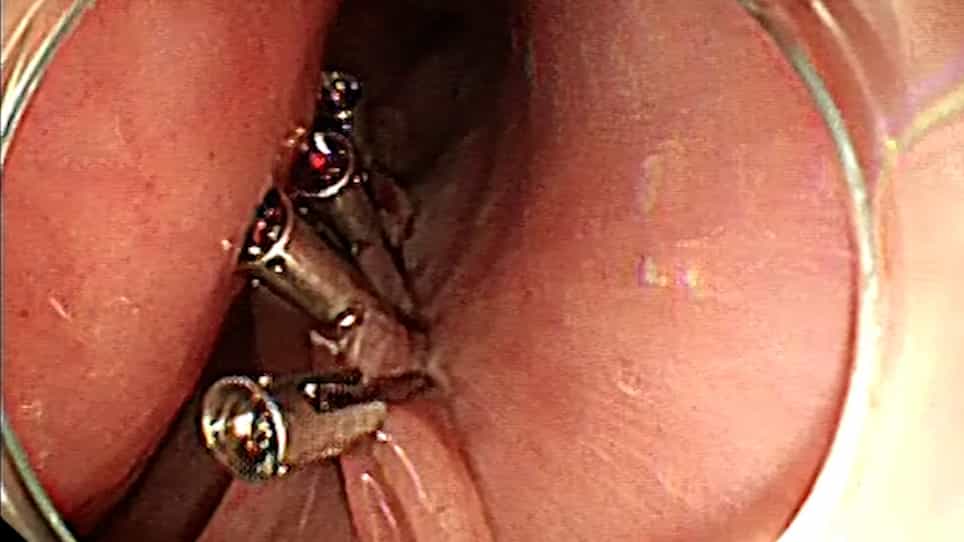
In this report, we describe the case of a 51-year-old male diagnosed with early esophageal cancer. To protect against esophageal stricture, the patient was administered oral steroids and underwent self-expandable metallic stent insertion for 45 d. Despite these interventions, stricture was detected at the lower edge of the stent following its removal. The patient remained refractory to multiple rounds of endoscopic bougie dilation treatment, and thus suffered from complex refractory benign esophageal stricture. As such, RIC combined with bougie dilation and steroid injection was employed to treat this patient more effectively, ultimately achieving satisfactory therapeutic efficacy.
Conclusion:
Combination of RIC, dilation, and steroid injection can be safely and effectively implemented to treat cases of post-ESD refractory esophageal stricture.
More Related Videos

Related Concept Videos
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure...
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...
 01:26
Endoscopic Procedures V: ERCP
Patient...