Related Experiment Video
Updated: Aug 8, 2025
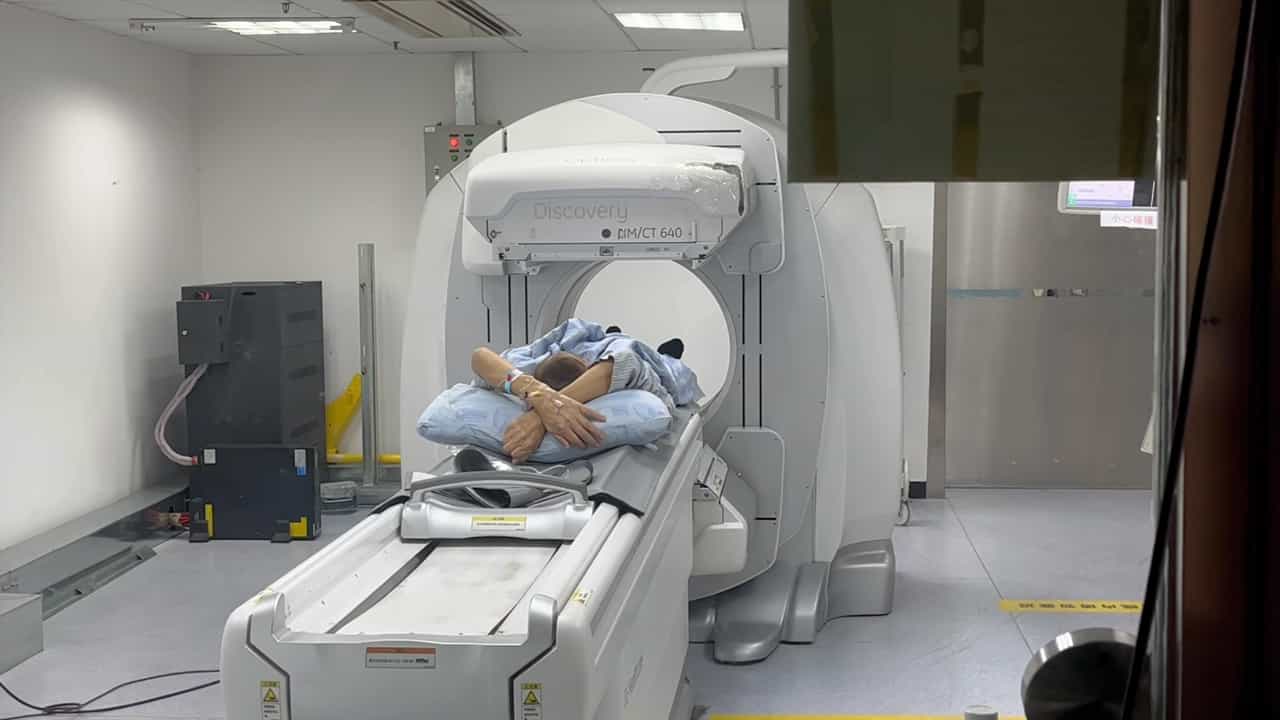
Y-90 Radioembolization and PD-1 Inhibitor as Neoadjuvant Treatment in Hepatocellular Carcinoma
Published on: May 24, 2024
SPECT and CT misregistration reduction in [99mTc]Tc-MAA SPECT/CT for precision liver radioembolization treatment
Zhonglin Lu1,2, Gefei Chen1, Han Jiang1
1Biomedical Imaging Laboratory (BIG), Department of Electrical and Computer Engineering, Faculty of Science and Technology, University of Macau, Taipa, Macau SAR, China.

Purpose:
Respiration and body movement induce misregistration between static [99mTc]Tc-MAA SPECT and CT, causing lung shunting fraction (LSF) and tumor-to-normal liver ratio (TNR) errors for 90Y radioembolization planning. We aim to alleviate the misregistration between [99mTc]Tc-MAA SPECT and CT using two registration schemes on simulation and clinical data.
Methods:
In the simulation study, 70 XCAT phantoms were modeled. The SIMIND Monte Carlo program and OS-EM algorithm were used for projection generation and reconstruction, respectively. Low-dose CT (LDCT) at end-inspiration was simulated for attenuation correction (AC), lungs and liver segmentation, while contrast-enhanced CT (CECT) was simulated for tumor and perfused liver segmentation. In the clinical study, 16 patient data including [99mTc]Tc-MAA SPECT/LDCT and CECT with observed SPECT and CT mismatch were analyzed. Two liver-based registration schemes were studied: SPECT registered to LDCT/CECT and vice versa. Mean count density (MCD) of different volumes-of-interest (VOIs), normalized mutual information (NMI), LSF, TNR, and maximum injected activity (MIA) based on the partition model before and after registration were compared. Wilcoxon signed-rank test was performed.
Results:
In the simulation study, compared to before registration, registrations significantly reduced estimation errors of MCD of all VOIs, LSF (Scheme 1: - 100.28%, Scheme 2: - 101.59%), and TNR (Scheme 1: - 7.00%, Scheme 2: - 5.67%), as well as MIA (Scheme 1: - 3.22%, Scheme 2: - 2.40%). In the clinical study, Scheme 1 reduced 33.68% LSF and increased 14.75% TNR, while Scheme 2 reduced 38.88% LSF and increased 6.28% TNR compared to before registration. One patient may change from 90Y radioembolization untreatable to treatable and other patients may change the MIA up to 25% after registration. NMI between SPECT and CT was significantly increased after registrations in both studies.
Conclusion:
Registration between static [99mTc]Tc-MAA SPECT and corresponding CTs is feasible to reduce their spatial mismatch and improve dosimetric estimation. The improvement of LSF is larger than TNR. Our method can potentially improve patient selection and personalized treatment planning for liver radioembolization.
More Related Videos
 08:54
Treatment of Liver Metastases Using an Internal Target Volume Method for Stereotactic Body Radiotherapy
Published on: May 8, 2018
 09:49
Dual-phase Cone-beam Computed Tomography to See, Reach, and Treat Hepatocellular Carcinoma during Drug-eluting Beads Transarterial Chemo-embolization
Published on: December 2, 2013
