Related Experiment Video
Updated: Aug 7, 2025


Delivery of In Vivo Acute Intermittent Hypoxia in Neonatal Rodents to Prime Subventricular Zone-derived Neural Progenitor Cell Cultures
Published on: November 2, 2015
Mild inflammation impairs acute intermittent hypoxia-induced phrenic long-term facilitation by a spinal
Alexandria B Marciante1, Gordon S Mitchell1
1Breathing Research and Therapeutics Center, Department of Physical Therapy & McKnight Brain Institute, University of Florida, Gainesville, Florida, United States.

Abstract:
Inflammation undermines neuroplasticity, including serotonin-dependent phrenic long-term facilitation (pLTF) following moderate acute intermittent hypoxia (mAIH: 3, 5-min episodes, arterial Po2: 40-50 mmHg; 5-min intervals). Mild inflammation elicited by a low dose of the TLR-4 receptor agonist, lipopolysaccharide (LPS; 100 µg/kg, ip), abolishes mAIH-induced pLTF by unknown mechanisms. In the central nervous system, neuroinflammation primes glia, triggering ATP release and extracellular adenosine accumulation. As spinal adenosine 2 A (A2A) receptor activation impairs mAIH-induced pLTF, we hypothesized that spinal adenosine accumulation and A2A receptor activation are necessary in the mechanism whereby LPS impairs pLTF. We report that 24 h after LPS injection in adult male Sprague Dawley rats: 1) adenosine levels increase in ventral spinal segments containing the phrenic motor nucleus (C3-C5; P = 0.010; n = 7/group) and 2) cervical spinal A2A receptor inhibition (MSX-3, 10 µM, 12 µL intrathecal) rescues mAIH-induced pLTF. In LPS vehicle-treated rats (saline, ip), MSX-3 enhanced pLTF versus controls (LPS: 110 ± 16% baseline; controls: 53 ± 6%; P = 0.002; n = 6/group). In LPS-treated rats, pLTF was abolished as expected (4 ± 6% baseline; n = 6), but intrathecal MSX-3 restored pLTF to levels equivalent to MSX-3-treated control rats (120 ± 14% baseline; P < 0.001; n = 6; vs. LPS controls with MSX-3: P = 0.539). Thus, inflammation abolishes mAIH-induced pLTF by a mechanism that requires increased spinal adenosine levels and A2A receptor activation. As repetitive mAIH is emerging as a treatment to improve breathing and nonrespiratory movements in people with spinal cord injury or ALS, A2A inhibition may offset undermining effects of neuroinflammation associated with these neuromuscular disorders.NEW & NOTEWORTHY Mild inflammation undermines motor plasticity elicited by mAIH. In a model of mAIH-induced respiratory motor plasticity (phrenic long-term facilitation; pLTF), we report that inflammation induced by low-dose lipopolysaccharide undermines mAIH-induced pLTF by a mechanism requiring increased cervical spinal adenosine and adenosine 2 A receptor activation. This finding advances the understanding of mechanisms impairing neuroplasticity, potentially undermining the ability to compensate for the onset of lung/neural injury or to harness mAIH as a therapeutic modality.
Insights
Mild inflammation impairs respiratory motor plasticity (phrenic long-term facilitation) by increasing spinal adenosine and activating adenosine 2A receptors. Blocking these receptors restores plasticity, offering potential therapeutic strategies for neuroinflammatory conditions.
Area of Science:
- Neuroscience
- Respiratory Physiology
- Inflammation Research
Background:
- Neuroinflammation disrupts neuroplasticity, affecting motor control.
- Moderate acute intermittent hypoxia (mAIH) normally enhances phrenic long-term facilitation (pLTF), a measure of respiratory motor plasticity.
- Mild inflammation, induced by lipopolysaccharide (LPS), abolishes mAIH-induced pLTF through unknown mechanisms.
Purpose of the Study:
- To investigate if spinal adenosine accumulation and adenosine 2A (A2A) receptor activation mediate the impairing effects of LPS on mAIH-induced pLTF.
- To test the hypothesis that blocking spinal A2A receptors can restore mAIH-induced pLTF in the presence of inflammation.
Main Methods:
- Adult male Sprague Dawley rats were administered LPS (100 µg/kg, ip) or saline.
- Adenosine levels were measured in cervical spinal cord segments (C3-C5) 24 hours post-injection.
- Intrathecal administration of an A2A receptor inhibitor (MSX-3, 10 µM) was performed before mAIH exposure.
- Phrenic long-term facilitation (pLTF) was assessed following mAIH.
Main Results:
- LPS injection significantly increased adenosine levels in the phrenic motor nucleus-containing spinal segments.
- Inhibition of cervical spinal A2A receptors with MSX-3 restored mAIH-induced pLTF in LPS-treated rats.
- MSX-3 administration alone enhanced pLTF in control (saline-treated) rats, but not in LPS-treated rats, indicating A2A receptor involvement in LPS's effect.
Conclusions:
- Inflammation abolishes mAIH-induced pLTF via a mechanism requiring increased spinal adenosine and subsequent A2A receptor activation.
- Targeting spinal adenosine A2A receptors may counteract the negative effects of neuroinflammation on respiratory motor plasticity.
- This finding is relevant for therapeutic strategies using mAIH in conditions like spinal cord injury and ALS, where neuroinflammation is present.
Related Concept Videos
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:30
Acute Respiratory Failure-III
 01:17
Other Factors Affecting Respiration Centers
However, the ability to hold one's breath voluntarily is not limitless. When the CO2 concentration in the blood reaches a critical...
 01:21
Skeletal Muscle Relaxants: Adverse Effects
Unlike...
 01:23
Physiological Control of Respiration
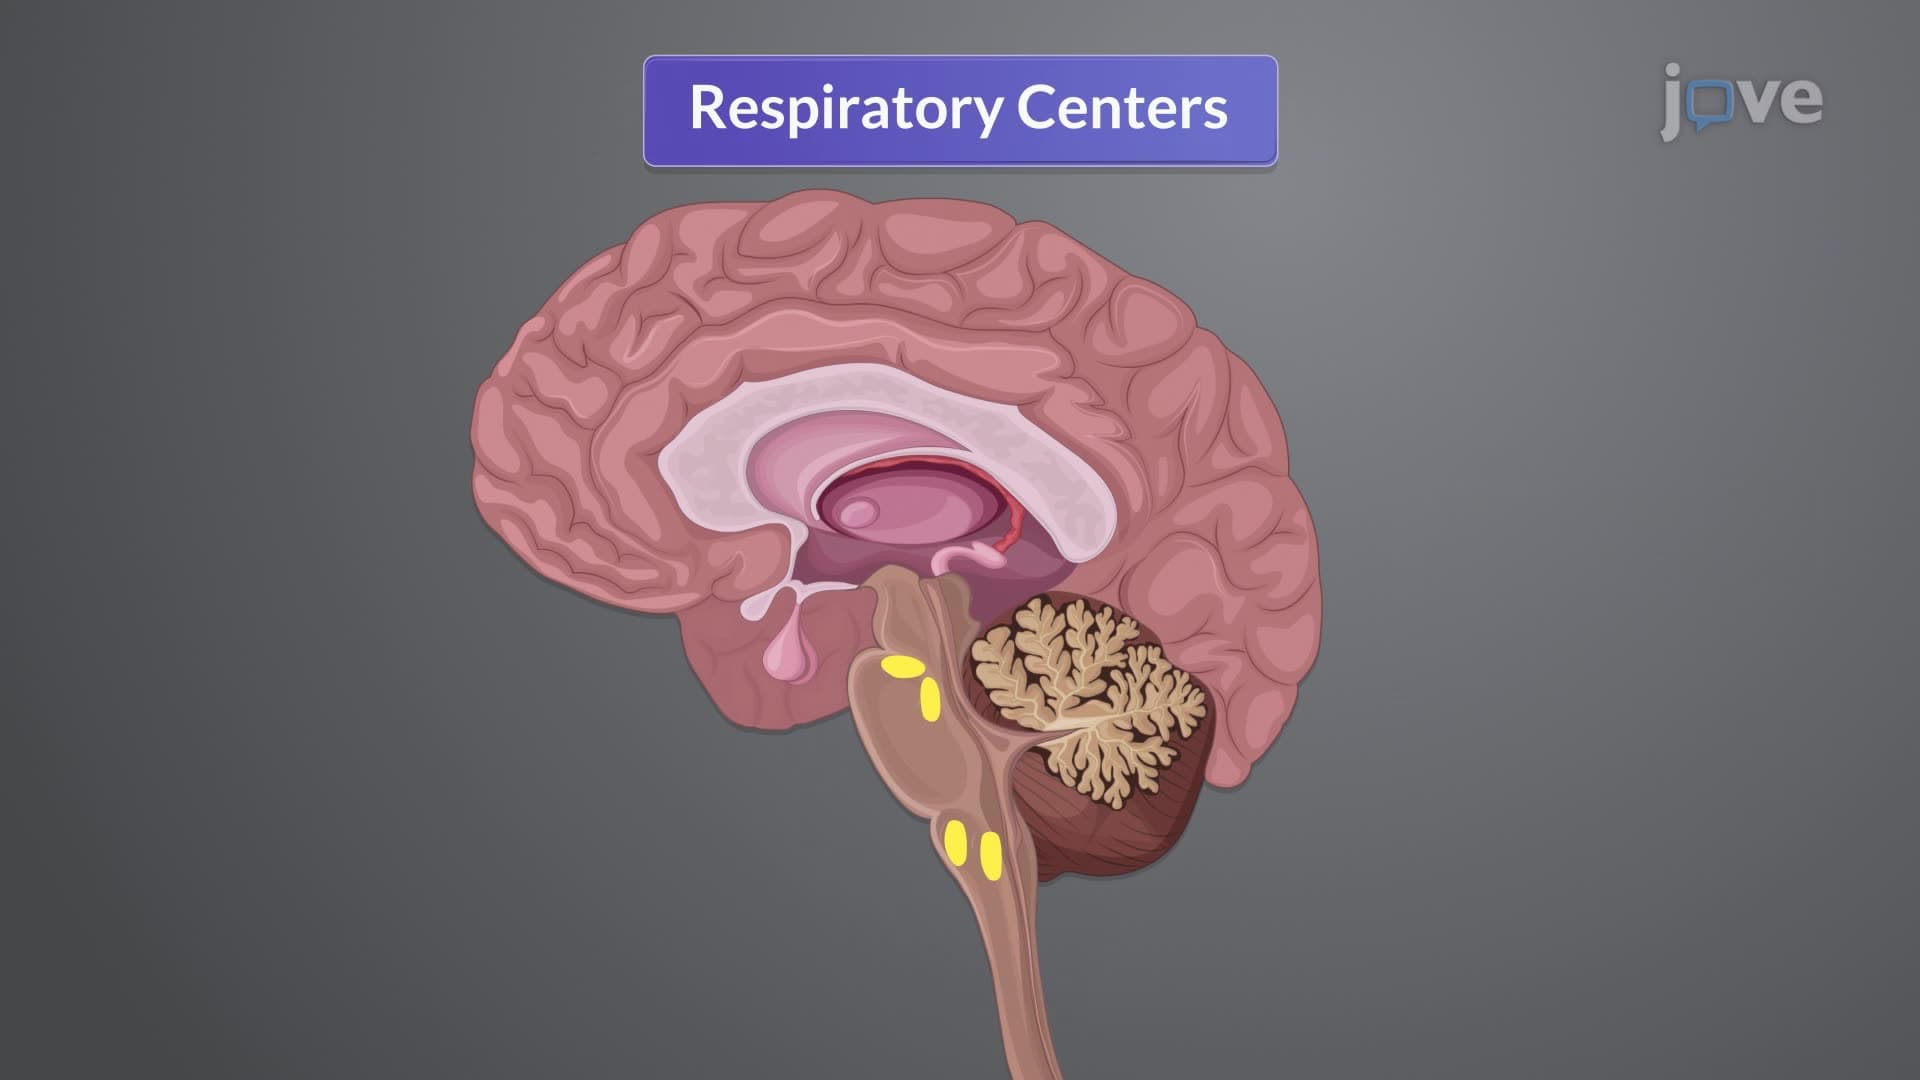
Breathing, a seemingly passive process, is regulated by the respiratory center in the brainstem. This center coordinates the involuntary control of respirations, which means it occurs without conscious effort, ensuring a smooth and uninterrupted pattern.
Regulation of Ventilation
The body maintains ventilation by monitoring levels of carbon dioxide (CO2), oxygen (O2), and hydrogen ion concentration (pH) in the arterial blood. Among these factors, the level of CO2 plays a crucial...
 01:22
Physiology of Respiration II: Neurogenic Control of Respiration
Central Control
The brainstem is the primary site of central control, hosting respiratory centers: