Related Experiment Video
Updated: Aug 7, 2025
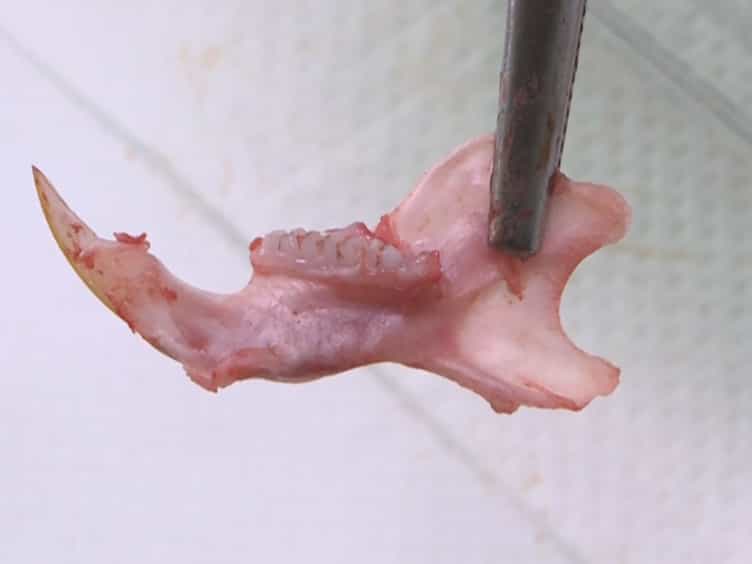
Micro-dissection of Enamel Organ from Mandibular Incisor of Rats Exposed to Environmental Toxicants
Published on: March 29, 2018
Prevalence and associated factors of enamel developmental defects among Nigerian children with perinatal HIV exposure
Nonso Emmanuel Onyia1, Paul Akhigbe2, Esosa Osagie2
1Department of Oral Pathology and Medicine, University of Benin, 302001 Edo State, Nigeria.

Insights
Developmental defects of enamel (DDE) are common in children, with HIV infection being a significant risk factor. This study highlights the prevalence of DDE in HIV-infected and exposed children, emphasizing the need for targeted oral health policies.
Area of Science:
- Pediatric Dentistry
- Infectious Diseases
- Oral Health Epidemiology
Background:
- Developmental defects of enamel (DDE) impact tooth structure and aesthetics.
- Human Immunodeficiency Virus (HIV) infection and perinatal exposure may influence oral health outcomes.
- Understanding DDE prevalence in HIV-affected children is crucial for early intervention.
Purpose of the Study:
- To determine the prevalence and patterns of DDE in HIV-infected (HI), HIV-exposed but uninfected (HEU), and HIV-unexposed and uninfected (HUU) children.
- To identify risk factors associated with DDE in these pediatric groups.
- To compare DDE occurrence between HI, HEU, and HUU children.
Main Methods:
- An analytic cross-sectional study involving 554 school-aged children (4-11 years) in Nigeria.
- Participants were categorized into HI (on antiretroviral therapy), HEU, and HUU groups.
- Data collected via questionnaires, clinical chart review, and dental examinations using the modified DDE Index; CD4+ T-cell counts were also assayed.
Main Results:
- Overall DDE prevalence was 18.59% across all groups.
- The HI group exhibited the highest frequency of DDE-affected teeth (4.36%), followed by HEU (2.73%) and HUU (2.05%).
- Demarcated Opacity (DDE code 1) was the most frequent defect; DDE codes 1, 4, and 6 were significantly associated with HI and HEU groups.
Conclusions:
- DDE is prevalent in school-aged children, with HIV infection identified as a significant risk factor for hypoplasia.
- Controlled HIV infection (with ART) shows associations with oral diseases, reinforcing the need for targeted public health policies.
- Further research is warranted to explore the specific mechanisms linking HIV and DDE.
Abstract:
To evaluate the prevalence and pattern of developmental defects of the enamel (DDE) and their risk factors among children born infected with Human Immunodeficiency Virus (HIV) and those born to HIV-infected mothers compared with their unexposed counterparts (i.e., children born to uninfected mothers). This was an analytic cross-sectional study evaluating the presence and pattern of distribution of DDE in three groups of school-aged children (age, 4-11 years) receiving care and treatment at a Nigerian tertiary hospital, comprising: (1) HIV-infected (HI) on antiretroviral therapy (ART) (n = 184), (2) HIV-exposed but uninfected (HEU) (n = 186) and (3) HIV-unexposed and uninfected (HUU) (n = 184). Data capture forms and questionnaires were used to record the children's medical and dental history based on clinical chart review and recall from their parents/guardians. Dental examinations were performed by calibrated dentists blinded to the study grouping. CD4+ (Cluster of Differentiation) T-cell counts were assayed for all participants. The diagnosis of DDE corresponded with the codes enumerated in the World Dental Federation's modified DDE Index. Analyses relied on comparative statistics to determine risk factors associated with DDE. A total of 103 participants distributed among the three groups presented with at least one form of DDE, which indicated a prevalence of 18.59%. The HI group had the highest frequency of DDE-affected teeth (4.36%), while that of the HEU and HUU groups were 2.73% and 2.05%, respectively. Overall, the most encountered DDE was code 1 (Demarcated Opacity), accounting for 30.93% of all codes. DDE codes 1, 4 and 6 showed significant associations with the HI and HEU groups in both dentitions (p < 0.05). We found no significant association DDE and either very low birth weight or preterm births. A marginal association with CD4+ lymphocyte count was observed in HI participants. DDE is prevalent in school-aged children, and HIV infection is a significant risk factor for hypoplasia, a common form of DDE. Our results were consistent with other research linking controlled HIV (with ART) to oral diseases and reinforce advocacies for public policies targeted at infants exposed/infected perinatally with HIV.
More Related Videos
 08:12
Isolation of Leukocytes from Human Breast Milk for Use in an Antibody-dependent Cellular Phagocytosis Assay of HIV Targets
Published on: September 6, 2019
 07:36
Modeling Encephalopathy of Prematurity Using Prenatal Hypoxia-ischemia with Intra-amniotic Lipopolysaccharide in Rats
Published on: November 20, 2015
Related Concept Videos
 01:26
Factors Affecting the Risk of Infection
The integrity and count of the white blood cells help the body resist pathogens and fight infection. When impaired, it reduces the body's resistance to pathogens. The acidic pH levels of the gastrointestinal, genitourinary tracts, and skin...
 01:15
Teeth
In the bud stage, the tooth germ (an aggregation of cells) starts to form in the developing jawbone. During the cap stage, the tooth germ differentiates into enamel organ, dental papilla, and dental sac, which will later develop into the tooth's enamel, dentin...
 01:08
Prevalence and Incidence
Prevalence indicates the proportion of individuals in a population who have a specific disease or health...
 01:07
Teratogenicity
 01:25
Immunodeficiency Diseases
There are three main causes of immunodeficiency...
 01:21
Tooth Anatomy
The Crown, Neck, and Root
The visible part of the tooth is referred to as the crown. It's covered by enamel, the hardest substance in the human body. The crown is uniquely shaped for each type of tooth, allowing for different functions such as cutting, tearing, or...