Related Experiment Video
Updated: Aug 7, 2025
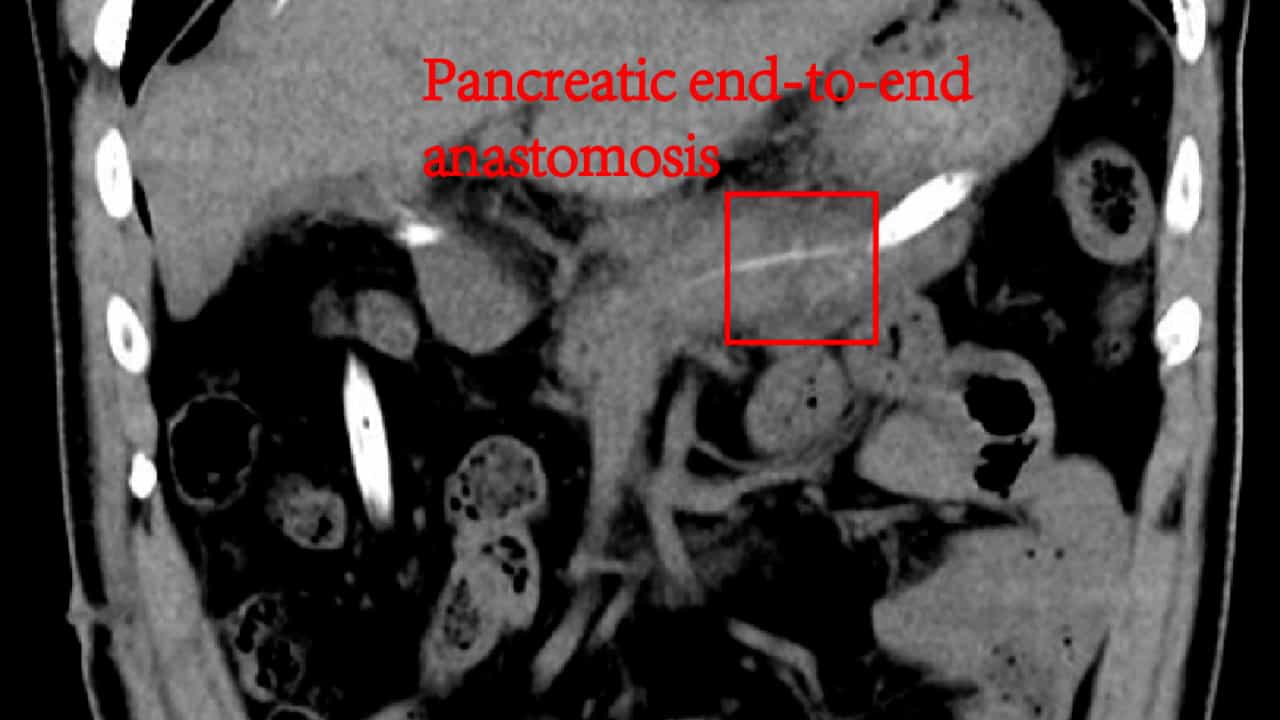

Application of Mid-Pancreatectomy with End-to-End Anastomosis in Pancreatic Benign Tumors
Published on: February 9, 2024
Middle Segment-Preserving Pancreatectomy to Avoid Pancreatic Insufficiency: Individual Patient Data Analysis of All
Thomas M Pausch1, Xinchun Liu1,2,3, Josefine Dincher1
1Department of General, Visceral and Transplantation Surgery, Heidelberg University Hospital, 69120 Heidelberg, Germany.

Abstract:
Middle segment-preserving pancreatectomy (MPP) can treat multilocular diseases in the pancreatic head and tail while avoiding impairments caused by total pancreatectomy (TP). We conducted a systematic literature review of MPP cases and collected individual patient data (IPD). MPP patients (N = 29) were analyzed and compared to a group of TP patients (N = 14) in terms of clinical baseline characteristics, intraoperative course, and postoperative outcomes. We also conducted a limited survival analysis following MPP. Pancreatic functionality was better preserved following MPP than TP, as new-onset diabetes and exocrine insufficiency each occurred in 29% of MPP patients compared to near-ubiquitous prevalence among TP patients. Nevertheless, POPF Grade B occurred in 54% of MPP patients, a complication avoidable with TP. Longer pancreatic remnants were a prognostic indicator for shorter and less eventful hospital stays with fewer complications, whereas complications of endocrine functionality were associated with older patients. Long-term survival prospects after MPP appeared strong (median up to 110 months), but survival was lower in cases with recurring malignancies and metastases (median < 40 months). This study demonstrates MPP is a feasible treatment alternative to TP for selected cases because it can avoid pancreoprivic impairments, but at the risk of perioperative morbidity.
Insights
Middle segment-preserving pancreatectomy (MPP) offers better pancreatic function preservation than total pancreatectomy (TP), avoiding diabetes and exocrine insufficiency. However, MPP carries a risk of postoperative pancreatic fistula (POPF).
Area of Science:
- Gastroenterology
- Surgical Oncology
- Endocrinology
Background:
- Total pancreatectomy (TP) is a radical treatment for pancreatic diseases but leads to severe endocrine and exocrine insufficiency.
- Middle segment-preserving pancreatectomy (MPP) is an alternative approach for specific pancreatic head and tail diseases, aiming to preserve pancreatic function.
Purpose of the Study:
- To systematically review and compare outcomes of MPP versus TP.
- To analyze clinical characteristics, operative course, and postoperative results of MPP.
- To assess long-term survival following MPP.
Main Methods:
- Systematic literature review and individual patient data (IPD) collection.
- Comparative analysis of 29 MPP patients and 14 TP patients.
- Limited survival analysis for MPP cohort.
Main Results:
- MPP preserved pancreatic functionality better than TP, with 29% incidence of new-onset diabetes and exocrine insufficiency versus near-ubiquitous rates in TP.
- Postoperative pancreatic fistula (POPF) Grade B occurred in 54% of MPP patients.
- Longer pancreatic remnants correlated with shorter hospital stays and fewer complications; older patients had more endocrine complications.
- Long-term survival after MPP was promising (median up to 110 months), but reduced in cases of recurrent malignancy or metastases.
Conclusions:
- MPP is a feasible alternative to TP for selected patients, avoiding pancreoprivic impairments.
- MPP is associated with a significant risk of perioperative morbidity, particularly POPF.
- Careful patient selection is crucial for optimizing outcomes with MPP.