Related Experiment Video
Updated: Aug 6, 2025
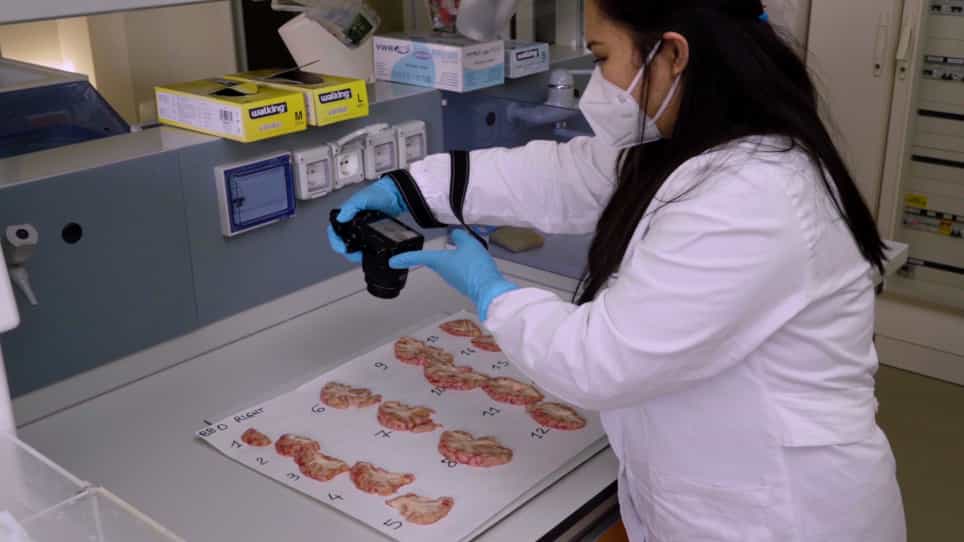
Abbiategrasso Brain Bank Protocol for Collecting, Processing and Characterizing Aging Brains
Published on: June 3, 2020
Cognitive and Clinical Characteristics of Patients With Limbic-Predominant Age-Related TDP-43 Encephalopathy
Rachel M Butler Pagnotti1, Shehroo B Pudumjee1, Chad L Cross1
1From the Cleveland Clinic Lou Ruvo Center for Brain Health (R.M.B.P., S.B.P., J.B.M.), Las Vegas; and Department of Epidemiology & Biostatistics (C.L.C.), School of Public Health, University of Nevada, Las Vegas.

Background And Objectives:
Limbic-predominant age-related TDP-43 encephalopathy (LATE) affects similar neuroanatomical networks as Alzheimer disease (AD) and is often comorbid with AD, though frequently missed in clinical diagnosis. The primary aim of this study was to elucidate the clinical and cognitive differences at baseline between patients with autopsy-confirmed LATE and patients with AD and comorbid LATE + AD.
Methods:
Clinical and neuropathologic datasets were requested from the National Alzheimer Coordination Center. Baseline data from individuals older than 75 years during death without neuropathologic indication of frontotemporal lobar degeneration were included in analyses. Pathologically defined groups reflecting LATE, AD, and comorbid LATE + AD were identified. Group differences in clinical characteristics and cognition were explored through analysis of variance and the χ2 using measures from the Uniform Data Set measures.
Results:
Pathology groups included 31 individuals with LATE (mean age: 80.6 ± 5.4 years), 393 with AD (mean age: 77.8 ± 6.4 years), and 262 with LATE + AD (mean age: 77.8 ± 6.6 years) without significant differences in sex, education, or race. Compared with participants with AD and LATE + AD pathology, participants with LATE pathology lived significantly longer (mean visits: LATE = 7.3 ± 3.7; AD = 5.8 ± 3.0; and LATE + AD = 5.8 ± 3.0; F(2,683) = 3.7, p < 0.05), reported later onset of cognitive decline (mean onset: LATE = 78.8 ± 5.7; AD = 72.5 ± 7.0; and LATE + AD = 72.9 ± 7.0; F(2,516) = 6.2, p < 0.01), and were more likely to be diagnosed as cognitively normal at baseline (LATE = 41.9%; AD = 25.4%; and LATE + AD = 12%; χ2 = 38.7, p < 0.001). Individuals with LATE (45.2%) also reported fewer memory complaints than those with AD (74.4%) or LATE + AD (66.4%; χ2 = 13.3, p = 0.001) and were less likely to be classified as impaired on the Mini-Mental State Examination (LATE = 6.5%; AD = 24.2%; and LATE + AD = 40.1%; χ2 = 29.20, p < 0.001). Across all neuropsychological measures, participants with LATE + AD pathology performed significantly worse than the AD and LATE groups.
Discussion:
Those with LATE pathology were older when cognitive symptoms began and lived longer than participants with AD or LATE + AD pathology. Participants with LATE pathology were also more likely to be classified as "cognitively normal" based on objective screening and self-report measures, and they had higher scores on neuropsychological testing. Consistent with prior literature, comorbid pathologies led to more significant cognitive and functional impairment. Early disease characteristics based on clinical presentation alone were insufficient for differentiating LATE from AD, reiterating the need for a validated biomarker.


Related Concept Videos
 01:26
Alzheimer's Disease: Overview
The clinical diagnosis of AD hinges on the presence of memory and other cognitive impairments. Biomarkers, such as changes in Aβ...
 01:30
Dementia
The progression of dementia is generally gradual....
 01:15
Parkinson's Disease: Overview
 01:22
Alzheimer's Disease: Treatment
 01:03
Long-term Depression
Calcium Ion Concentration Mechanism
If over...
 01:30
Cognitive Development During Adulthood