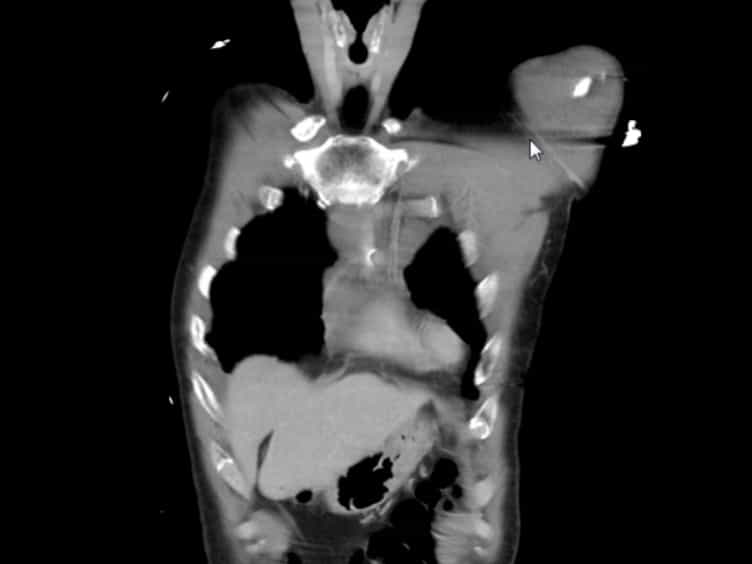
Characteristics of rib fracture patients who require chest computed tomography in the emergency department
Woosik Kim1, Juhyun Song1, Sungwoo Moon1
1Department of Emergency Medicine, Korea University Ansan Hospital, 123, Jeokgeum-Ro, Danwon-Gu, Ansan-Si, Gyeonggi-Do, 15355, Republic of Korea.

Background:
The disadvantages and complications of computed tomography (CT) can be minimized if CT is performed in rib fracture patients with high probability of intra-thoracic and intra-abdominal injuries and CT is omitted in rib fracture patients with low probability of intra-thoracic and intra-abdominal injuries. This study aimed to evaluate the factors that can identify patients with rib fractures with intra-thoracic and intra-abdominal injuries in the emergency department among patients with rib fracture.
Methods:
This retrospective observational study included adult patients (age ≥ 18 years) diagnosed with rib fracture on chest radiography prior to chest CT due to blunt chest trauma in the emergency department who underwent chest CT from January 2016 to February 2021. The primary outcomes were intra-thoracic and intra-abdominal injuries that could be identified on a chest CT. Multivariate logistic regression analysis was performed.
Results:
Among the characteristics of rib fractures, the number of rib fractures was greater (5.0 [3.0-7.0] vs. 2.0 [1.0-3.0], p < 0.001), bilateral rib fractures were frequent (56 [20.1%] vs. 12 [9.8%], p = 0.018), and lateral and posterior rib fracture was more frequent (lateral rib fracture: 160 [57.3%] vs. 25 [20.5%], p < 0.001; posterior rib fracture: 129 [46.2%] vs. 21 [17.2%], p < 0.001), and displacement was more frequent (99 [35.5%] vs. 6 [6.6%], p < 0.001) in the group with intra-thoracic and intra-abdominal injuries than in the group with no injury. The number of rib fractures (adjusted odds ratio [aOR], 1.44; 95% confidence interval [CI], 1.16-1.78; p = 0.001), lateral rib fracture (aOR, 2.80; 95% CI, 1.32-5.95; p = 0.008), and posterior rib fracture (aOR, 3.18; 95% CI, 1.45-6.94; p = 0.004) were independently associated with intra-thoracic and intra-abdominal injuries. The optimal cut-off for the number of rib fractures on the outcome was three. The number of rib fractures ≥ 3 (aOR, 3.01; 95% CI, 1.35-6.71; p = 0.007) was independently associated with intra-thoracic and intra-abdominal injuries.
Conclusion:
In patients with rib fractures due to blunt trauma, those with lateral or posterior rib fractures, those with ≥ 3 rib fractures, and those requiring O2 supplementation require chest CT to identify significant intra-thoracic and intra-abdominal injuries in the emergency department.
Related Concept Videos
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:30
Radiological Investigation I: X-ray and CT
 01:24
Flail Chest-I
Flail chest is a severe and potentially life-threatening condition characterized by the fracture of three or more adjacent ribs in multiple places. It is most commonly caused by direct impacts and trauma, such as motor vehicle accidents or injuries from a steering wheel impact. It can also occur due to falls in elderly individuals with osteoporosis, or assaults involving sharp objects.
Pathophysiology
The pathophysiology of flail chest is complex, involving fractures of...
 01:26
Pneumothorax-I
Pneumothorax can be even further classified as spontaneous, traumatic, and tension pneumothorax.
 01:23
Acute Respiratory Failure-IV
 01:27
Pneumothorax-II
Clinical Manifestations: