Left Upper Lobe Multi-Segmentectomy Versus Lobectomy for Early-Stage Lung Cancer: A Meta-Analysis
Related Experiment Video
Updated: Aug 5, 2025
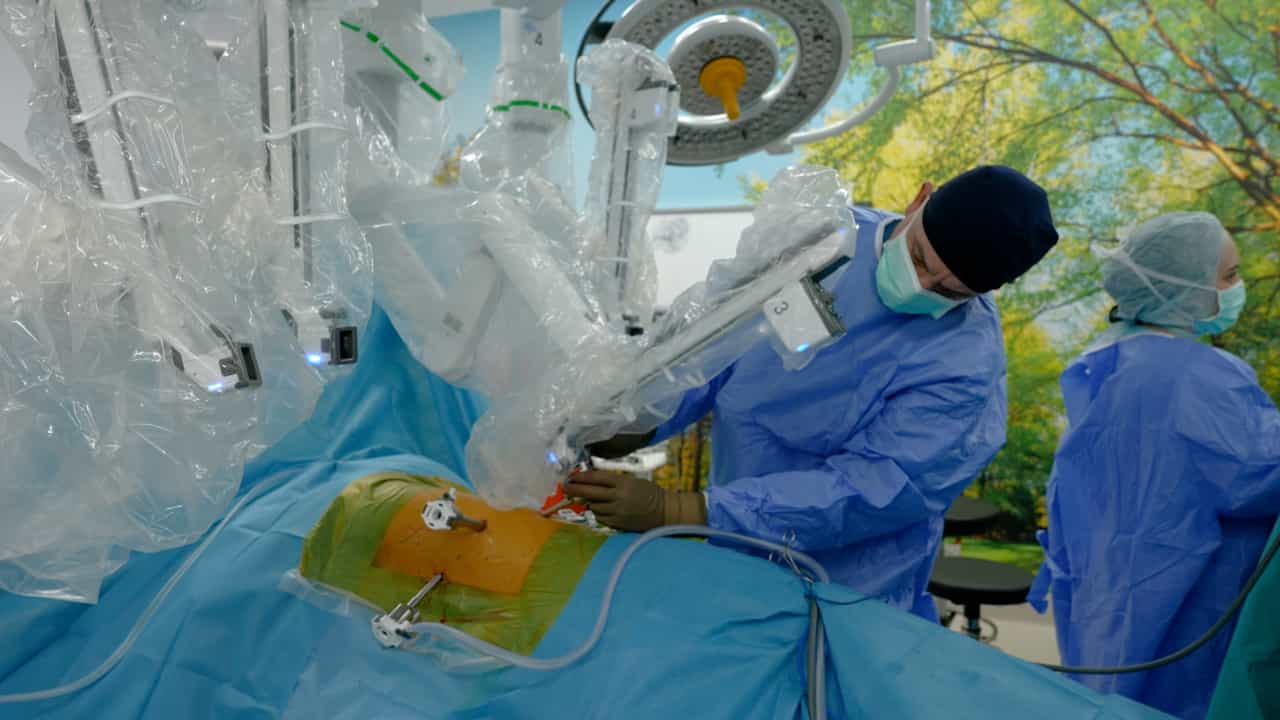
Subcostal Specimen Removal in Completely Portal Robotic Lobectomy
Published on: April 19, 2024
Nicholas G R Bayfield1, Liam Bibo1, Edward Wang1
1Department of Cardiothoracic Surgery and Transplantation, Fiona Stanley Hospital, Perth, WA, Australia.

Introduction:
The left upper lobe (LUL) has unique hilar anatomy, and LUL multi-segmentectomy (apical trisegmentectomy and lingulectomy) may result in different outcomes than both single anatomical segmentectomy and left upper lobectomy in the management of early-stage primary lung cancer; however no meta-analyses have been performed. The aim of this meta-analysis is to determine if LUL multi-segmentectomy is non-inferior to left upper lobectomy for long-term survival outcomes, or superior for in-hospital outcomes.
Methods:
Electronic databases searches were performed on PubMed, Embase, and the Cochrane Library to identify studies comparing outcomes in LUL multi-segmentectomy vs left upper lobectomy in early-stage lung cancer (clinical stage T2 N0 or less). Long-term postoperative overall and disease-free survival were assessed via reconstruction of Kaplan-Meier survival curves. In-hospital complications and length of stay, as well as long term recurrence were analysed via random effects models.
Results:
Five relevant studies were identified, including 1,196 patients. Overall survival did not differ at 5 years (multi-segmentectomy 92.6% vs lobectomy 89.3%, P=0.188), but patients undergoing LUL multi-segmentectomy had better disease-free survival at 5 years (93.1% vs 88.4%, P=0.041). Patients undergoing LUL multi-segmentectomy had a shorter mean length of hospital stay (mean difference -0.26 days, 95% CI; -0.39 to 0.14, P<0.01, I2=0.00%). There was no difference in combined in-hospital complications (P=0.14), local recurrence (P=0.35), distant recurrence (P=0.23), or overall recurrence (P=0.39).
Conclusion:
LUL multi-segmentectomy is associated with reduced hospital length of stay, but no difference in long-term overall survival compared with left upper lobectomy in the management of early-stage primary lung cancer.