Related Experiment Video
Updated: Aug 5, 2025
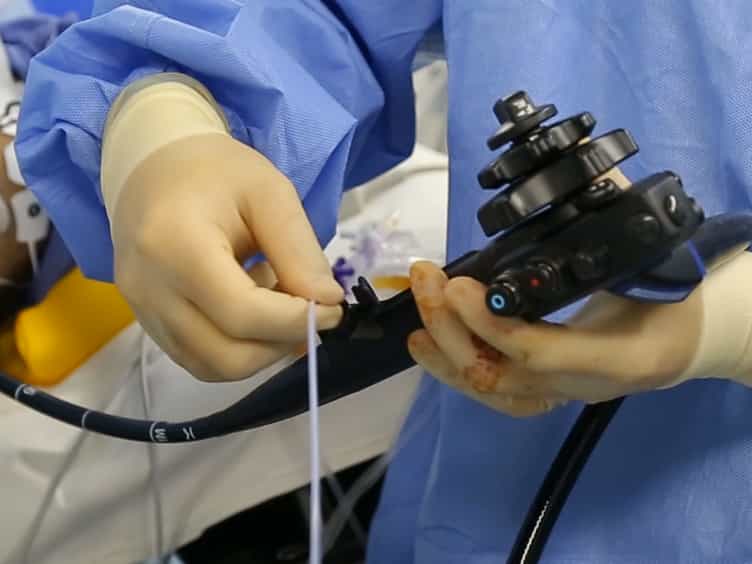

Intraoperative Gastroscopy for Tumor Localization in Laparoscopic Surgery for Gastric Adenocarcinoma
Published on: August 9, 2016
Gastric adenocarcinoma burden, trends and survival in Cali, Colombia: A retrospective cohort study
Luis Gabriel Parra-Lara1,2, Juan Camilo Falla-Martínez2, Daniel Francisco Isaza-Pierotti2
1Facultad de Ciencias de la Salud, Universidad Icesi, Cali, Colombia.

Background:
Gastric adenocarcinoma (GA) has changed in recent decades. Cancer estimates are often calculated from population-based cancer registries, which lack valuable information to guide decision-making (clinical outcomes). We describe the trends in clinical practice for GA using a hospital-based cancer registry over a timespan of 15 years.
Methods:
A retrospective cohort study was conducted. Data were gathered from adults diagnosed and treated for GA at Fundación Valle del Lili (FVL), between 2000 and 2014, from the hospital's own cancer registry and crossed with Cali's Cancer Registry. Additional data were obtained directly from clinical records, pathology reports and the clinical laboratory. Patients younger than 18 years and those for whom limited information was available in the medical history were excluded. A survival analysis was conducted using Kaplan-Meier method.
Results:
A total of 500 patients met eligibility criteria. Median age was 64 years (IQR: 54-74 years), 39.8% were female, 22.2% were at an early stage, 32.2% had a locally advanced disease, and 29% a metastatic disease, 69% had intestinal subtype, 48.6% had a positive H. pylori test, 85.2% had a distal lesion, 62% underwent gastrectomy, 60.6% lymphadenectomy, and 40.6% received chemotherapy. Survival at 5 years for all cases was 39.9% (CI 95% 35.3-44.5). Survival decreased over time in all groups and was lower in age-groups <39 and 60-79 with either locally advanced or metastatic disease. Prognostic factors that were significant in the Cox proportional-hazards model were late stages of the tumor (locally advanced: HR=2.52; metastatic: HR=4.17), diffuse subtype (HR=1.40), gastrectomy (subtotal: HR=0.42; total: 0.44) and palliative chemotherapy (HR=0.61).
Conclusions:
The treatment of GA has changed in recent decades. GA survival was associated with clinical staging, diffuse subtype, gastrectomy and palliative chemotherapy. These findings must be interpreted in the context of a hospital-based study.

Related Concept Videos
 01:21
Cancer Survival Analysis
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure...