Related Experiment Video
Updated: Aug 5, 2025


A New Single Chamber Implantable Defibrillator with Atrial Sensing: A Practical Demonstration of Sensing and Ease of Implantation
Published on: February 28, 2012
Predicted Need for Atrial and Ventricular Pacing Per Indication Group in Patients With Dual-Chamber Pacemakers
Karel T N Breeman1, Leonard A Dijkshoorn1, Arthur A M Wilde1
1Amsterdam UMC location University of Amsterdam, Department of Cardiology, Amsterdam, The Netherlands; Amsterdam Cardiovascular Sciences, Heart failure & arrhythmias, Amsterdam, The Netherlands.

Background:
Bradyarrhythmias are adequately treated with pacemakers. There are different pacing modes (single-chamber, dual-chamber, cardiac resynchronisation therapy [CRT] and conduction system pacing [CSP]) and a choice between leadless or transvenous pacemakers. The expected pacing need is important for determining optimal pacing mode and device type. This study aimed to evaluate atrial pacing (AP) and ventricular pacing (VP) percentages over time for the most common pacing indications.
Methods:
Included patients were aged ≥18 years with a dual-chamber rate-modulated [DDD(R)] pacemaker implantation and ≥1 year of follow-up at a tertiary centre between January 2008 and January 2020. Baseline characteristics, AP and VP at yearly follow-up visits up to 6 years after implantation were retrieved from the medical records.
Results:
A total of 381 patients were included. Primary pacing indications were incomplete atrioventricular block (AVB) in 85 (22%), complete AVB in 156 (41%) and sinus node dysfunction (SND) in 140 (37%) patients. Mean age at implantation was 71±14, 69±17 and 68±14 years, respectively (p=0.23). Median follow-up was 42 months (25-68 months). Overall, AP was highest in SND with median 37% (7%-75%) versus 7% (1%-26%) in incomplete AVB and 3% (1%-16%) in complete AVB (p<0.001); VP was highest in complete AVB with median 98% (43%-100%) versus 44% (7%-94%) in incomplete AVB and 3% (1%-14%) in SND (p<0.001). Ventricular pacing significantly increased over time in patients with incomplete AVB and SND (both p=0.001).
Conclusions:
These results confirm the pathophysiology of different pacing indications, causing clear differences in pacing need and expected battery longevity. They may help guide optimal pacing mode and suitability for leadless or physiological pacing.


Related Concept Videos
 01:25
ECG Interpretation of Arrhythmias II: Atrial, Junctional and Ventricular Arrhythmias
 01:18
Dysrhythmias IV: Characteristics of Bradyarrhythmias
 01:25
Dysrhythmias VI: Management of Dysrhythmias
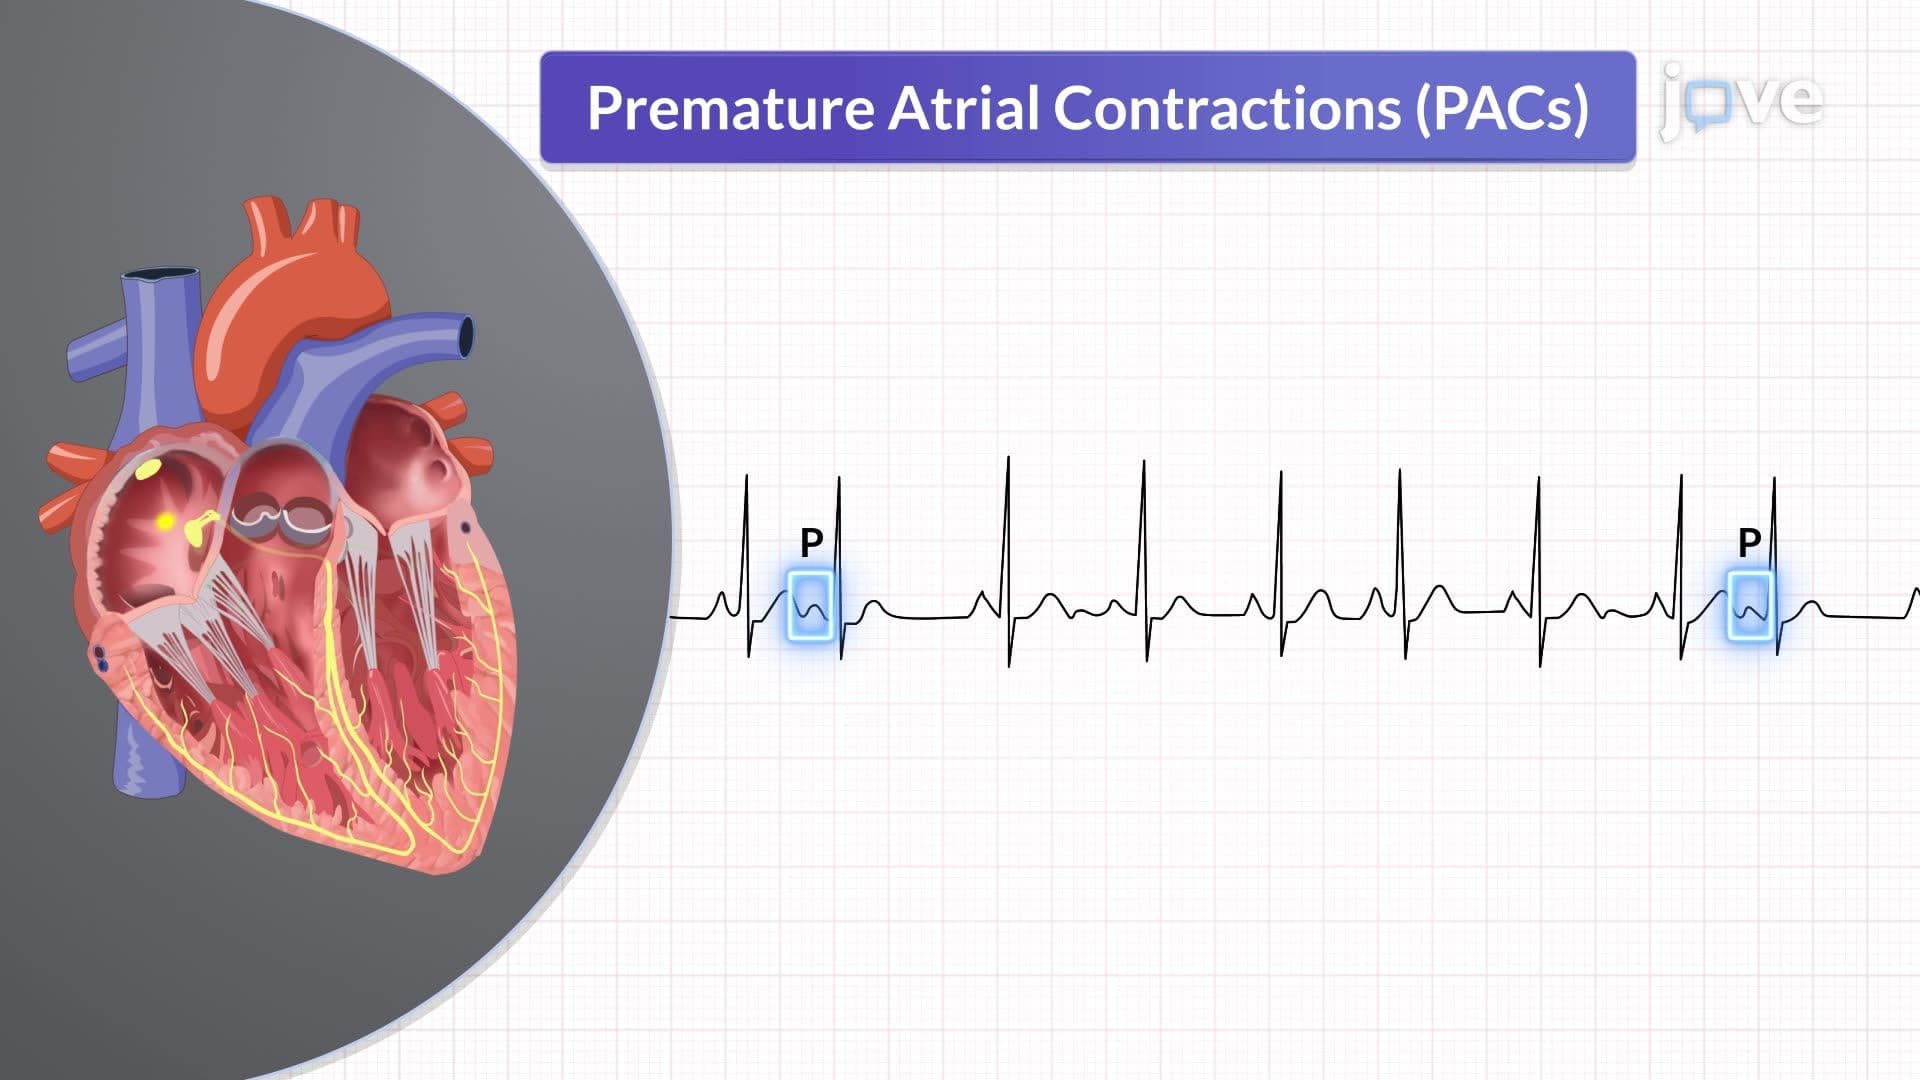 01:29
Dysrhythmias III: Characteristics of Dysrhythmias
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy
 01:19
Conduction System of the Heart
The pacemaker cells are located in two primary nodes: the sinoatrial (SA) node and the atrioventricular (AV) node. The SA node pacemaker cells can autonomously depolarize, triggering an action potential that leads to the...