Related Experiment Video
Updated: Aug 4, 2025
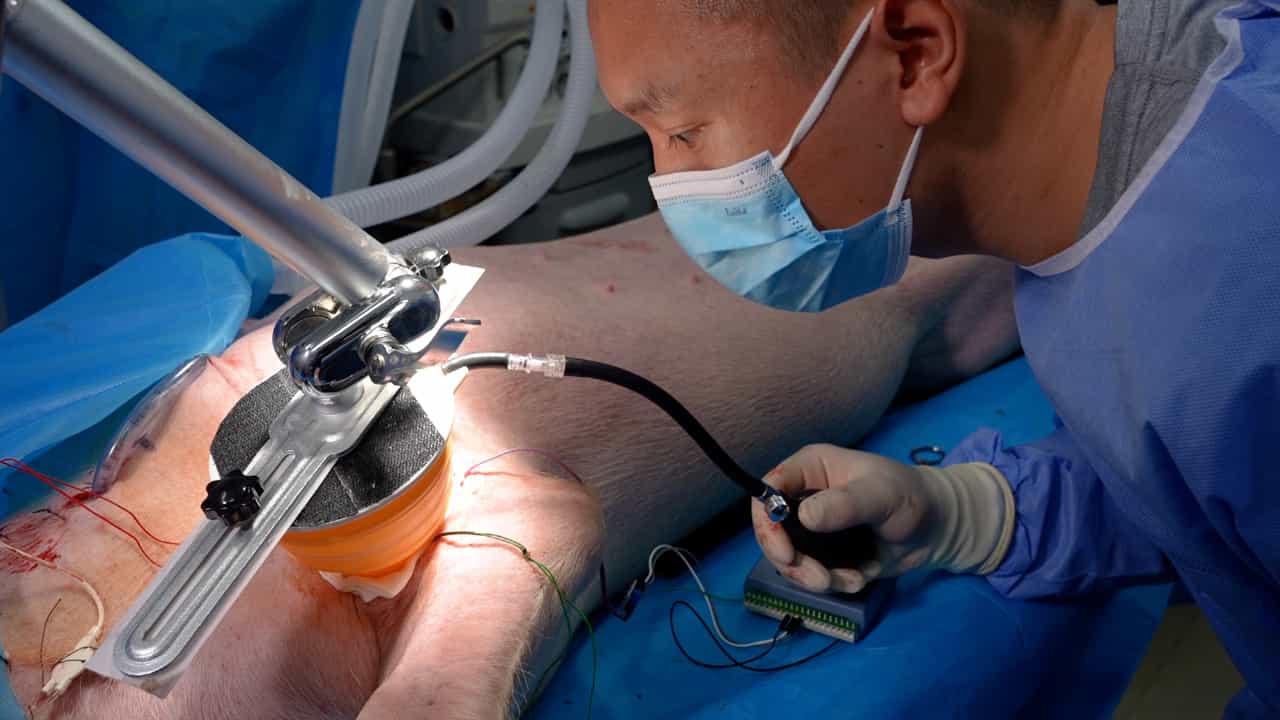

A New Hybrid Quantitative Evaluation Model for Axillary Junctional Hemorrhage in Swine
Published on: December 6, 2024
Derivation and validation of a novel risk score to predict need for haemostatic intervention in acute upper
Isobel Marks1, Imran Karim Janmohamed2, Sadek Malas1
1Gastroenterology, Imperial College Healthcare NHS Trust, London, UK.

Background:
Acute upper gastrointestinal bleeding (AUGIB) is a common medical emergency, which takes up considerable healthcare resources. However, only approximately 20%-30% of bleeds require urgent haemostatic intervention. Current standard of care is for all patients admitted to hospital to undergo endoscopy within 24 hours for risk stratification, but this is difficult to achieve in practice, invasive and costly.
Aim:
To develop a novel non-endoscopic risk stratification tool for AUGIB to predict the need for haemostatic intervention by endoscopic, radiological or surgical treatments. We compared this with the Glasgow-Blatchford Score (GBS).
Design:
Model development was carried out using a derivation (n=466) and prospectively collected validation cohort (n=404) of patients who were admitted with AUGIB to three large hospitals in London, UK (2015-2020). Univariable and multivariable logistic regression analysis was used to identify variables that were associated with increased or decreased chances of requiring haemostatic intervention. This model was converted into a risk scoring system, the London Haemostat Score (LHS).
Results:
The LHS was more accurate at predicting need for haemostatic intervention than the GBS, in the derivation cohort (area under the receiver operating curve (AUROC) 0.82; 95% CI 0.78 to 0.86 vs 0.72; 95% CI 0.67 to 0.77; p<0.001) and validation cohort (AUROC 0.80; 95% CI 0.75 to 0.85 vs 0.72; 95% CI 0.67 to 0.78; p<0.001). At cut-off scores at which LHS and GBS identified patients who required haemostatic intervention with 98% sensitivity, the specificity of the LHS was 41% vs 18% with the GBS (p<0.001). This could translate to 32% of inpatient endoscopies for AUGIB being avoided at a cost of only a 0.5% false negative rate.
Conclusions:
The LHS is accurate at predicting the need for haemostatic intervention in AUGIB and could be used to identify a proportion of low-risk patients who can undergo delayed or outpatient endoscopy. Validation in other geographical settings is required before routine clinical use.

Related Concept Videos
 01:30
Anticoagulant Drugs: Low-Molecular-Weight Heparins
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...
 01:29
Venous Thrombosis III: Interprofessional Care
 01:05
Introduction to Hemostasis
The three phases of hemostasis involve many clotting factors present in plasma and several substances released by platelets and injured tissue cells. It is a fast, localized,...