Related Experiment Video
Updated: Aug 4, 2025


Assessment of Morphine-induced Hyperalgesia and Analgesic Tolerance in Mice Using Thermal and Mechanical Nociceptive Modalities
Published on: July 29, 2014
Morphine and Hydromorphone Effects, Side Effects, and Variability: A Crossover Study in Human Volunteers
Konrad Meissner1, Albert Dahan2, Erik Olofsen2
1Department of Anesthesiology, University Medical Center Göttingen, Göttingen, Germany; Department of Anesthesiology, Leiden University Medical Center, Leiden, The Netherlands; Department of Anesthesiology, Washington University in St. Louis, St. Louis, Missouri.

Background:
Balancing between opioid analgesia and respiratory depression continues to challenge clinicians in perioperative, emergency department, and other acute care settings. Morphine and hydromorphone are postoperative analgesic standards. Nevertheless, their comparative effects and side effects, timing, and respective variabilities remain poorly understood. This study tested the hypothesis that IV morphine and hydromorphone differ in onset, magnitude, duration, and variability of analgesic and ventilatory effects.
Methods:
The authors conducted a randomized crossover study in healthy volunteers. Forty-two subjects received a 2-h IV infusion of hydromorphone (0.05 mg/kg) or morphine (0.2 mg/kg) 1 to 2 weeks apart. The authors measured arterial opioid concentrations, analgesia in response to heat pain (maximally tolerated temperature, and verbal analog pain scores at discrete preset temperatures to determine half-maximum temperature effect), dark-adapted pupil diameter and miosis, end-expired carbon dioxide, and respiratory rate for 12 h after dosing.
Results:
For morphine and hydromorphone, respectively, maximum miosis was less (3.9 [3.4 to 4.2] vs. 4.6 mm [4.0 to 5.0], P < 0.001; median and 25 to 75% quantiles) and occurred later (3.1 ± 0.9 vs. 2.3 ± 0.7 h after infusion start, P < 0.001; mean ± SD); maximum tolerated temperature was less (49 ± 2 vs. 50 ± 2°C, P < 0.001); verbal pain scores at end-infusion at the most informative stimulus (48.2°C) were 82 ± 4 and 59 ± 3 (P < 0.001); maximum end-expired CO2 was 47 (45 to 50) and 48 mmHg (46 to 51; P = 0.007) and occurred later (5.5 ± 2.8 vs. 3.0 ± 1.5 h after infusion start, P < 0.001); and respiratory nadir was 9 ± 1 and 11 ± 2 breaths/min (P < 0.001), and occurred at similar times. The area under the temperature tolerance-time curve was less for morphine (1.8 [0.0 to 4.4]) than hydromorphone (5.4°C-h [1.6 to 12.1] P < 0.001). Interindividual variability in clinical effects did not differ between opioids.
Conclusions:
For morphine compared to hydromorphone, analgesia and analgesia relative to respiratory depression were less, onset of miosis and respiratory depression was later, and duration of respiratory depression was longer. For each opioid, timing of the various clinical effects was not coincident. Results may enable more rational opioid selection, and suggest hydromorphone may have a better clinical profile.


Related Concept Videos
 01:15
Opioid Analgesics: Synthetic and Semisynthetic Opioids
 01:20
Opioid Analgesics: Morphine and Other Natural Cogeners
 01:22
Opioid Receptors: Overview
 01:25
Analgesia and Pain Management
 01:16
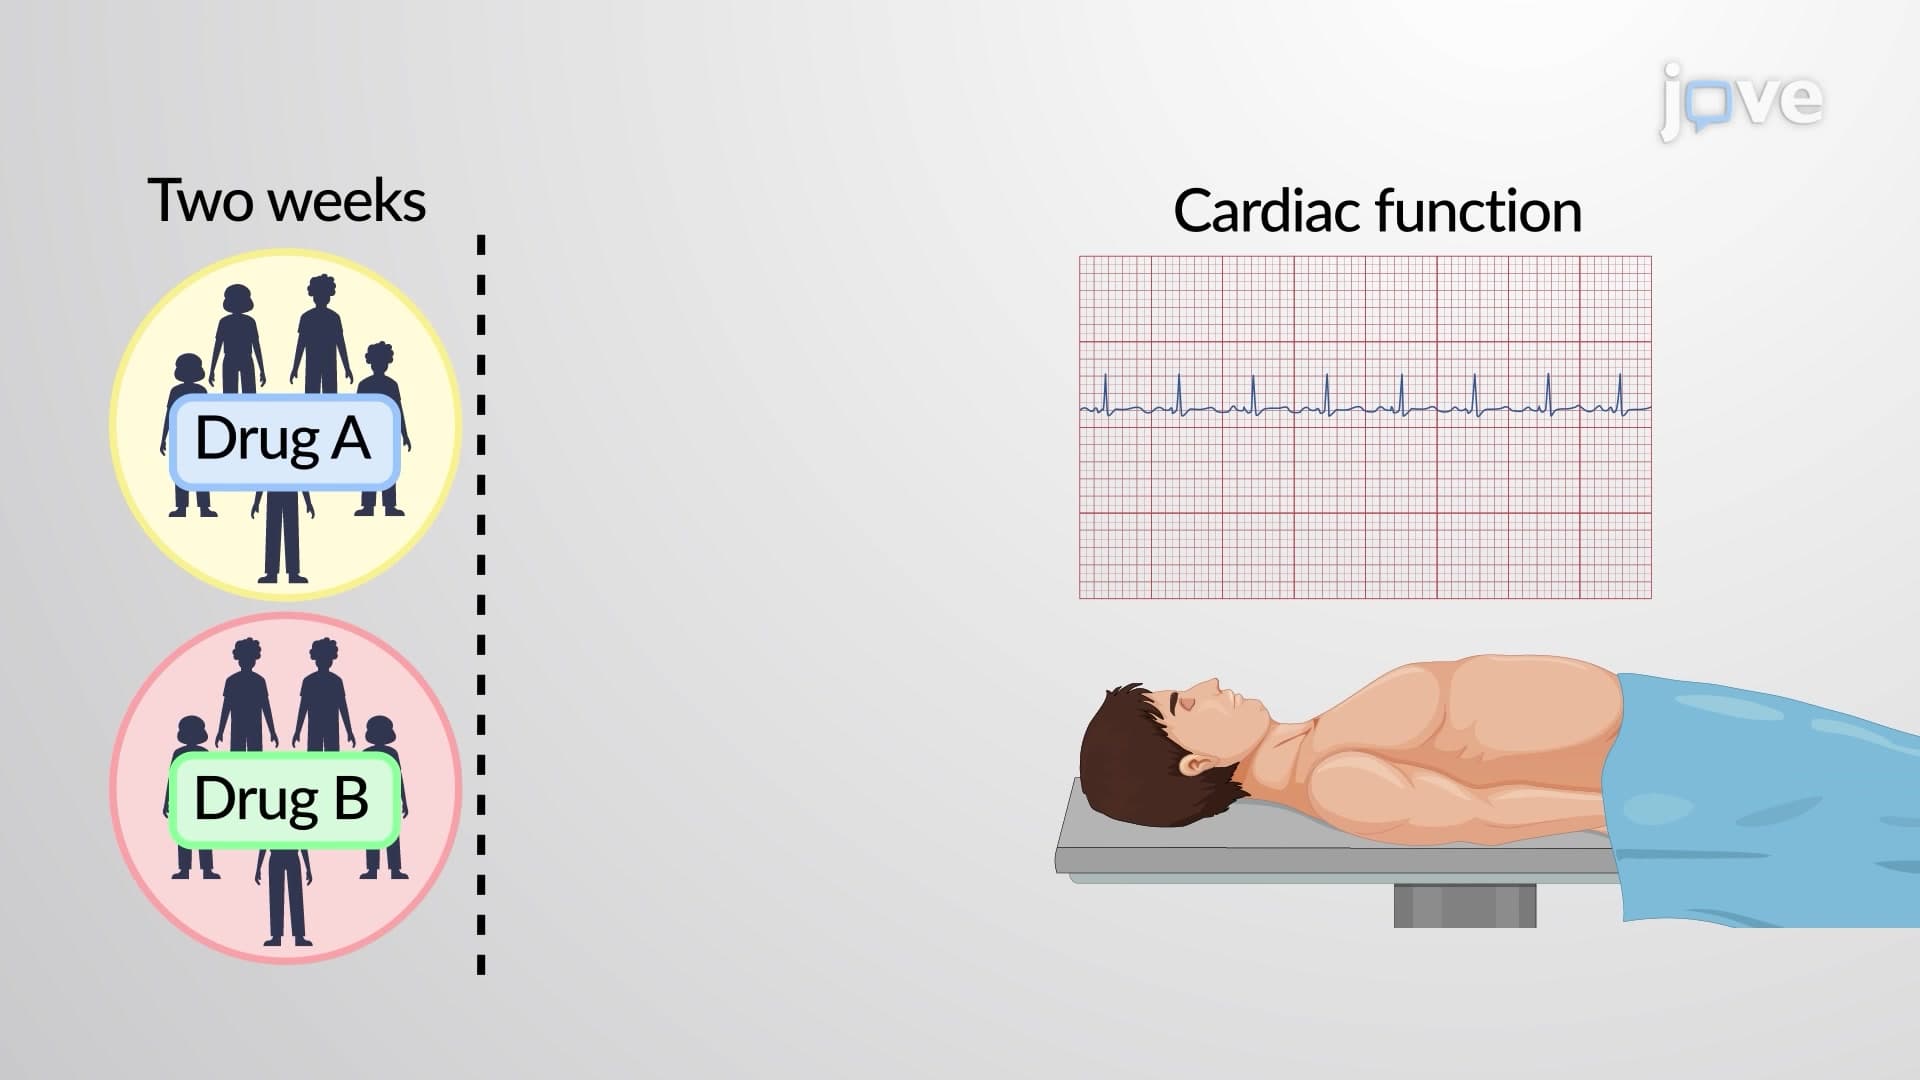
Crossover Experiments
Crossover designs are performed even with smaller sample sizes since the samples can act as their controls. These are better than simple randomized trials since patients are exposed to all the treatments.
 01:15
Drug Abuse and Addiction: Pharmacological Phenomena