Disturbances in sodium and chloride homeostasis predict outcome in stable and critically ill patients with cirrhosis
Related Experiment Video
Updated: Aug 4, 2025
Invasive Hemodynamic Characterization of the Portal-hypertensive Syndrome in Cirrhotic Rats
Published on: August 1, 2018
Georg Semmler1,2, Bernhard Scheiner1,2,3, Lorenz Balcar1,2
1Division of Gastroenterology and Hepatology, Department of Internal Medicine III, Medical University of Vienna, Vienna, Austria.

Background:
Hyponatremia has prognostic implications in patients with cirrhosis, and thus, has been incorporated in the 2016 MELD-UNOS update. Changes in serum chloride are commonly perceived as 'just' parallel to changes in serum sodium. However, these are less well studied in the context of cirrhosis.
Aims:
To investigate whether serum chloride independently predicts outcomes in patients with advanced chronic liver disease (ACLD) and stable clinical course or with critical illness.
Methods:
891 patients with ACLD (defined by hepatic venous pressure gradient [HVPG] ≥6 mm Hg) were followed after HVPG measurement between 2003 and 2020 (ACLD cohort). 181 critically ill patients with cirrhosis admitted to the ICU between 2004 and 2007 were recruited for the ICU cohort. Hypo-/hypernatremia (normal: 136-145 mmol/L) and hypo-/hyperchloremia (normal: 98-107 mmol/L) at baseline were assessed.
Results:
ACLD cohort: 68% of male patients with a median MELD (adjusted for Na) of 11 (9-17) were included (Child-Pugh-stages-A/B/C: 46%/38%/16%) and followed for a median of 60 months. Lower serum chloride (adjusted average HR per mmol/L: 0.965 [95% confidence interval (95% CI): 0.945-0.986], p = 0.001) showed a significant association with hepatic decompensation/liver-related mortality on multivariable Cox regression analysis adjusted for age, HVPG, albumin and MELD. In line, hypochloremia was significantly associated with hepatic decompensation/liver-related mortality (adjusted average HR: 1.656 [95% CI:1.267-2.163], p < 0.001). ICU cohort: 70% of patients were male, median MELD was 31(22-39) at ICU admission (92% with Child-Pugh-stage-C). After adjusting for hypo-/hypernatremia, MELD, and blood pH, hypochloremia remained independently associated with ICU-mortality (aOR Cl: 3.200 [95%CI: 1.209-8.829], p = 0.021).
Conclusion:
Hypochloremia is associated with increased mortality in clinically stable and critically ill patients with cirrhosis independently of MELD including serum sodium.


Related Concept Videos
 01:29
Roles of Electrolytes: Chloride and Bicarbonate
Conditions such as hypochloremia can arise from insufficient chloride reabsorption by the kidneys, often compounded by extended bouts of diarrhea, vomiting,...
 01:24
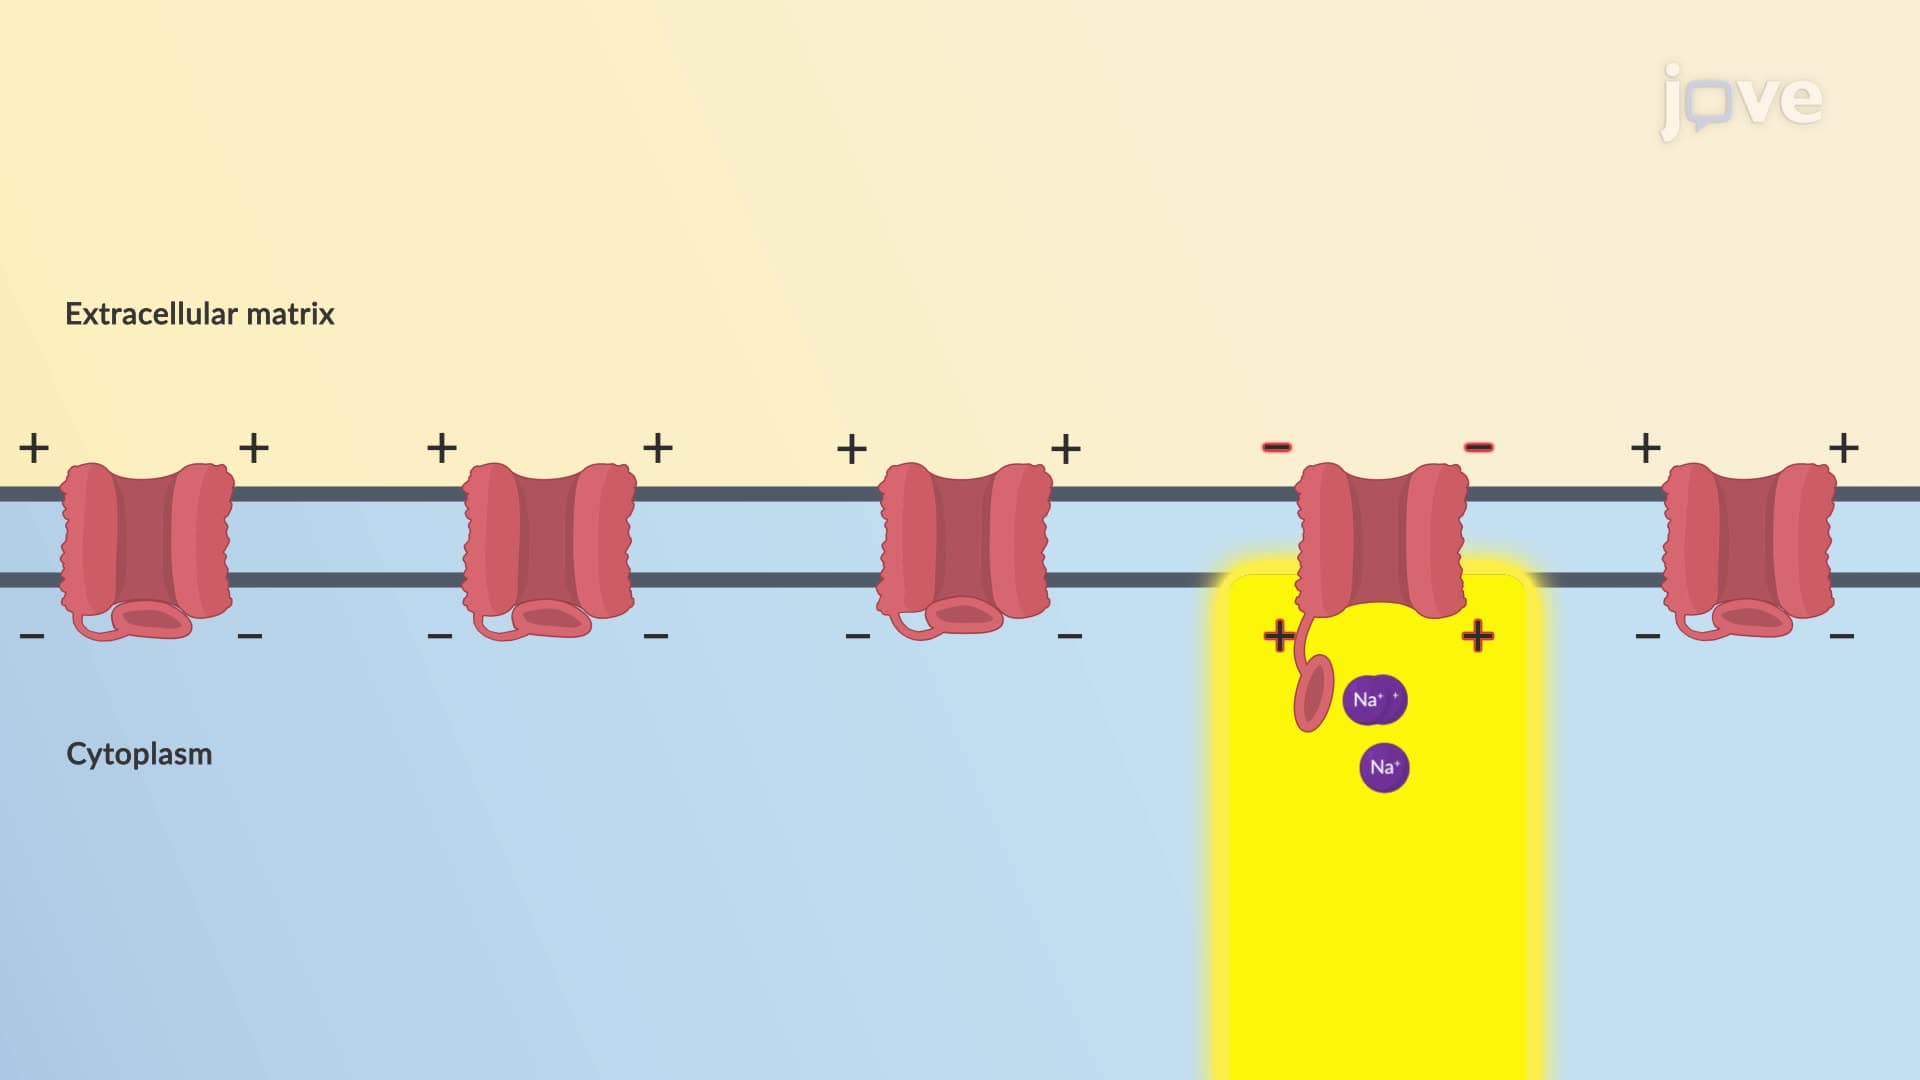
Roles of Electrolytes: Sodium and Potassium
 01:22
Heart Failure VI: Adjunct Therapies
 01:18
Chronic Kidney Disease IV: Nursing Management
 01:22
Acute Kidney Injury VI: Nursing Management
 01:29
Disorder of Water Balance
Dehydration
Dehydration occurs when the body loses fluids (particularly water).
Causes:
The major causes of dehydration include excessive sweating, fever, vomiting, diarrhea, and diuresis.
Signs and Symptoms:
Symptoms primarily include intense...